

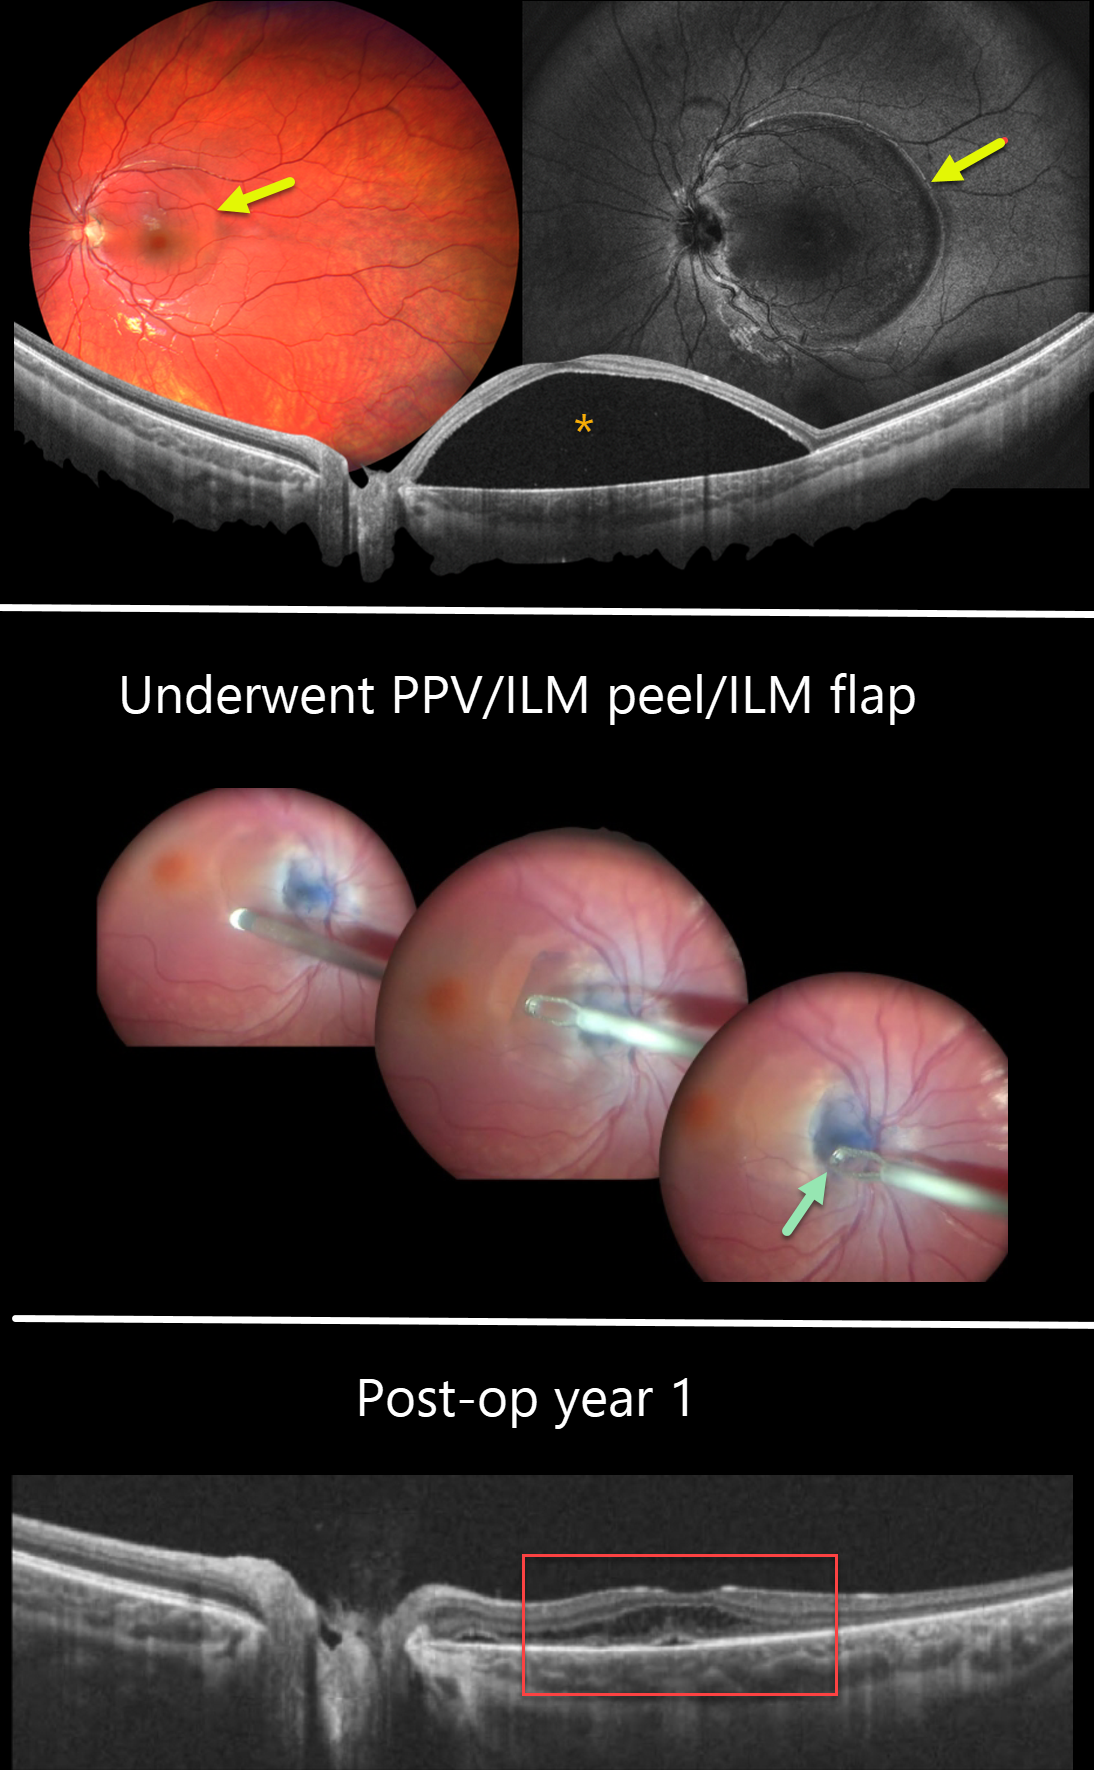
This 10YO female was referred for vision loss in her left eye from a macular detachment and optic pit. Vision was 20/20 in the normal OD and 20/80 OS.
Color imaging shows a round elevation of the entire macula, which is confirmed on widefield OCT. An optic nerve pit is noted along the inferotemporal edge of the nerve.
The macular detachment was initially treated with micropulse laser, resulting in partial reabsorption. Due to persistent fluid, one year later, pars plana vitrectomy with ILM peeling in the inter-papillomacular area and ILM flap into the pit was performed. One year postoperatively, the macular detachment resolved, and vision improved to 20/50.
Learning Points:
An optic nerve pit is a rare (about 0.1% prevalence) congenital anomaly thought to be caused by incomplete closure of the optic fissure during gestation. Pits are most often located within or along the inferior-temporal disc margin and usually appear as a gray depression.
While most optic pits are asymptomatic, they can cause vision loss by forcing fluid into the inner and outer retina, and ultimately into the subretinal space (optic pit maculopathy). The source of the fluid remains a topic of ongoing debate, with the fluid originating either from the vitreous or the subarachnoid space.
A host of treatments for optic pit maculopathy have been suggested over the years. However, a recent meta-analysis suggested that a plain-vanilla vitrectomy without gas tamponade is as successful as other procedures (Zheng et al, Ophthalmology Retina 2020;4:289-299).



