

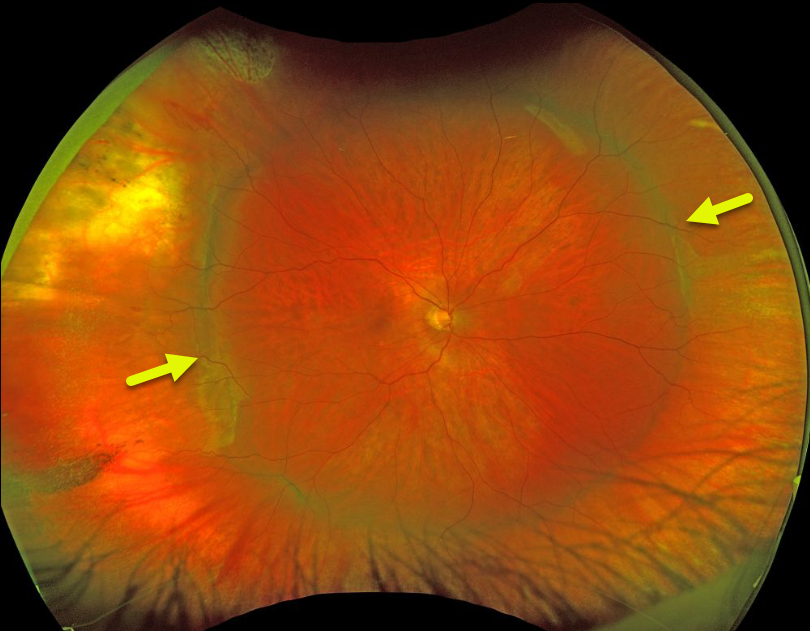
This patient has a broad encircling scleral buckle that’s beautifully imaged in this Optos photograph.
Learning Points:
The normal neurosensory retina remains attached to the RPE due to numerous physiologic mechanisms, including the inner (retinal vascular endothelium) and outer (tight junctions at the apex of the RPE cells) blood retinal barriers, hyperosmotic choroid passively drawing fluid into the subretinal space, RPE pump, interphotoreceptor matrix, and friction between the RPE microvilli and the photoreceptor outer segments.
Rhegmatogenous retinal detachment (RRD) occurs when liquid vitreous, entering the subretinal space through a retinal break, overwhelms these forces, favoring retinal detachment.
Repairing RRD involves finding and closing all breaks, essentially denying the liquid vitreous access to the subretinal space. The break(s) can be closed internally with a gas bubble via pneumatic retinopexy or vitrectomy surgery, or externally by securing a piece of silicone material to the sclera (scleral buckle). This indents, or buckles, the sclera against the retinal break.
The choice for what procedure to use to reattach the retina is complex, depending on each patient’s unique anatomy and on the surgeon’s preference. Historically, scleral buckling was the only method before vitrectomy surgery was introduced by Machemer in the early 1970’s.
There are advantages and disadvantages to all techniques. With one or more surgeries, there is a high anatomic success rate regardless of how the retina is reattached.



