

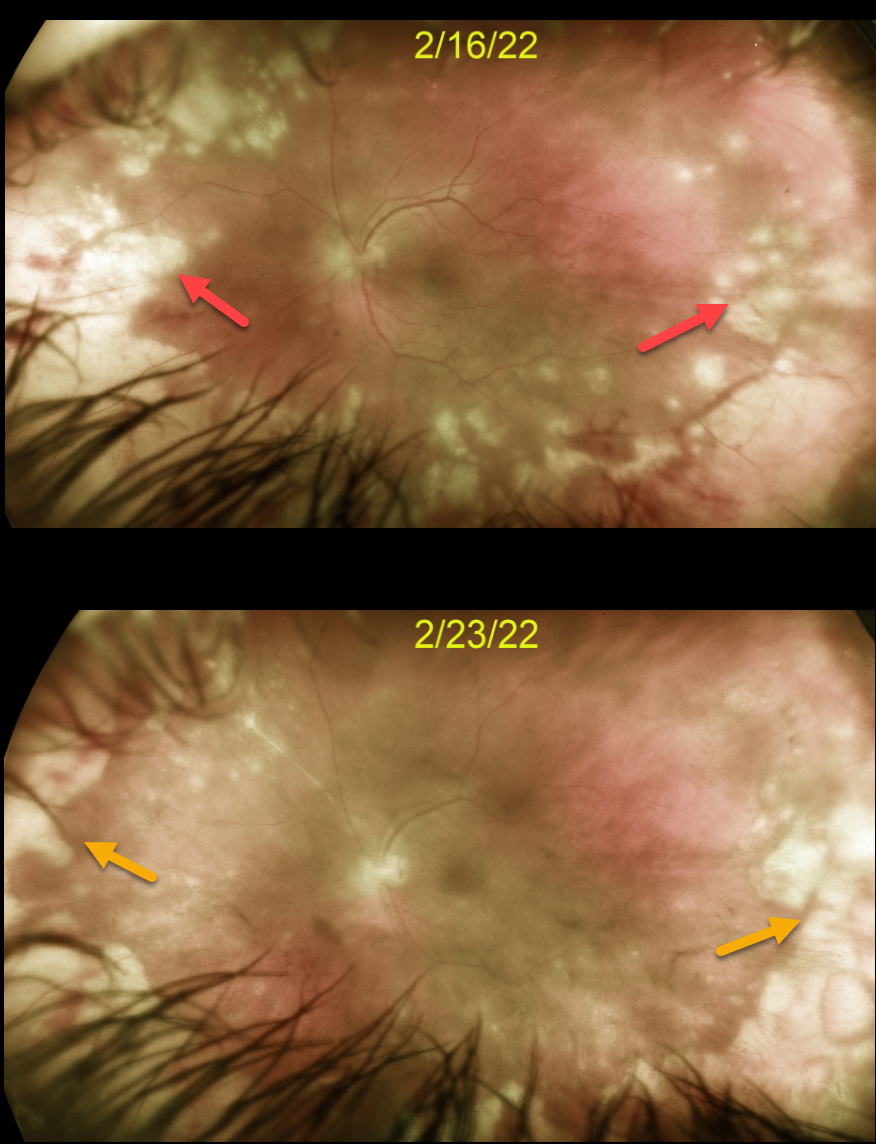
This 44YO otherwise healthy male presented with 1 week of floaters, blurred vision and pain in his left eye. Vision was 20/20 in his normal right eye and 20/100 in his left eye. There was panuveitis in his left eye, including a moderate granulomatous anterior uveitis, vitritis, and peripheral multifocal mostly outer white retinitis.
We diagnosed him with acute retinal necrosis syndrome (ARNS), and started him on oral valganciclovir 900 mg BID and a baby aspirin daily. Several days later, oral prednisone 60mg/day was begun.
After 1 week, vision remained at 20/100 but with subjective improvement. The retinitis was significantly improving. We continue to follow him very closely.
Learning Points:
The Herpes zoster virus most commonly causes ARNS. It usually occurs in immunocompetent individuals and is a rapidly progressive panuveitis with hemorrhagic and ischemic unilateral (ARNS) or bilateral (BARNS) retinal necrosis, typically beginning in the retinal periphery.
ARNS is often a devastating and blinding infection due to the high risk for retinal detachment as well as macular and optic nerve involvement.
The latest meta-analysis argues for systemic antiviral therapy and prophylactic vitrectomy, with uncertain benefits for prophylactic laser photocoagulation or adjunctive intravitreal antivirals (see Zhao et al, Retina 2021;41:965-978).



