

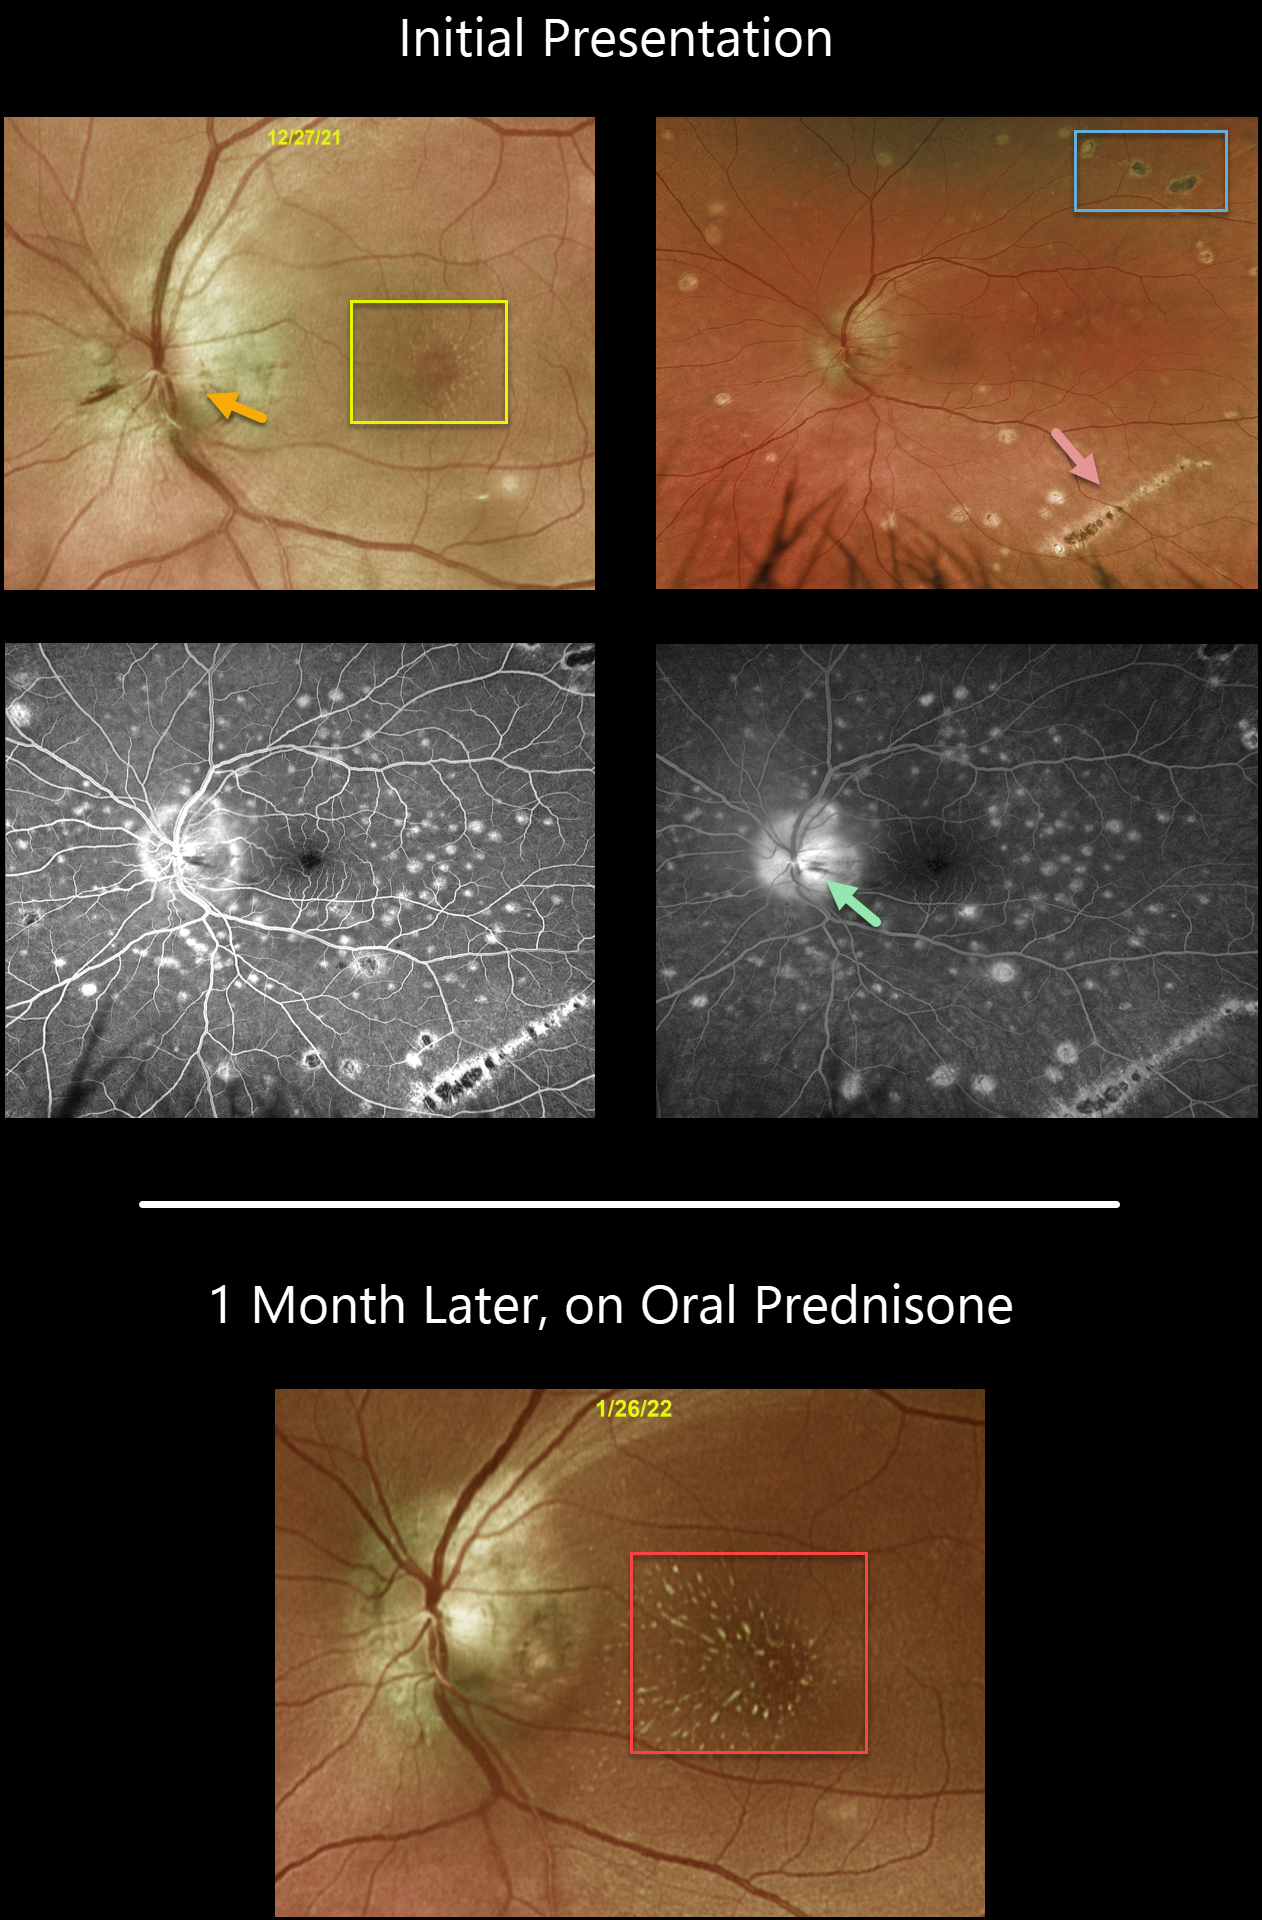
This healthy 46YO male presented on 12/27/21 with 1 day of decreasing vision in his left eye. Vision was 20/25 in his normal right eye and 20/60 in his left eye.
The left nerve was swollen with a faint macular lipid star. There were bilateral multifocal scars and an inferotemporal streak lesion in his left eye. Fluorescein angiography shows minimal left optic nerve staining.
An extensive workup, including labs for Bartonella, Lyme, tuberculosis, sarcoidosis, toxoplasmosis, syphilis, and a chest x-ray, was all negative. He denied any systemic symptoms, although he recently had a COVID-19 vaccine. Serology showed positive IgG and negative IgM antibodies for COVID-19.
He was treated with a tapering 1-month course of oral prednisone, and at his 1/26/22 visit, the nerve edema had resolved, with a more prominent macular lipid star.
Learning Points:
The diagnosis for a unilateral swollen nerve is extensive. However, it becomes much smaller when associated with inner retinal ischemia and lipid exudation (neuroretinitis), including cat scratch (Bartonella), Lyme disease, and syphilis. When no underlying cause is found, the entity is called Leber’s idiopathic stellate neuroretinitis. The condition is self-limited, so treatment is not usually recommended.
We gave our patient the presumed diagnosis of Leber’s idiopathic stellate neuroretinitis due to the unilateral swollen nerve followed by a lipid star, in the absence of a positive infectious workup. The bilateral multifocal scars appeared inactive and were likely present long before he presented with a unilateral swollen nerve.
Our best guess is that the scarring represents ocular histoplasmosis or multifocal choroiditis unrelated to the swollen nerve, although we can’t rule out that the two might be related.



