

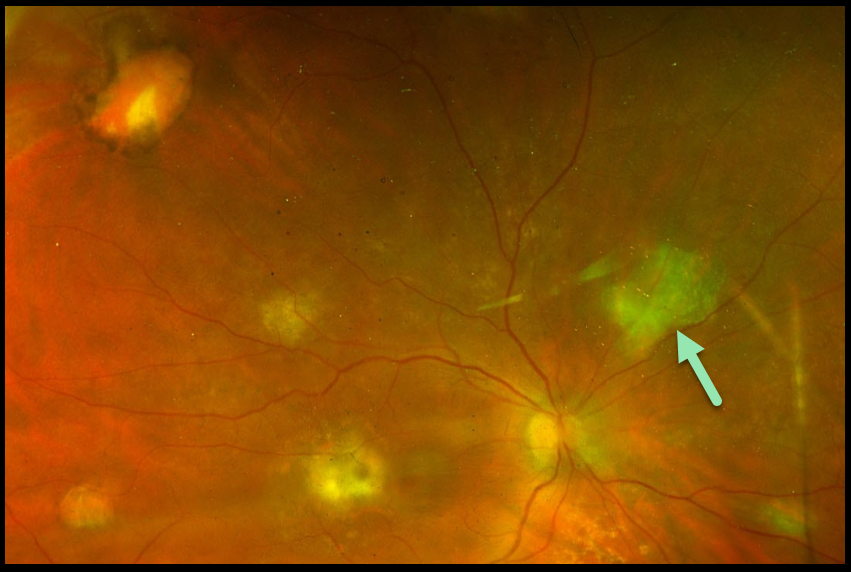
In October 2021, this 73YO emaciated woman presented for a routine cataract evaluation. Vision was 20/600 with moderate cell and flare bilaterally. Posterior segments were grossly normal, but the views were limited due to vitreous opacification.
There was a history of colon cancer treated with chemotherapy in 2018. In 2019, she suffered a cerebral hemorrhage and was later evacuated via craniotomy. In 2020, she developed a bowel obstruction during chemotherapy treatment, and total parenteral nutrition was initiated. In August 2021, a central line infection caused Candida albicans sepsis. Voriconazole was administered until blood cultures came back negative, and she became afebrile.
Based on the clinical history, she was felt to have bilateral fungal endophthalmitis despite the negative blood cultures and negative in-office vitreous and aqueous stains and cultures.
Fluconazole 400 mg/day and intravitreal Amphotericin B (0.01 mg/0.1 ml) were administered, with improvement in anterior segment inflammation but no change in the vitritis.
Eventually, a diagnostic vitrectomy was performed in the right eye, revealing yellowish retinal foci, typical for endogenous Candida albicans endophthalmitis, although Gram stain and cultures were negative.
Vision improved to 20/100 in the right eye. We plan on performing vitrectomy in her left eye when her clinical condition allows.



