

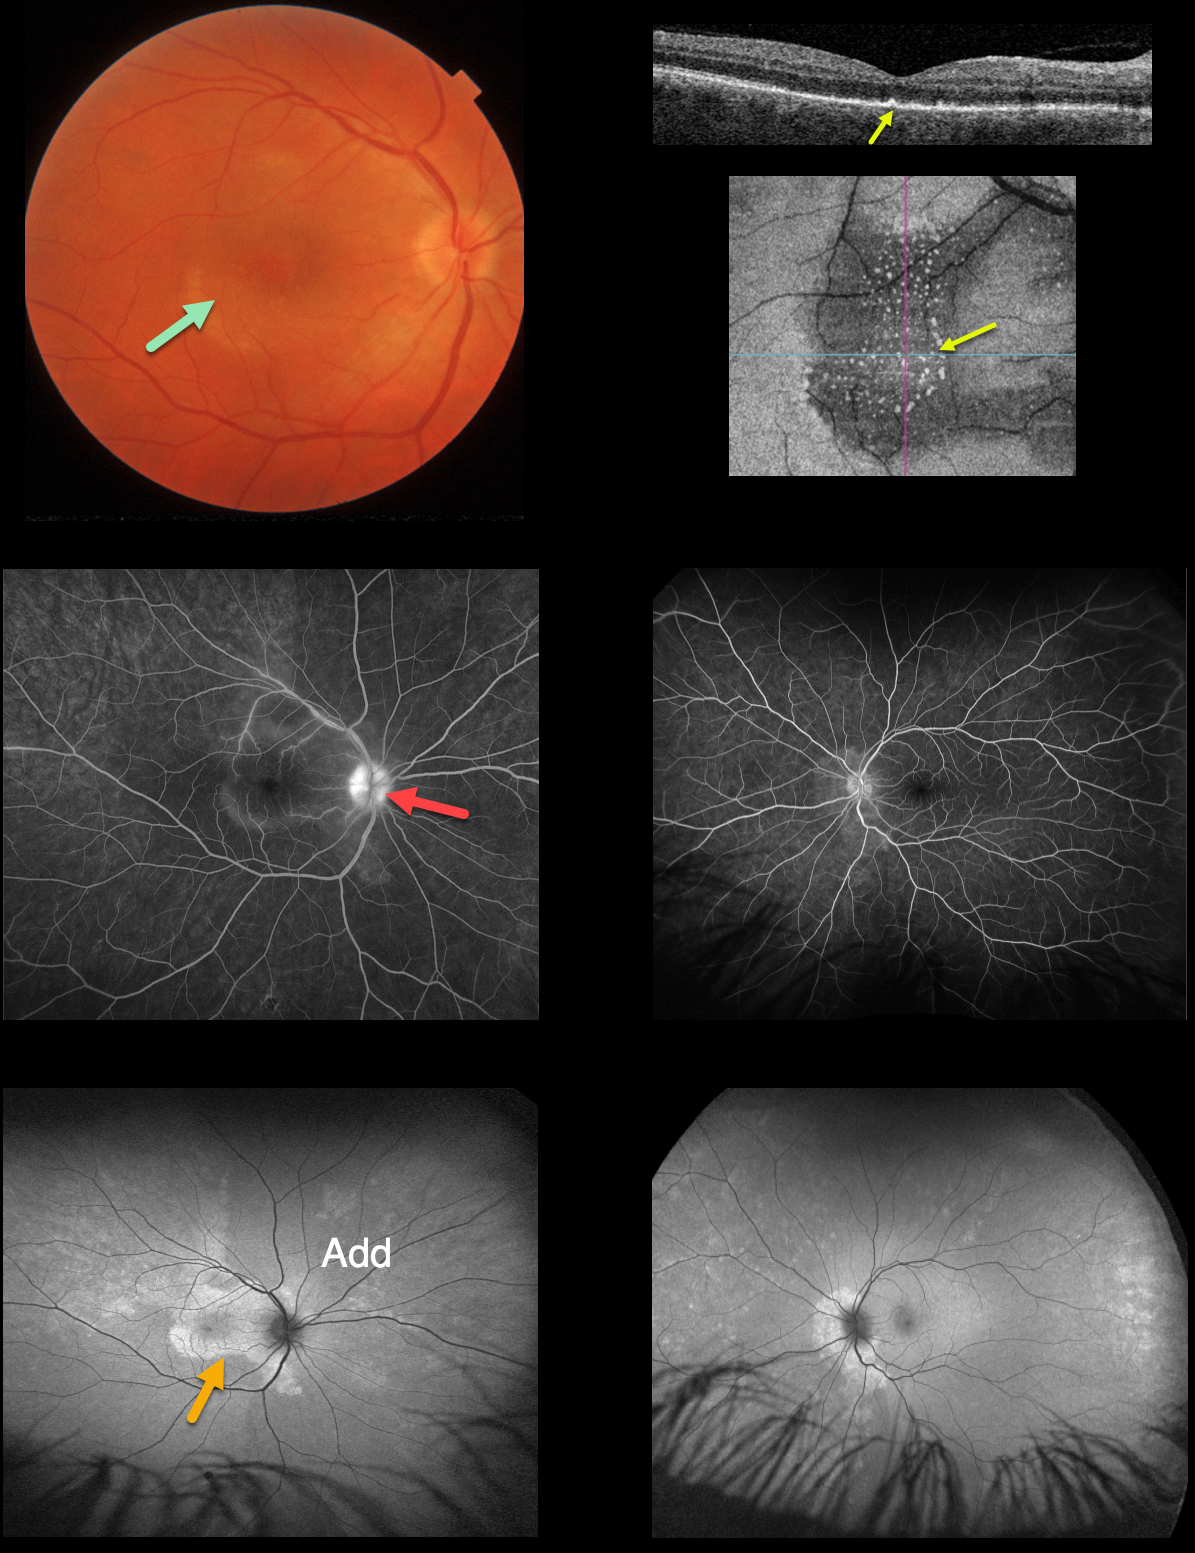
This 49YOM presented with a one-week history of blurred central vision in his right eye. There was no past medical history.
Vision was 20/400 OD and 20/25 OS. Anterior segments were normal. An oval, whitish submacular lesion was noted, and the optic nerve also appeared mildly swollen in the right eye.
OCT scanning of the right macula shows numerous, needle-like projections extending from the RPE into the outer retina. En face imaging best shows the hyperreflective outer retinal opacities.
Fluorescein angiography shows staining of the right nerve, mild peripapillary subretinal staining OU, and macular staining OD.
Fundus autofluorescence (FAF) shows much more extensive findings than those noted clinically, with peripapillary hyper-FAF OU, macular hyper-FAF OD corresponding to the placoid lesion, and peripheral hyperreflective dots bilaterally.
Treponema pallidum antibodies were reactive, with a high quantitative RPR (1:32). He was started on parenteral penicillin.
Learning Points:
Ocular manifestations of syphilis vary widely and include virtually all variations of anterior and posterior segment inflammation, including a recently described presentation as the multiple evanescent white dot syndrome phenotype (Russel et al Int Ophthalmol 2020;40:627-738). Hence, the reason it’s been dubbed the great imitator or masquerader.
One of the more common presentations is placoid chorioretinitis (Eandi et al., Retina 2012;32:1915-1941), which was evident on FAF imaging in our patient.



