

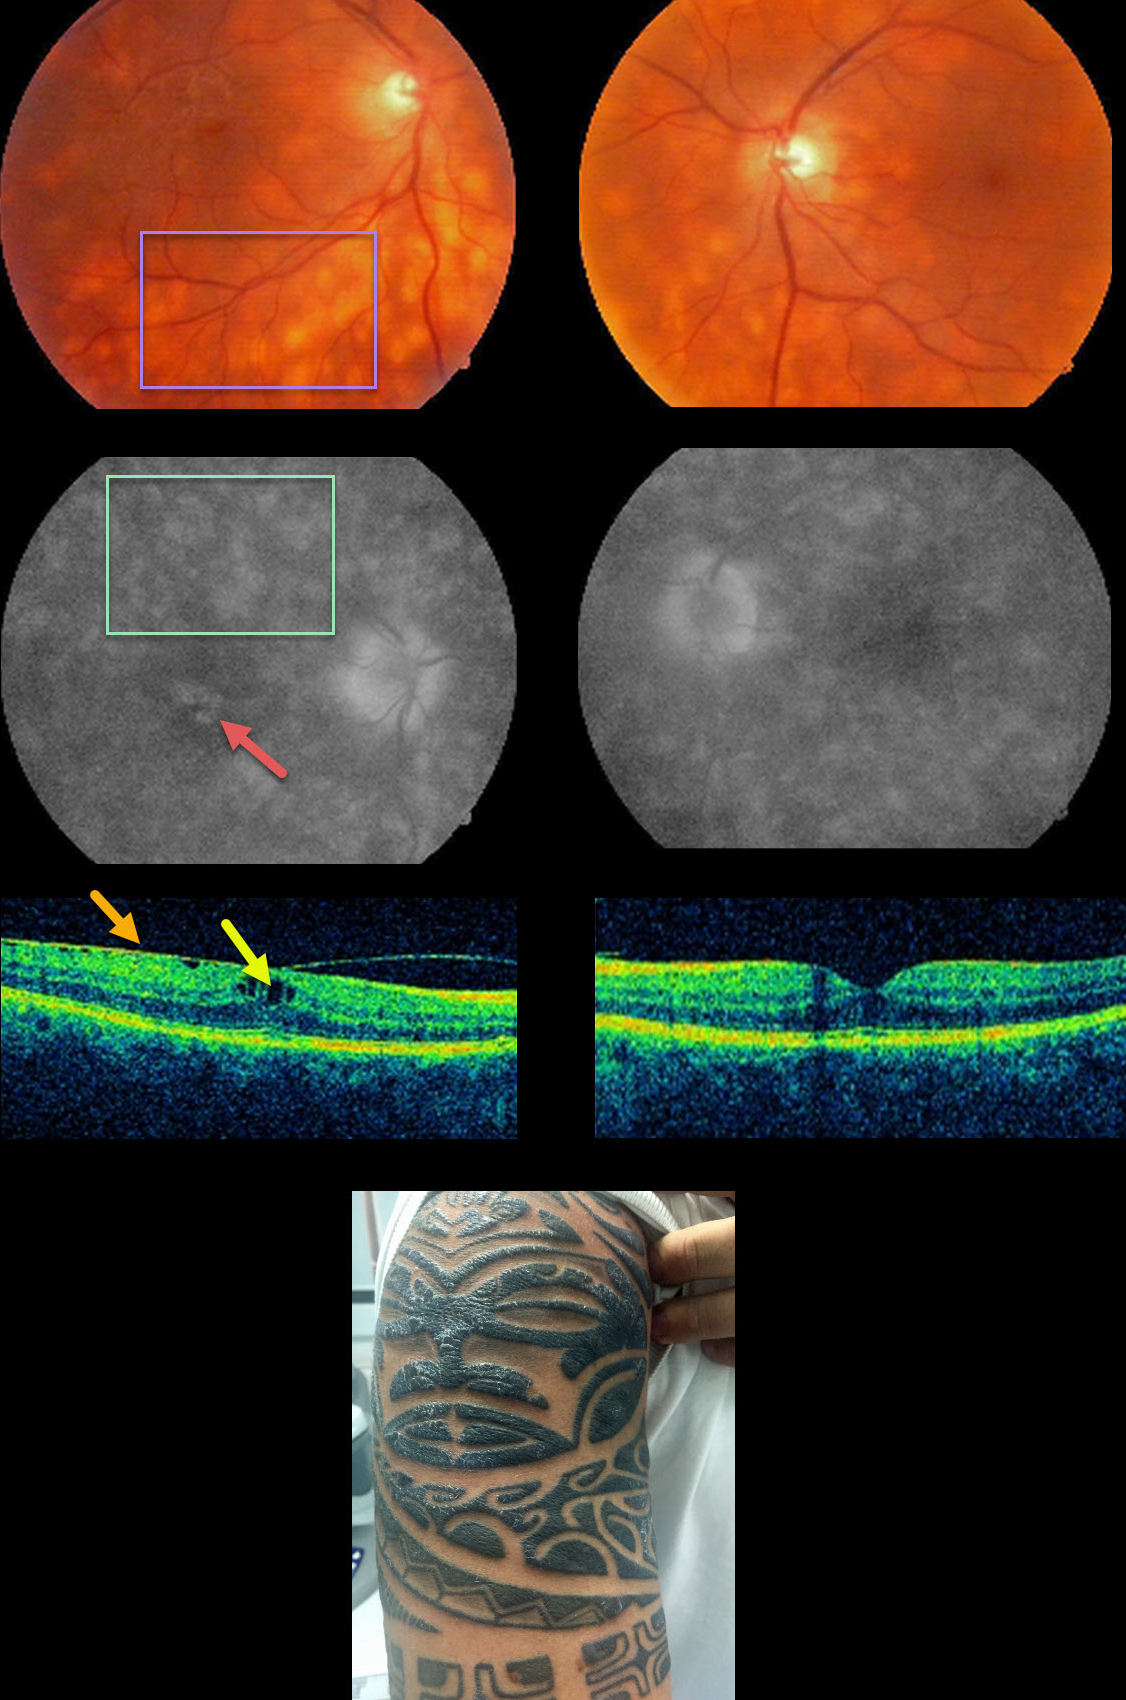
This 39YO male presented with bilateral floaters and a several-year history of intermittent panuveitis. He had a history of treated hepatitis C.
Vision was 20/25 OD and 20/20 OS. Anterior segments were normal. There was mild bilateral vitritis and scattered amelanotic subretinal lesions in each posterior pole.
Fluorescein angiography shows staining of these lesions with cystoid leakage in his right macula. OCT scanning shows a mild epiretinal membrane with cystoid edema OD. The initial differential diagnosis included birdshot chorioretinopathy and sarcoidosis.
HLA-A29 was negative, but on further questioning, he told us that the tattoos on his arms always became swollen and painful prior to the recurrent uveitis.
A biopsy of one of the inflamed tattoos revealed inflammation granulomatosa. The granulomas were classified as foreign-body or sarcoid-type reactions.
However, the sarcoidosis workup, including ACE, chest X-ray, and chest CT, was all normal. He is being treated as needed with oral and topical steroids.
Learning Points:
Tattoo pigments are known to produce mast cell activation and to provoke cellular lysis after phagocytosis. Intradermal injection of melanin, interphotoreceptor retinoid-binding protein, and S-antigen is known to produce a granulomatous anterior or pan-uveitis (see Ostheimer et al, AJO 2014;158:637-643). The uveitis can be controlled with systemic steroids and/or immunosuppressants.



