

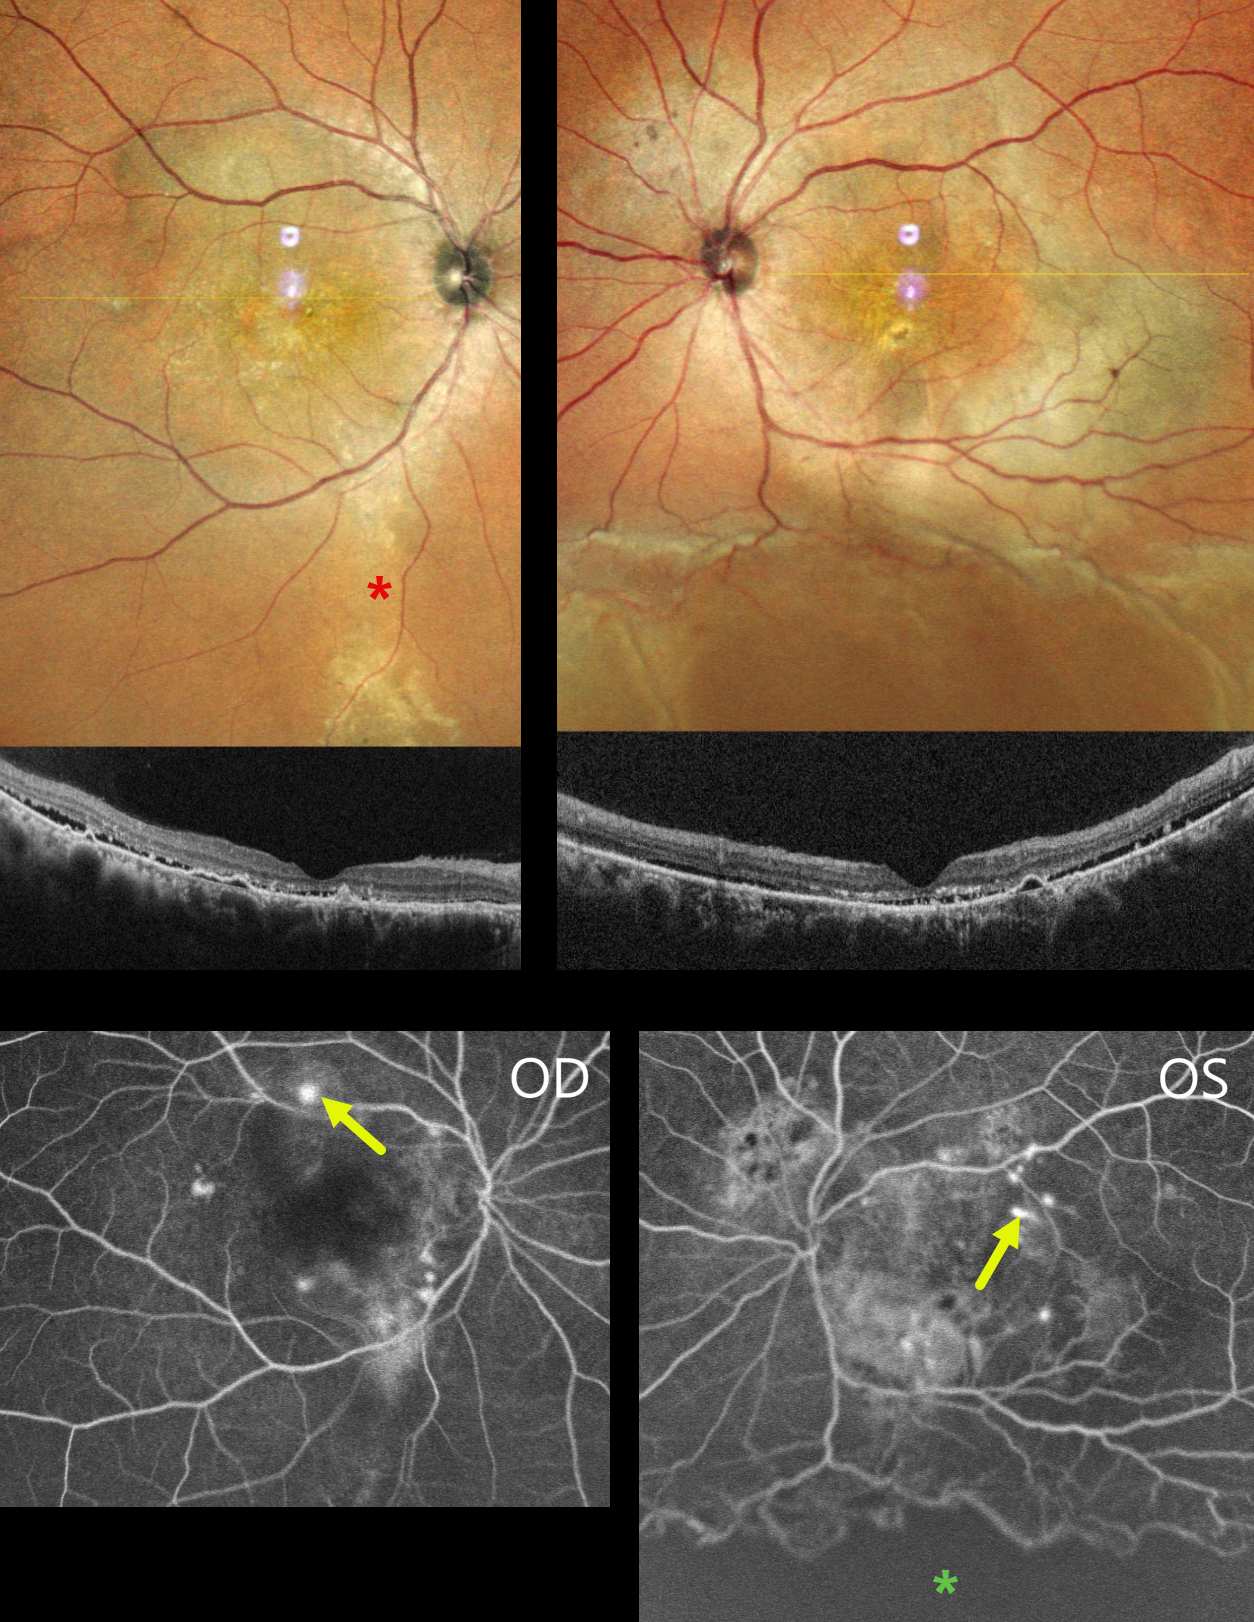
This 39YO male presented with 4 months of bilateral vision loss. He was diagnosed elsewhere with chronic idiopathic central serous chorioretinopathy (ICSC) and was placed on azathioprine and spironolactone 3 months earlier. There was no history of steroid use or injections. Vision was 20/120 OD and 20/200 OS.
MultiColor imaging shows macular pigmentary changes that extend in a gutter inferiorly OD. Diffuse macular pigmentary changes are noted in his left eye that communicate with an inferior exudative retinal detachment. OCT scanning shows shallow subretinal fluid with hyperreflective shed outer segments, outer retinal hyperreflective foci, and RPE detachments. Fluorescein angiography shows bilateral multifocal subretinal blot leakage. A broad area of ischemia is present overlying the inferior detachment of the OS.
Mantoux skin testing (15x18mm) and QuantiFERON-TB Gold testing were positive. Chest CT showed fibrotic strands in the right lung. He was referred for systemic antituberculosis treatment. A week later, his local ophthalmologist reported that his vision and retinal findings improved, but he was then lost to follow-up.
Learning Points:
Our patient presented with severe bilateral idiopathic central serous chorioretinopathy (ISCS) with multifocal leaks in each eye and a secondary exudative detachment in his left eye. There are rare case reports of TB occurring in patients with ICSC, and these are likely coincidental findings (Khan et al, BMJ Case Rep 2017:bcr-2016-216471).



