

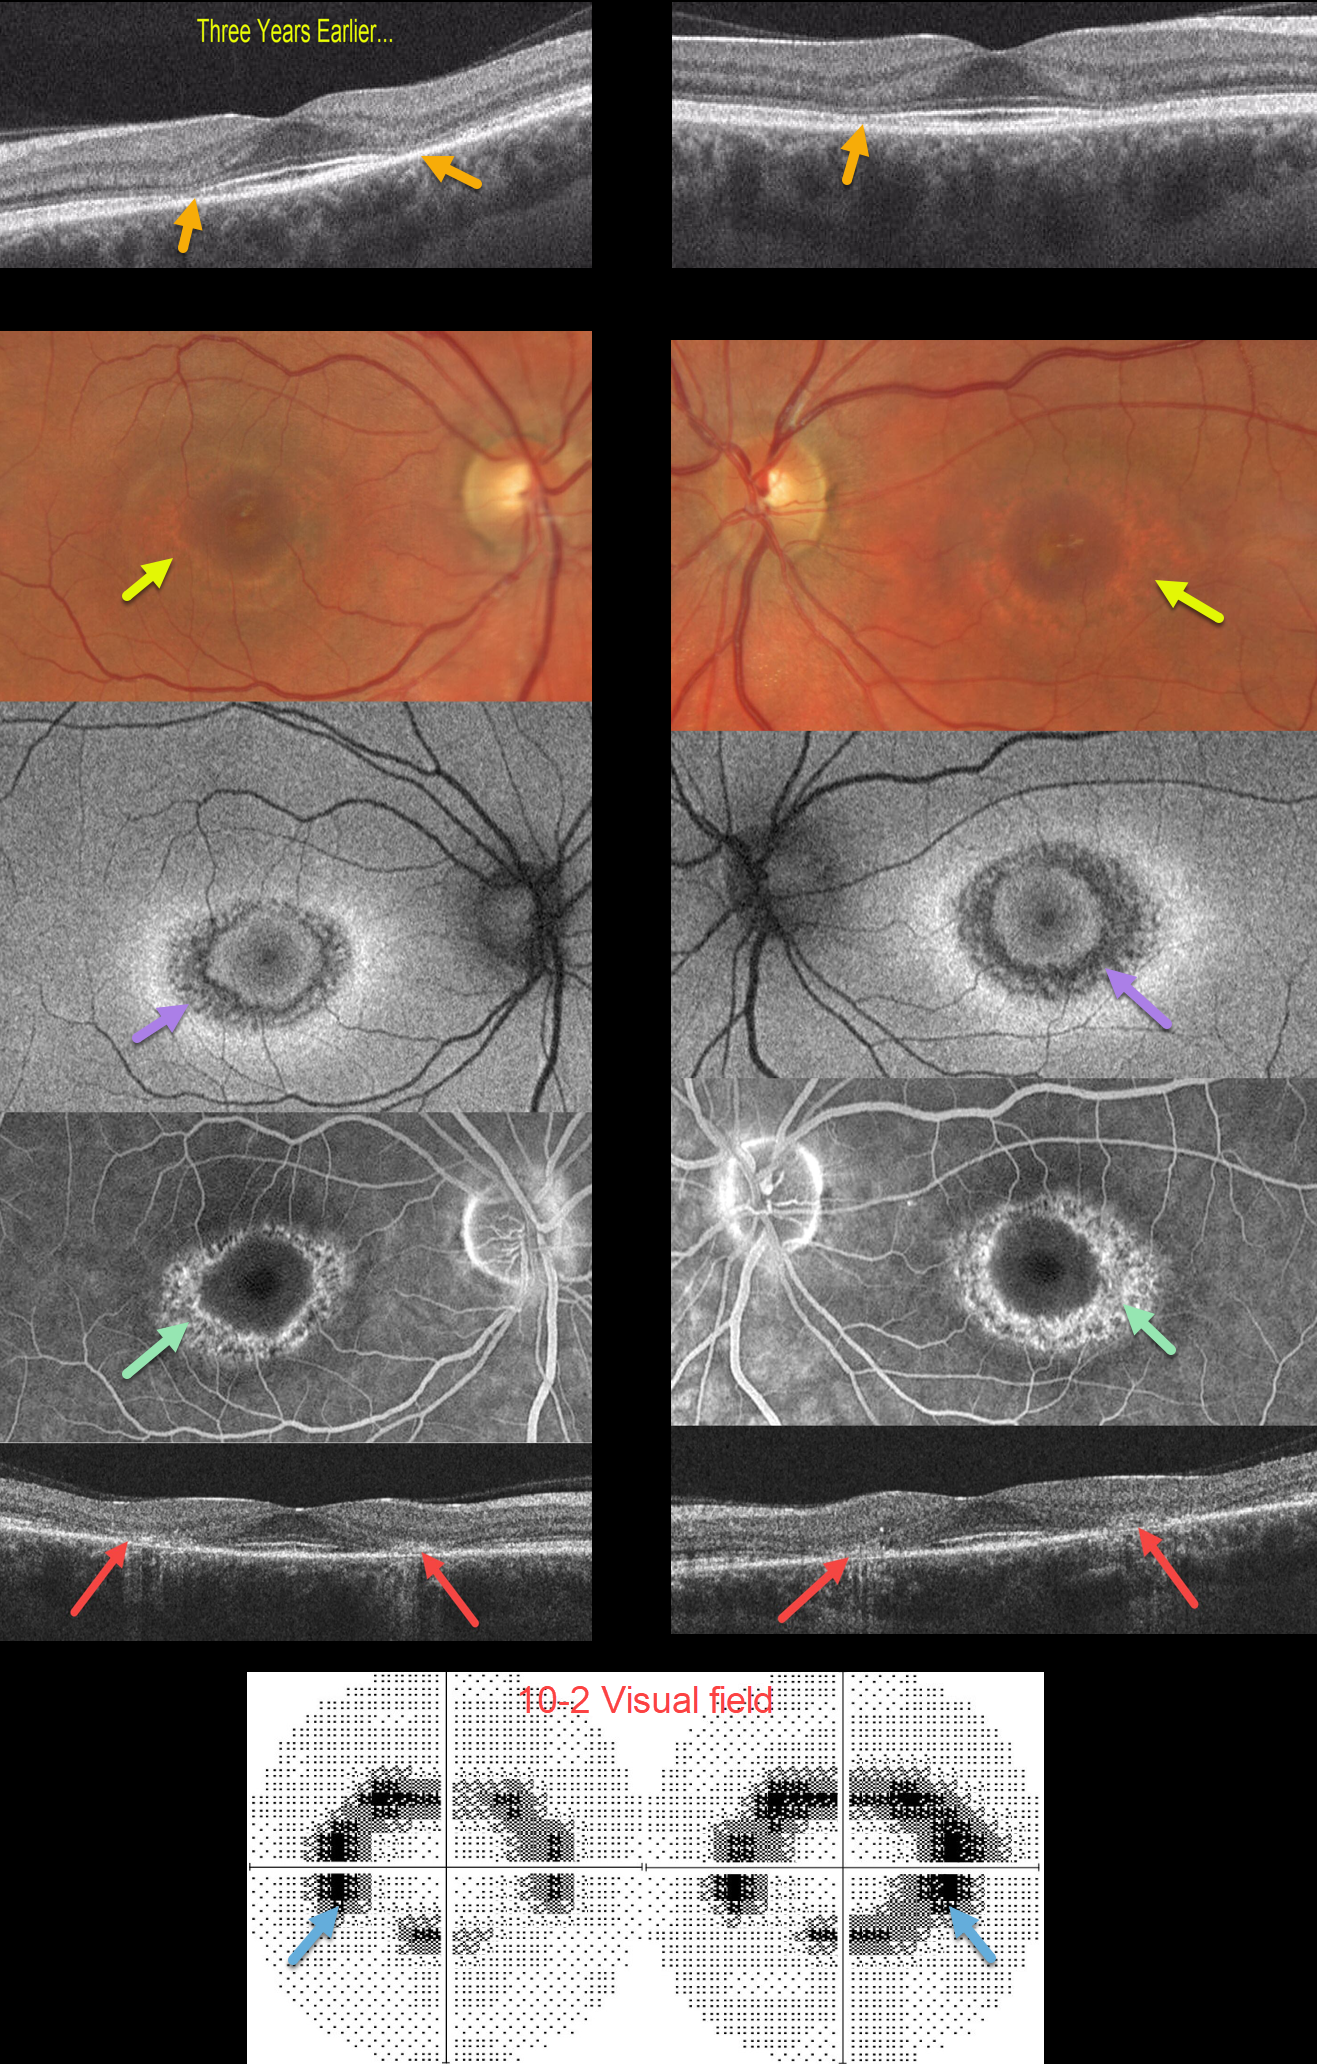
This 43YO female was seen in 2019 by a general ophthalmologist at an outside practice with somewhat subtle paracentral outer retinal atrophy. Vision was 20/20 without symptoms. She was taking Plaquenil for 8 years for rheumatoid arthritis. Unfortunately, these OCT findings for early Plaquenil toxicity were missed.
She was subsequently lost to followup until she presented 3 years later. Although vision remained at 20/20 OU, she now complained of donut-shaped scotomas bilaterally. There were now dramatic and classic findings for Plaquenil toxicity captured on multimodal imaging.
Optos color imaging shows a bullseye pattern of pigmentary loss encircling each fovea. Fundus autofluorescence shows hypo-FAF and fluorescein angiography shows window defects corresponding to these bullseye changes.
OCT scanning shows symmetrical paracentral outer retinal and RPE atrophy. Finally, 10-2 visual fields show a ring of bilateral paracentral visual field loss.
Learning Points:
Current screening guidelines should make Plaquenil toxicity a thing of the past. Last revised in 2016, the American Academy of Ophthalmology (AAO) recommends that a baseline exam be performed before starting the medication with annual screenings beginning at least 5 years after initiating treatment, unless major risk factors are present. However, in practicality, patients are usually screened yearly once they are placed on this medication.
Optical coherence tomography (OCT) is performed annually, looking for outer retinal findings, including ellipsoid zone loss. Humphrey 10-2 visual field testing (24-2 for Asians since their macular involvement is usually more peripheral) is needed annually as well, since about 10% of patients will have field loss despite normal examinations and OCT testing.
Plaquenil dosing should also be based on real, not ideal, weight to better predict the optimal dose. See Marmor et al Ophthalmology 2016;123:1386-1394 for the full screening guidelines.



