

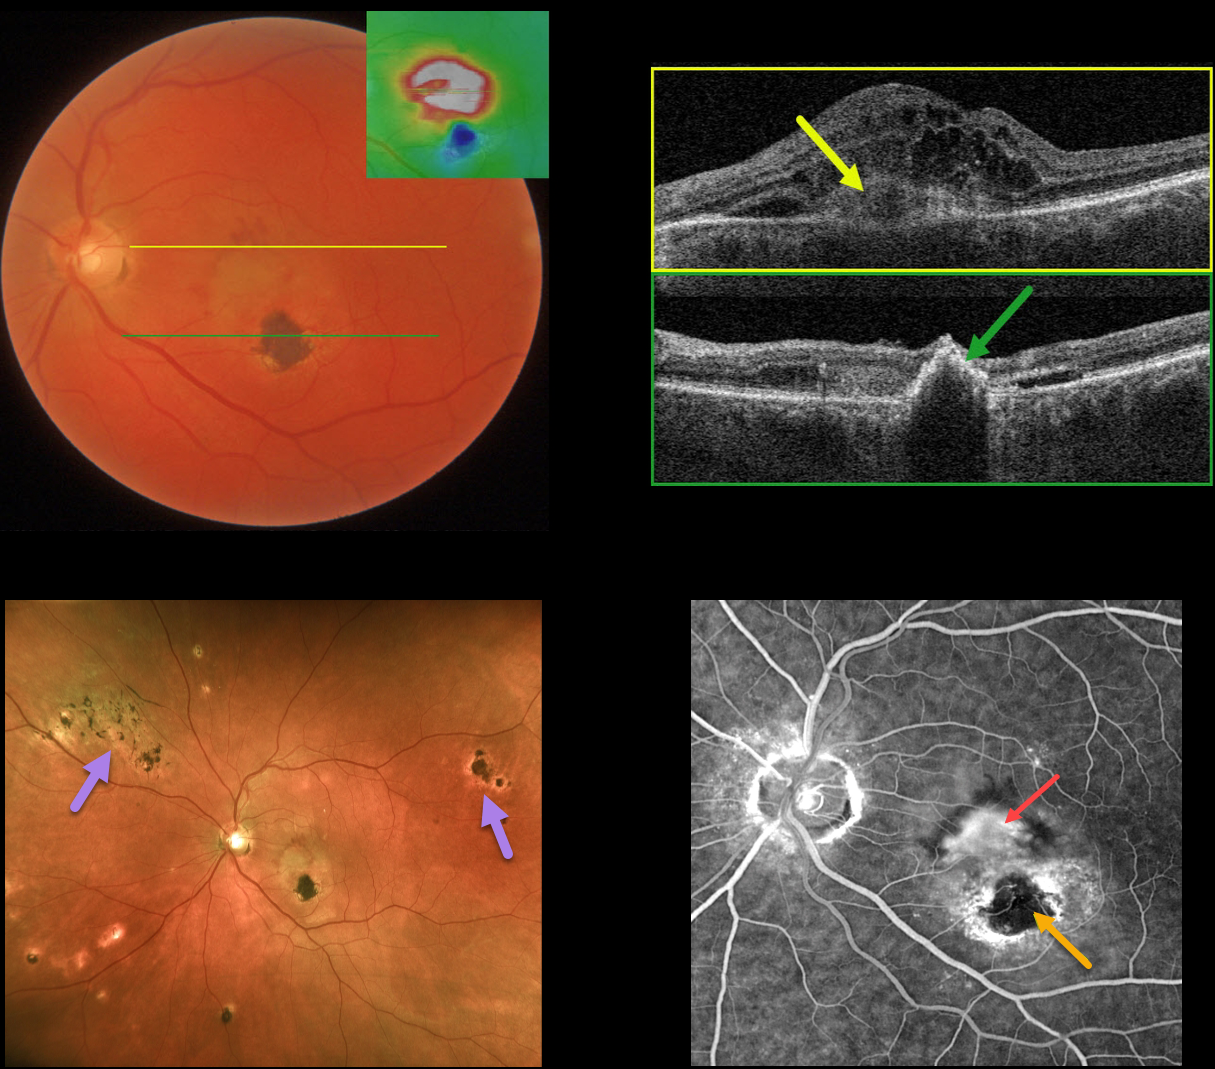
This 62YO male presented with acute vision loss of 20/400 in his left eye. He gave a history of thermal laser in this eye about 25 years earlier for ocular histoplasmosis.
Color photography shows opaque macular fluid with some dots of superior subretinal blood.
OCT map shows central and superior retinal thickening. OCT B-scan through the macular center shows a type 2 macular neovascularization (MNV, located above the RPE) with marked overlying macular edema and trace nasal subretinal fluid. A B-scan through the inferior macular laser scar shows a full-thickness, markedly hyperreflective lesion.
Fluorescein angiography shows a leaking subfoveal MNV with a central hypofluorescent laser scar with surrounding staining.
Optos ultrawidefield imaging provides a broader perspective on macular, peripapillary, and peripheral chorioretinal scarring.
An intravitreal Avastin injection was given, and this will be followed by half-fluence photodynamic therapy to try to minimize the treatment burden.
Learning Points:
Ocular histoplasmosis is caused by the Histoplasmosis capsulatum fungus, which is commonly found in soil contaminated by bird or bat droppings.
It is seen worldwide, but in the United States, it is most often seen in the Ohio-Mississippi River valley. Most people in endemic areas inhale the organism’s spores early in life, with only a few percent developing asymptomatic chorioretinal scars.
A small percentage of these will develop MNV later in life. Treatment is similar to wet AMD, with anti-VEGF therapy usually being the first-line therapy. Unlike AMD, these patients often do not require ongoing injections.
Photodynamic therapy can help minimize treatment burden, and thermal laser therapy remains a good option for more peripheral macular lesions.



