

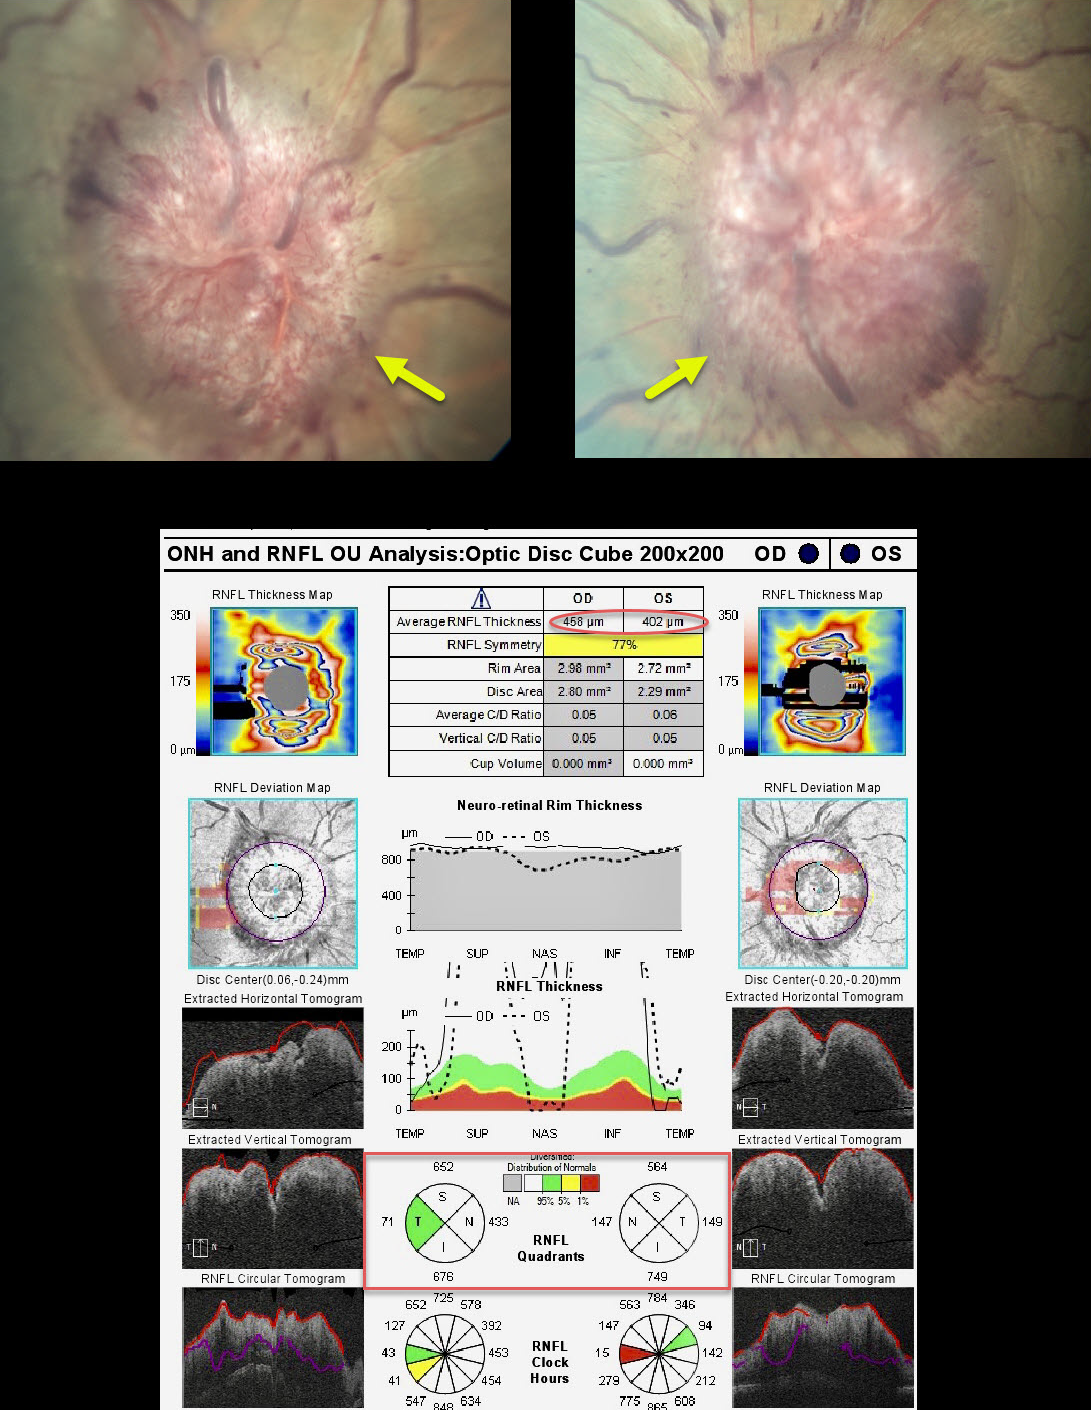
This patient presented with diplopia from bilateral esotropia and reduced abduction in each eye due to sixth nerve palsies. There were no headaches or visual disturbances.
Her nerves showed severe papilledema with severe retinal nerve fiber layer thickening on OCT.
An MRI showed no mass lesions, but her lumbar puncture opening pressure was 41 cm H2O.
Despite an aggressive weight loss regimen and oral acetazolamide, her intracranial pressure remained elevated and required a ventriculoperitoneal shunt.
Learning Points:
Idiopathic intracranial hypertension (pseudotumor cerebri) can occasionally cause a downward displacement of the brainstem, stretching the sixth nerve as it exits the pons towards Dorello’s canal at the apex of the petrous bone.



