

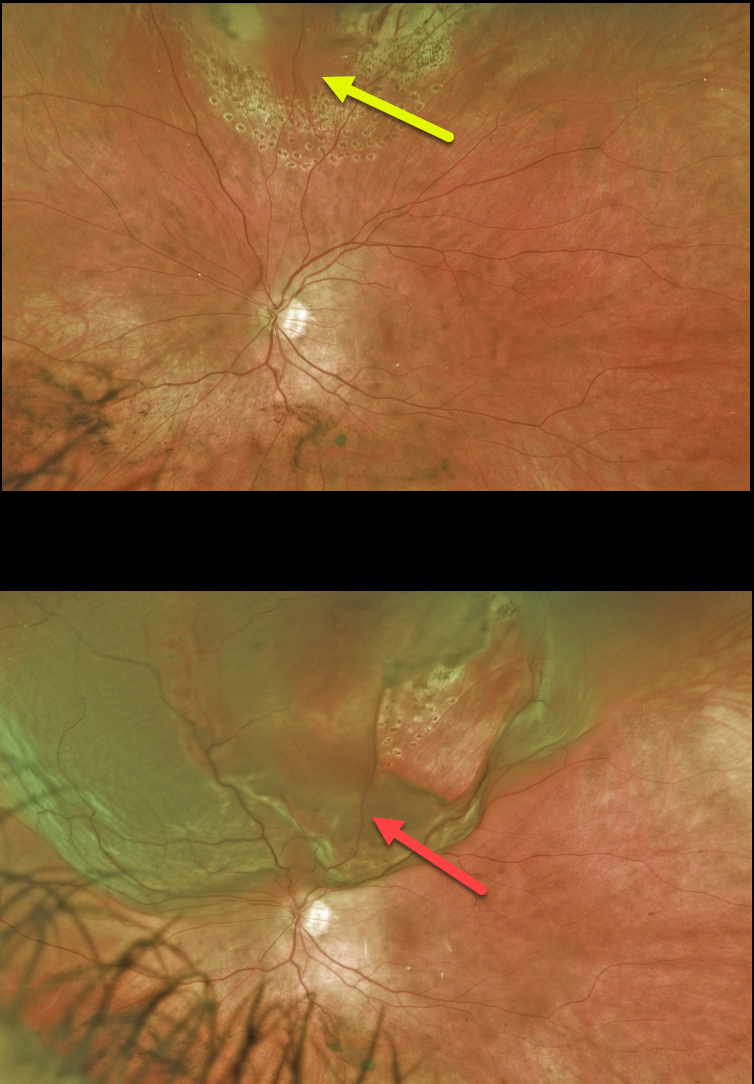
This 37YO female presented with a symptomatic superior retinal tear in her left eye. The posterior and lateral edges of the break were surrounded with thermal laser. The anterior edges could not be reached with the laser, so these were surrounded with cryotherapy. One week later, pigmented scarring surrounds the treated tear.
Three weeks later, she presented with a few days of inferior visual field loss. She now has a superior macula-on rhegmatogenous retinal detachment (RRD) due to lifting off the originally treated tear. Vitrectomy surgery was performed the following day.
Learning Points:
Untreated symptomatic retinal tears have a high risk for RRD. Retinopexy, either with thermal laser or cryotherapy, must completely surround the break and, for more anterior lesions, ideally extend to the ora.
Patients must be followed closely, especially during the first month, due to the risk of additional breaks or retinal detachment. A firm chorioretinal adhesion takes several weeks to form (Yoon and Marmor, Ophthalmology 1988;95:1385-1388). Patients must always be cautioned to return immediately for new flashes, floaters, or vision loss.



