

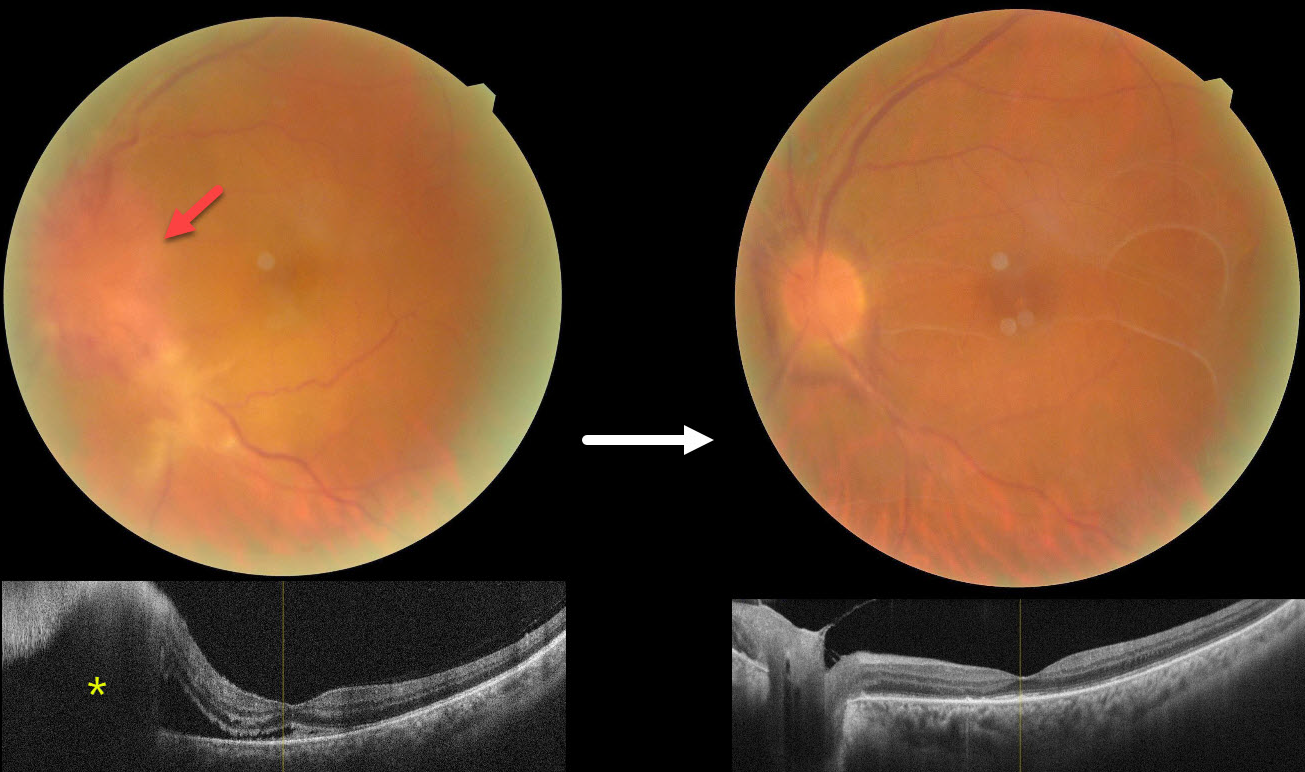
This 52YO male presented with 3 weeks of vision loss in his left eye. He has a history of diabetes, hypertension, and HIV. He was diagnosed elsewhere with optic neuritis and started on intravenous methylprednisolone with no improvement. Vision was 20/30 in his normal OD and counting fingers OS. There was a mild nongranulomatous anterior uveitis OS on slit lamp examination.
Color photography shows a markedly swollen nerve with possible retinitis extending inferotemporally. OCT scanning confirms the disc elevation with subretinal fluid extending beneath the nasal macula.
On further questioning, there was a recent history of a genital chancre, and the treponema pallidum hemagglutination assay was positive for syphilis. Following a 2-week course of parenteral penicillin, vision improved to 20/120 with marked improvement in the posterior segment findings. Unusual premacular vitreous membranes are noted.
Learning Points:
Ocular manifestations of syphilis vary widely and include virtually all variations of anterior and posterior segment inflammation. In our experience, placoid syphilis is the most common posterior segment presentation, although a recent systematic review and meta-analysis found papillitis to be the most reported finding in syphilitic uveitis (Zhang et al, J of Ophthalmology 2017;1; 6594849). Papillitis can be isolated or associated with other findings.
Any patient who tests positive for syphilis should always be checked for HIV since coinfection, as in our patient, is common.



