

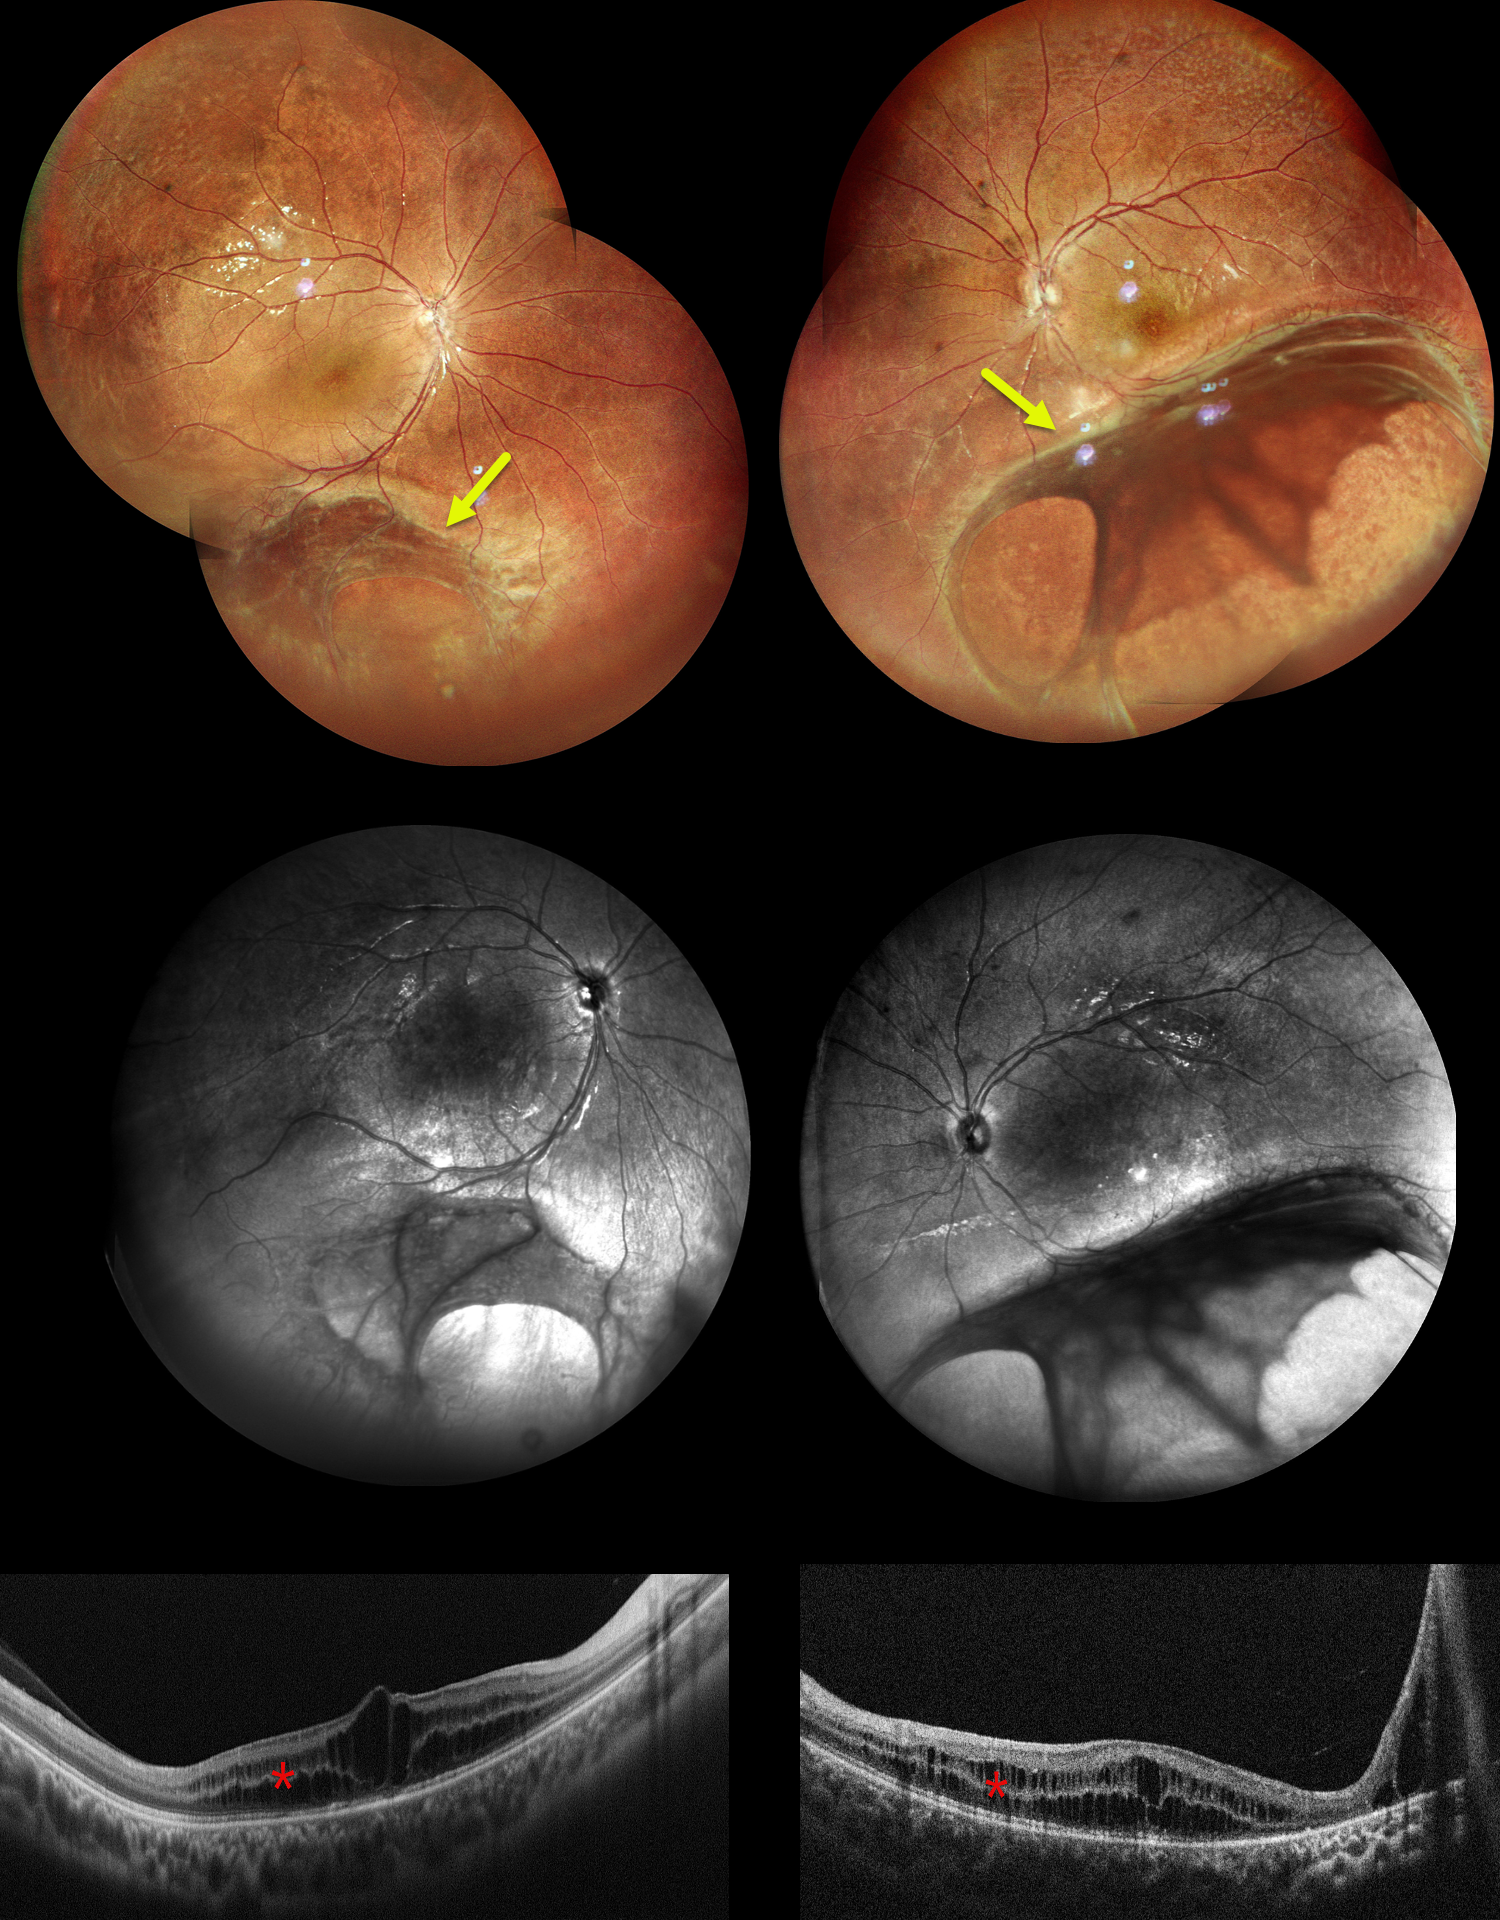
This 9YO boy presented with decreased vision in each eye since early childhood. Vision was 20/80 OU.
Pseudocolor SLO imaging shows blunted foveal reflexes due to inner and outer nuclear layer schisis on OCT. Widefield imaging shows extension of the schisis cavities into the inferotemporal periphery, involving the inner retina with vitreous veils. These changes are best seen in the infrared images. Our patient’s 13YO brother was examined the same day and had similar fundus findings.
Both brothers were prescribed topical carbonic anhydrase inhibitors (dorzolamide) and asked to follow up in 3 months. Genetic testing was recommended.
Learning Points:
Sex-linked retinoschisis is caused by a hemizygous mutation in the RS1 gene, which is located on the X chromosome and encodes for retinoschisin, a protein secreted by photoreceptors that is involved in intercellular adhesion and likely in retinal cellular organization (Heymann et al, Progress Retinal Eye Research 2023;95:101147). Although usually transmitted as an X-linked recessive disorder in males with an incidence of 1 in 15,000 to 30,000, it can also sometimes affect females.
The characteristic features include “spoke-wheel” foveoschisis and peripheral schisis with vitreous veils. Over time, the macular schisis flattens with secondary atrophy, and vision usually levels off at about 20/100. Patients can develop spontaneous vitreous hemorrhage and rhegmatogenous retinal detachment from peripheral schisis. Although there is no specific treatment, topical carbonic anhydrase inhibitors may decrease the foveal thickness and possibly help minimize foveal atrophy (see Andreuzzi et al Retina 2017;37:1555-1561).



