

Acute Macular Neuroretinopathy (AMN)
<< Back to Cases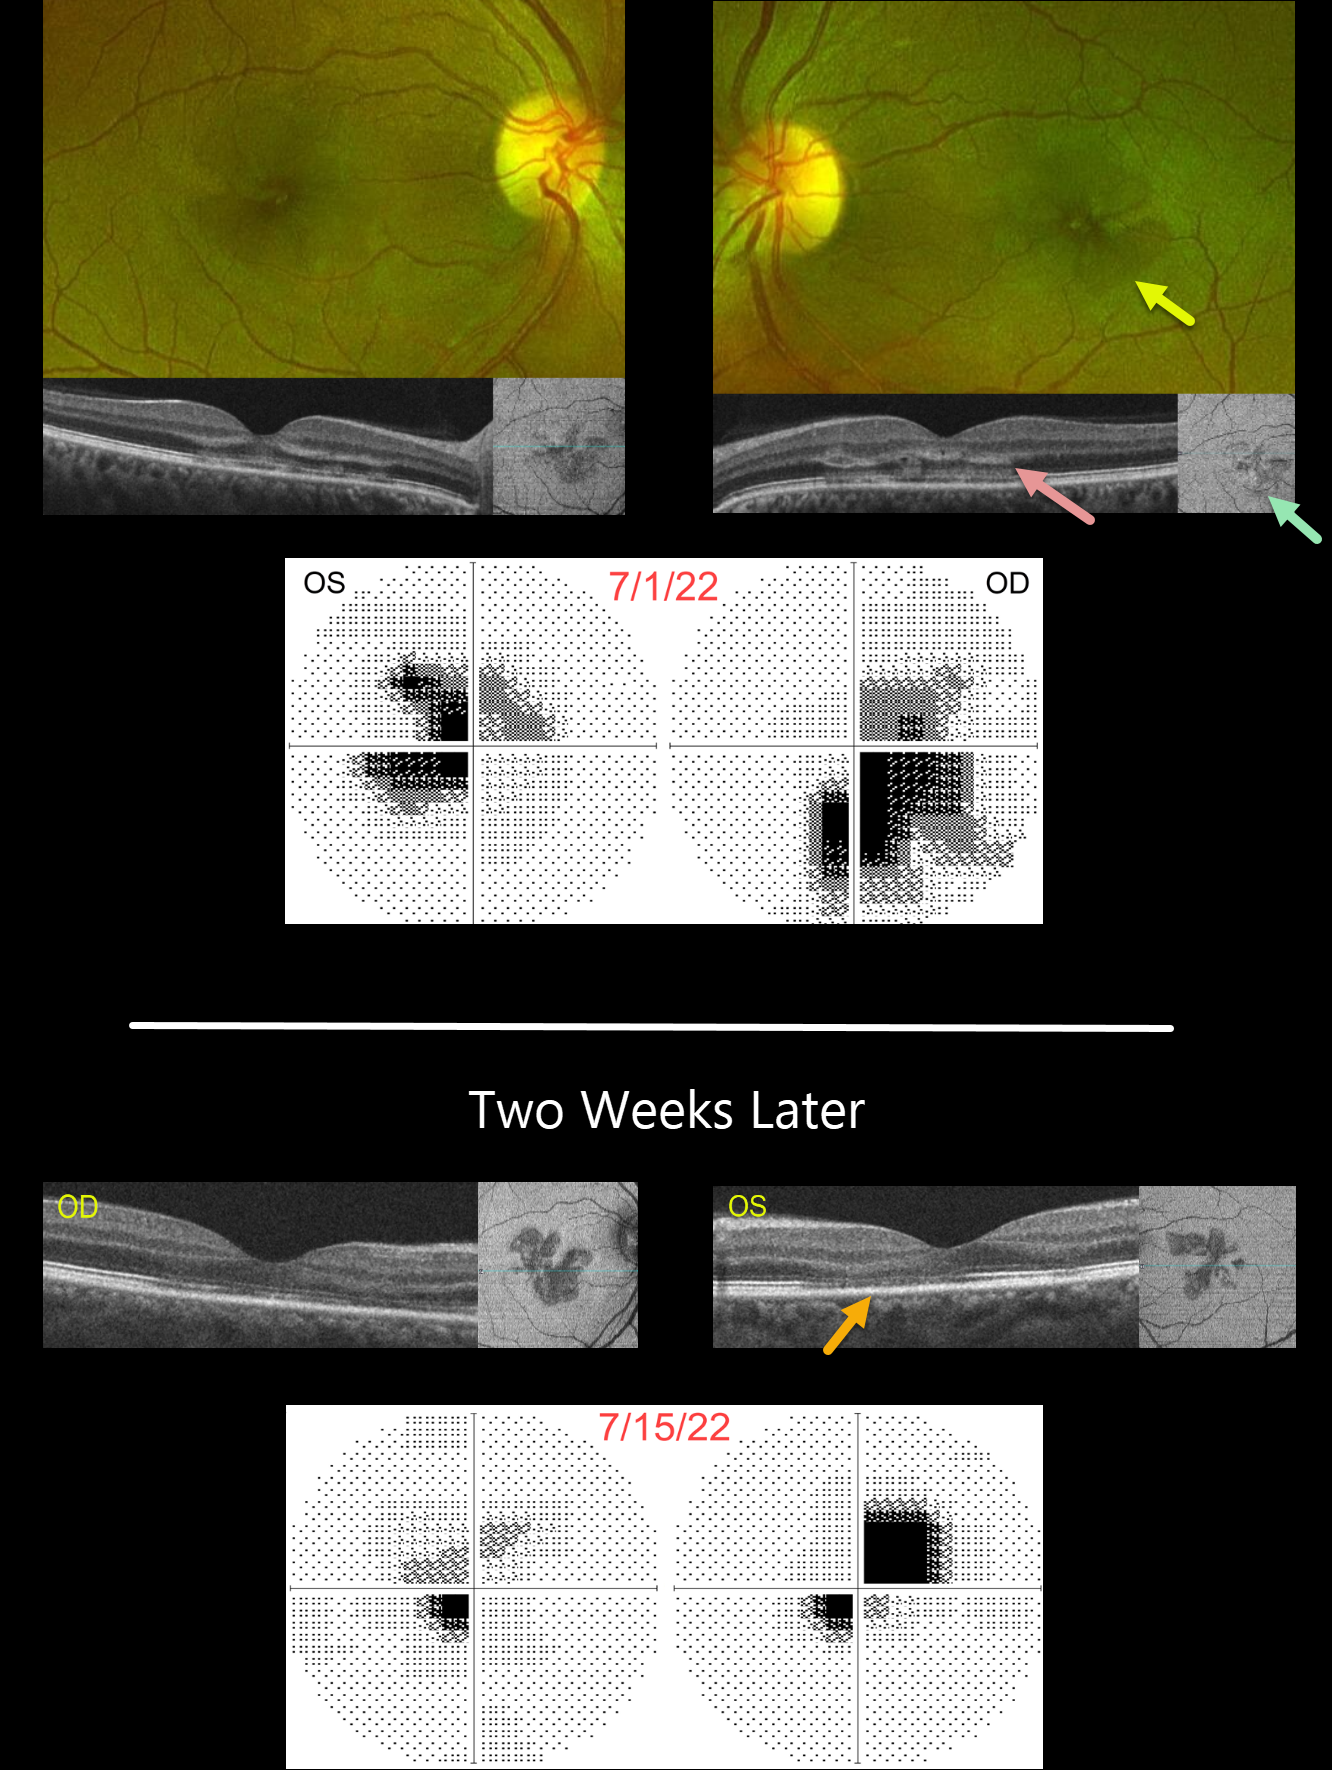
ACUTE MACULAR NEURORETINOPATHY (AMN)
Will Gibson
Originally posted on @retina.rocks February 19, 2024
This 41YO female presented with recent bilateral paracentral scotomas and blurred vision. There was no prior ocular or past medical history. Vision was 20/50 OD and 20/100 OS.
Optos color RG imaging shows faint wedge-shaped lesions radiating outwards from each macular center. OCT B-scanning shows variable patchy hyperreflectivity extending from the outer plexiform layer into the interdigitation zone. OCT en face imaging through the outer retina shows hyporeflective wedge lesions. Central 10-2 visual field testing shows bilateral paracentral scotomas.
Two weeks later, vision spontaneously improved to 20/60 OD and 20/25 OS. On OCT B-scanning, the outer retinal hyperreflective lesions are now replaced by secondary thinning with more prominent en face wedge lesions. The visual field scotomas are also improving.
Learning Points:
This case highlights many characteristic features of acute macular neuroretinopathy (AMN), an idiopathic disorder likely caused by compromise of the deep retinal capillary plexus.
Traditionally, the pathognomonic wedge-shaped AMN lesions are best seen with near-infrared reflectance, although we also find them easily imaged with en face OCT. With resolution, the acute lesions cause secondary outer retinal thinning.
Most patients are white, non-Latino females with a median age of 30 years. The most common associations are a flu-like prodrome and oral contraceptive use. Presenting acuity is usually good, coinciding with sparing of the sub-foveal areas. Roughly half of AMN cases are bilateral. There is typically moderate visual improvement over several months without treatment.
ACUTE MACULAR NEURORETINOPATHY (AMN)
Originally posted on @retina.rocks December 21, 2022
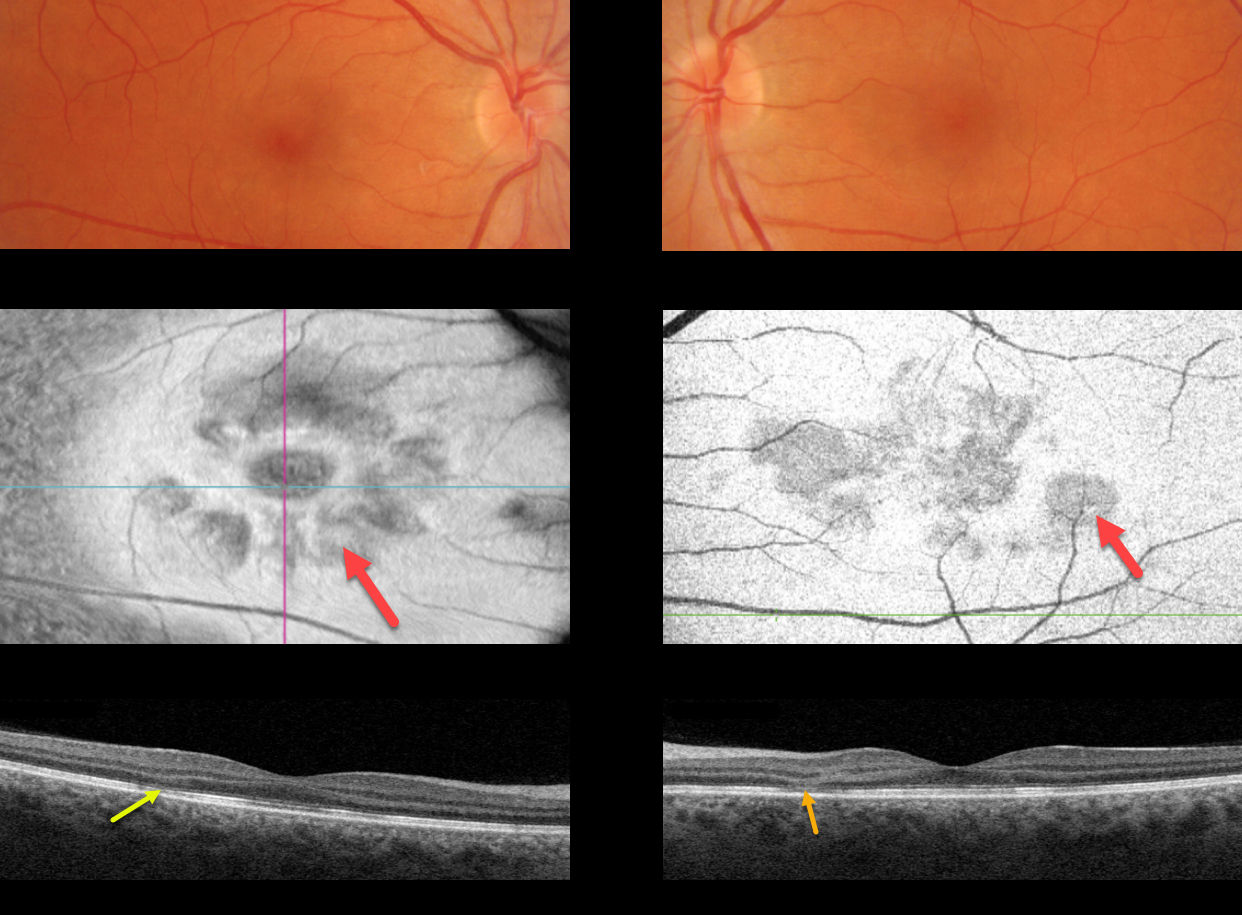
This 41YO female presented with acute bilateral central vision loss. Fundus photography shows very faint reddish-brown wedge-shaped lesions radiating from each fovea.
Swept-source en face imaging of the outer retina shows multiple hyporeflective wedge-shaped lesions radiating from the macular centers.
OCT B-scanning shows bilateral areas of outer nuclear layer thinning with hyperreflectivity associated with disruption of the ellipsoid zone and outer segment layers.
Learning Points:
This case highlights many characteristic features of acute macular neuroretinopathy (AMN), an idiopathic disorder likely caused by compromise of the deep retinal capillary plexus.
Multicolor and infrared imaging often highlight the typical wedge-shaped AMN lesions more effectively than color fundus photos, although the en face OCT images in our patient beautifully capture these pathognomonic findings.
Most patients are white, non-Latino females with a median age of 30 years. The most common associations are a flu-like prodrome and oral contraceptive use.
Presenting acuity is usually good, coinciding with sparing of the sub-foveal areas. Roughly half of AMN cases are bilateral. There is typically moderate visual improvement over several months without treatment.
ACUTE MACULAR NEURORETINOPATHY
Originally posted on @retina.rocks January 21, 2022
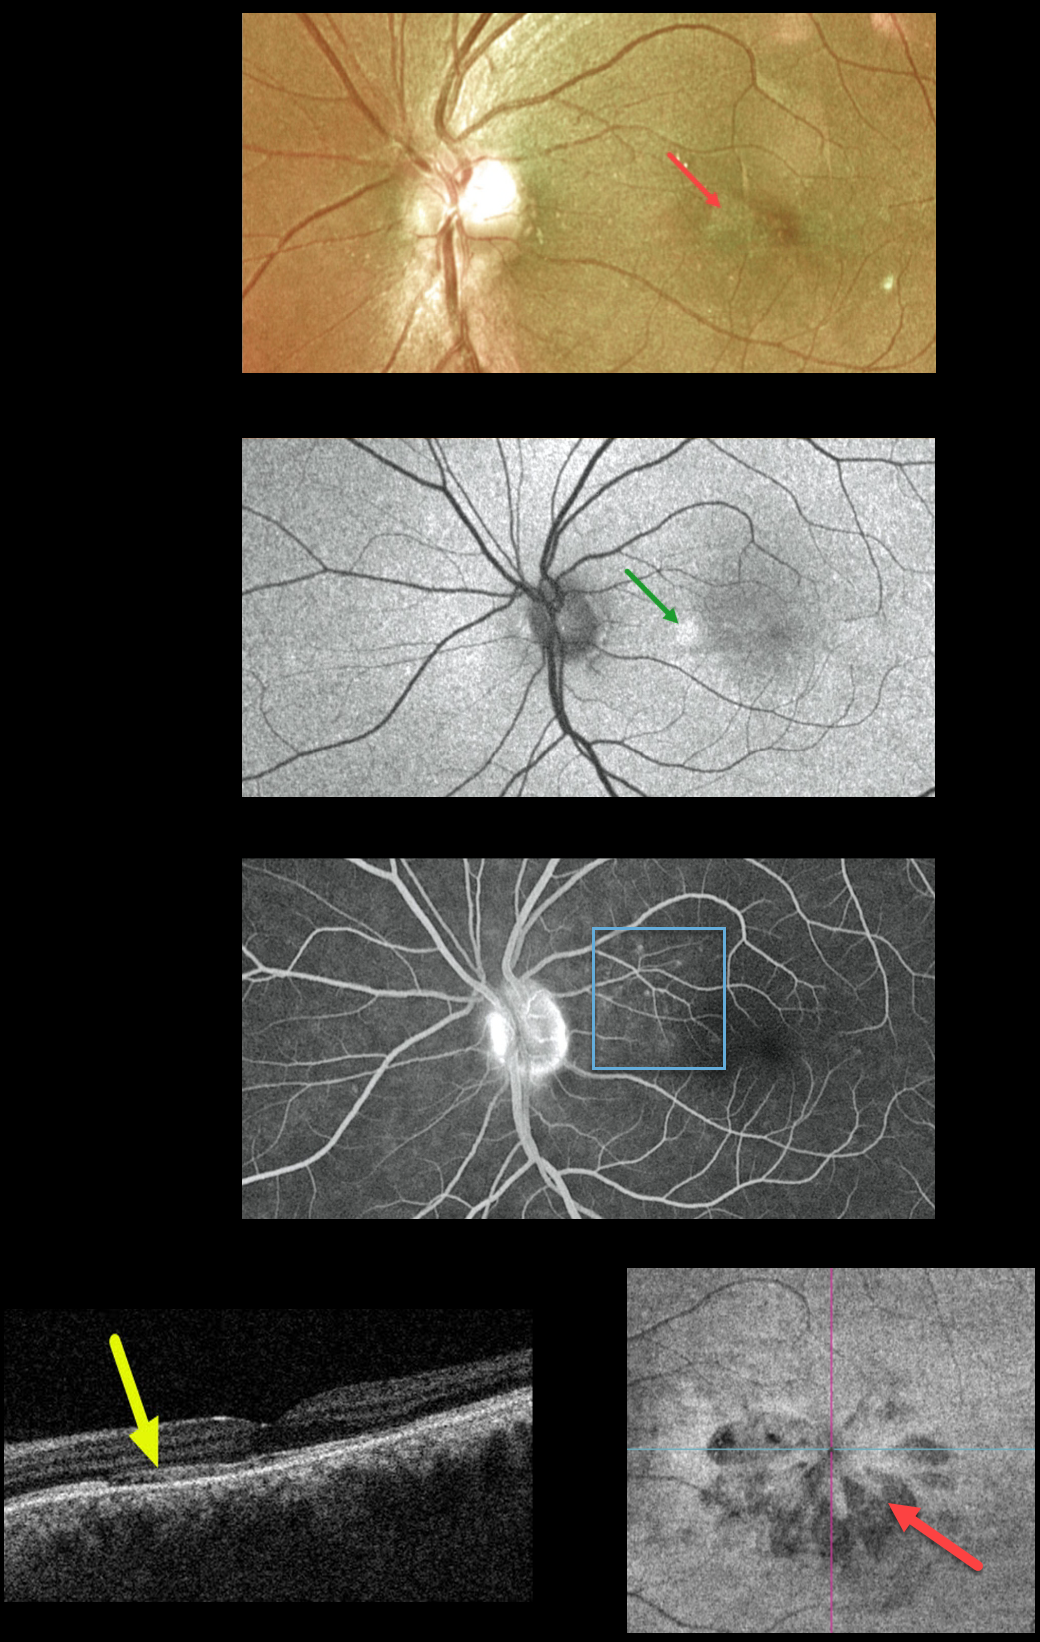
This 39YO male presented with 1 day of blurred vision in his left eye. Vision was 20/30 OU. Optos color imaging shows a wedge-shaped lesion radiating into the nasal fovea. Optos fundus autofluorescence (FAF) shows hyper-FAF in this area, and fluorescein angiography shows subtle areas of increased nasal macular hyperfluorescence.
Swept-source OCT shows attenuation of the ellipsoid zone and outer segment layers. En face imaging of the outer retina shows multiple hyporeflective wedge-shaped lesions radiating from the macular center. Findings in the right eye were completely normal.
Learning Points:
This case highlights many characteristic features of acute macular neuroretinopathy (AMN), an idiopathic disorder likely caused by compromise of the deep retinal capillary plexus.
Multicolor and infrared imaging often highlight the typical wedge-shaped AMN lesions more effectively than color fundus photos, although the Triton en face OCT image in our patient beautifully imaged these.
Most patients are white, non-Latino females with a median age of 30 years. Roughly half of AMN cases are bilateral. The most common associations are a flu-like prodrome and oral contraceptive use.
Presenting acuity is usually good, coinciding with sparing of the sub-foveal areas. There is typically moderate visual improvement over several months without treatment.
For a great AMN review, see Bhavsar et al, Surv Ophthalmology 2016;61:538-565.
ACUTE MACULAR NEURORETINOPATHY (AMN)
Originally posted on @retina.rocks May 28, 2021
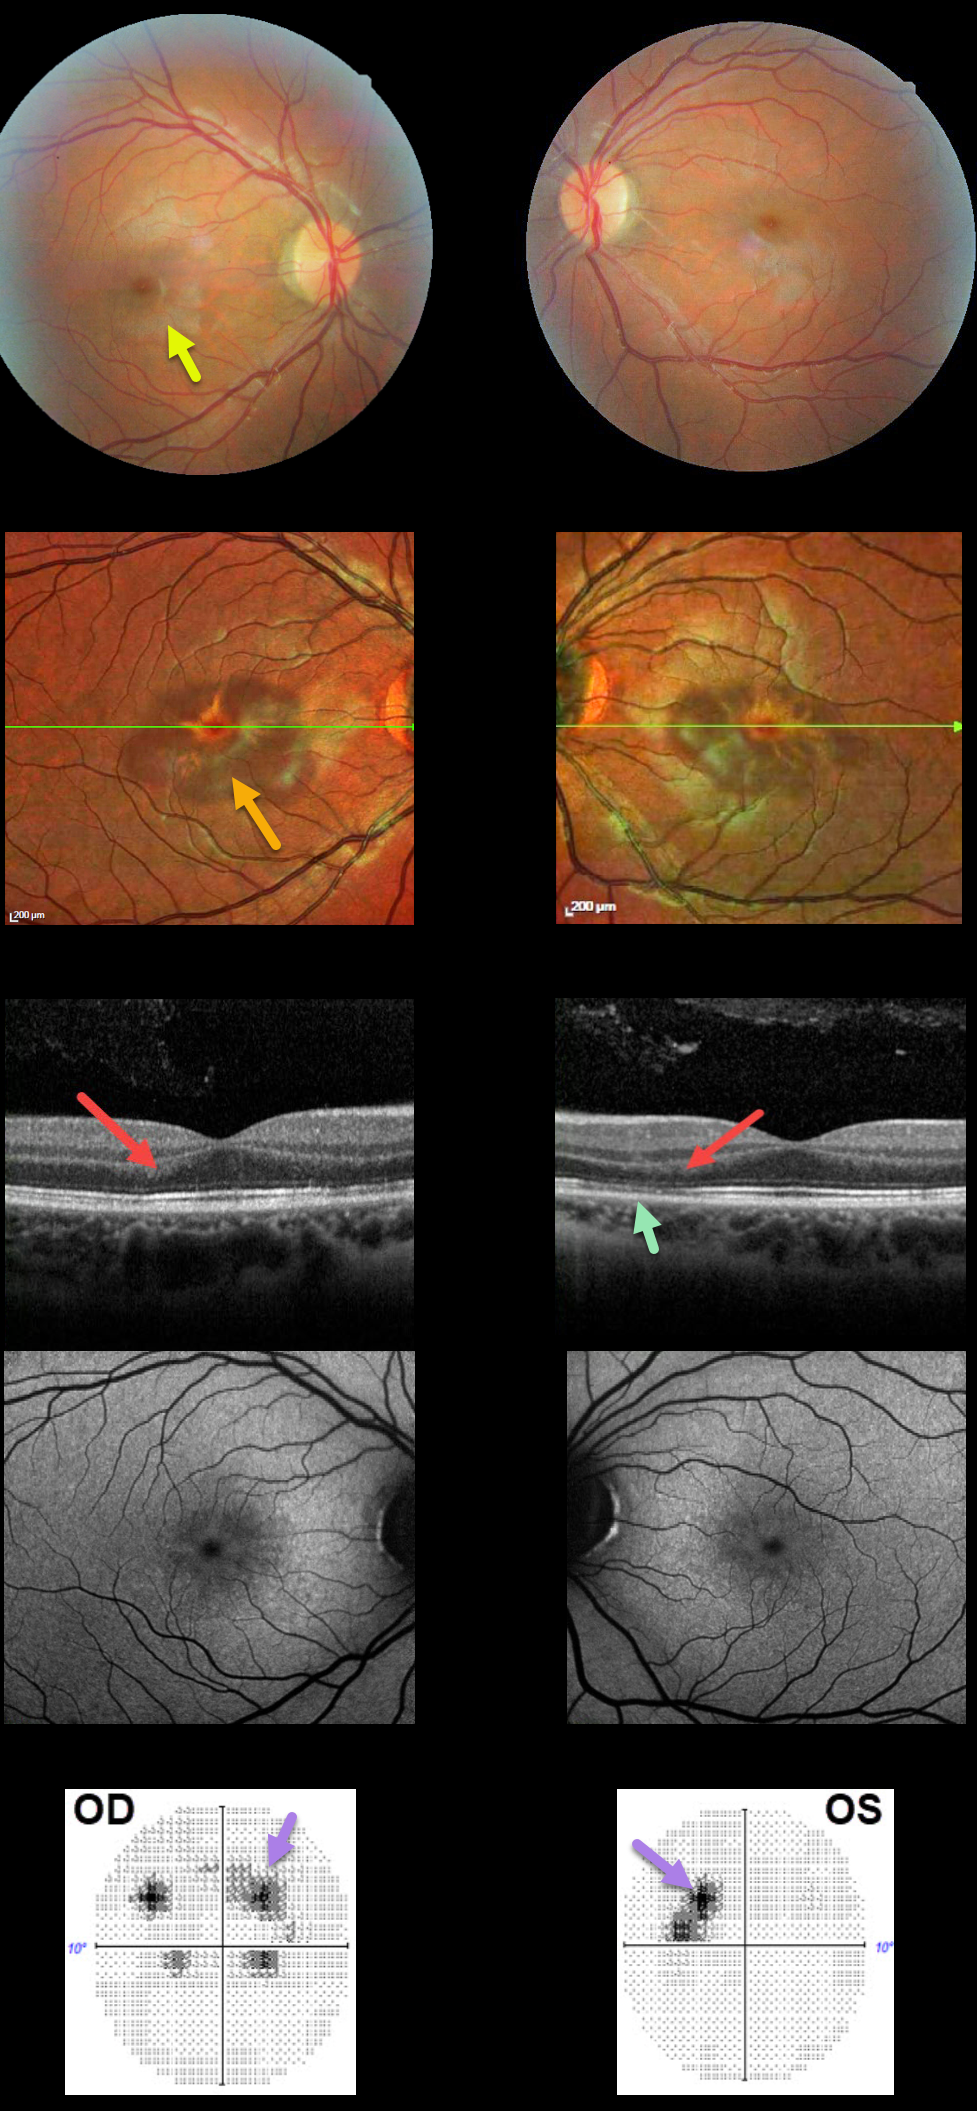
This 21YO female presented with a two-week history of bilateral paracentral relative scotomas. This was preceded by myalgias, sinus pressure, sore throat, and a cough. There was a 4-year history of oral contraceptive use. Vision was 20/25 OU.
There are faint reddish-brown wedge-shaped lesions radiating out of each fovea, seen more easily on multicolor imaging.
OCT scanning shows some focal areas of increased hyperreflectivity in the outer nuclear layer and defects in the ellipsoid zone. Fundus autofluorescence is relatively normal.
10-2 visual fields confirm the paracentral scotomas noticed by the patient. Over the following months, her 10-2 visual field partially improved, coinciding with partial normalization of the OCT findings (not shown).
Learning Points:
This case highlights many characteristic features of acute macular neuroretinopathy (AMN), an idiopathic disorder likely caused by compromise of the deep retinal capillary plexus.
Multicolor and infrared imaging often highlight the typical wedge-shaped AMN lesions more effectively than color fundus photos.
84% of patients are female with a median age of 30 years, and 80% are non-Latino white.
The most common association is a flu-like prodrome (48%), followed by oral contraceptive use (36%).
Presenting acuity is 20/40 or better in 80% of eyes, coinciding with sparing of the sub-foveal areas. Roughly half of AMN cases are bilateral. There is typically moderate visual improvement over the coming months, and no treatment is recommended.
For a great summary of AMN, see Bhavsar KV et al, Surv Ophthalmology 2016; 61:538-565.


