

Miscellaneous
<< Back to Cases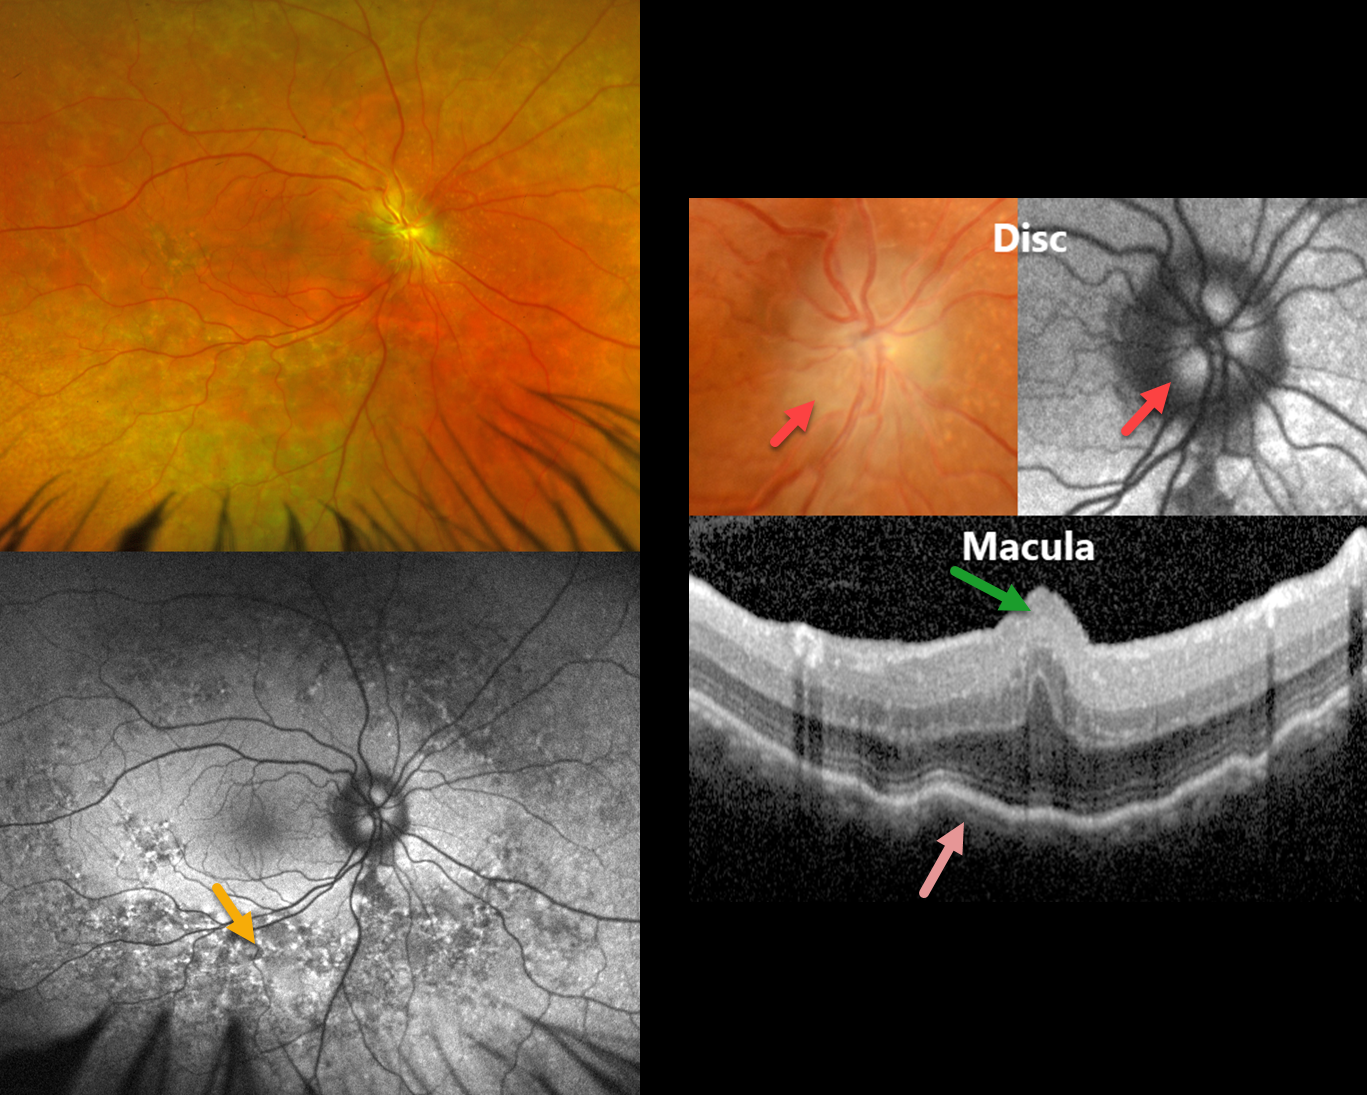
MFRP RETINITIS PIGMENTOSA
João Pedro Marques
Originally posted on @retina.rocks June 9, 2026
This 49YO male has a history of MFRP-related retinitis pigmentosa (RP). We have followed him for 13 years with stable findings of bilateral nanophthalmos (+18D hyperopia, axial lengths 14.82mm OD and 15.14 OS), optic disc drusen (ODD), and choroidal folds. He has compound heterozygosity for 2 pathogenic variants in the MFRP gene.
Optos color RG imaging in his OD shows pigmentary changes throughout the midperiphery along with an ill-defined disc margin. Fundus autofluorescence (FAF) shows variable hyper- and hypo-FAF in the midperiphery. Disc drusen are noted on a more magnified view, which hyper-FAF. Macular OCT shows a central fold, choroidal thickening, and chorioretinal folds. Identical findings were present in his OD (not shown).
Learning Points:
The MFRP (membrane frizzled-related protein) is expressed in the RPE and ciliary epithelium. MFRP functions as a molecular hub on the RPE apical membrane, coordinating protein trafficking and lipid homeostasis. Loss of MFRP leads to DHA accumulation in the RPE, downregulation of visual cycle genes and phototransduction genes, and progressive photoreceptor degeneration.
Biallelic MFRP mutations cause a well-characterized autosomal recessive retinitis pigmentosa (RP) syndrome with nanophthalmos and ODD (Li et al, BJO 2024;108;1679-1687). These eyes are at high risk of angle-closure glaucoma, usually requiring prophylactic laser peripheral iridotomy.
HARADA DISEASE
The European VitreoRetina Society (EVRS), Malvika Singh and Manish Nagpal
Originally posted on @retina.rocks October 3, 2025
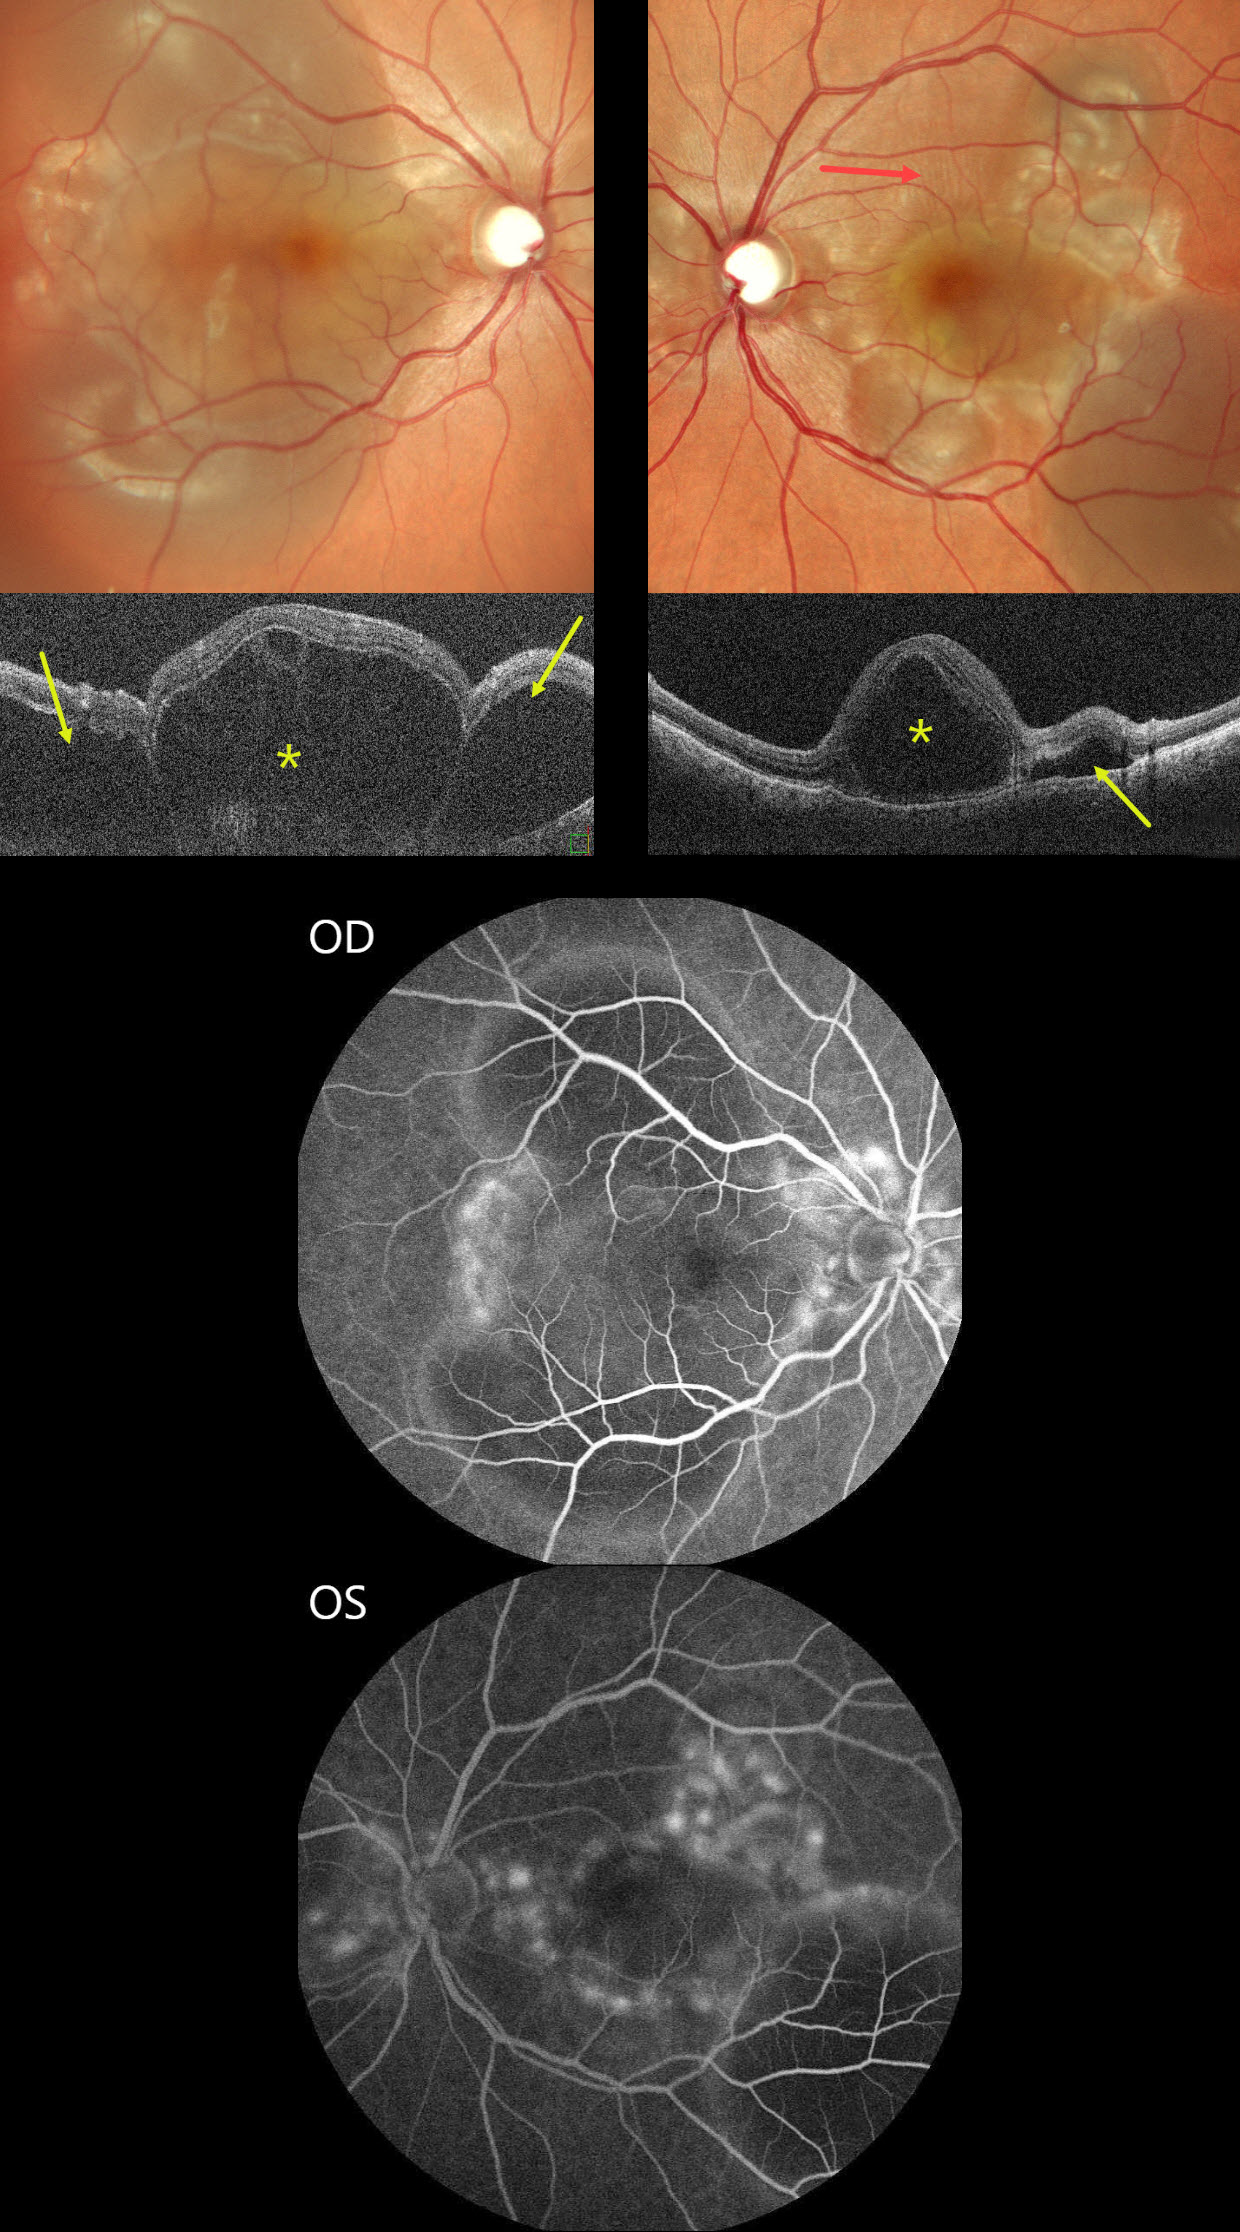
This previously healthy 30YO female presented with sudden bilateral vision loss for 5 days. Vision was counting fingers OU.
Color SLO imaging shows bilateral variably confluent serous detachments involving the posterior poles. Retinal folds are also noted in the left superior macula. OCT scanning shows a complex pattern of bacillary layer detachments (asterisks) and subretinal fluid (arrows). Fluorescein angiography shows multifocal subretinal leaks with pooling in the pockets of subretinal and intraretinal spaces.
She was started on oral steroids and immunomodulators in conjunction with a rheumatologist. One month later, vision returned to 20/20 OU with normalization of the funduscopic findings (not shown).
Learning Points:
Harada disease is characterized by relatively acute bilateral panuveitis, optic nerve swelling, thickened choroid, chorioretinal folds, multifocal serous exudative retinal detachments, and bacillary layer detachments. Patients with only ocular findings (as in our patient) have Harada disease, whereas those with additional systemic findings (including vitiligo, poliosis, headache, vertigo, and hearing loss) have Vogt-Koyanagi-Harada disease.
CHOROIDAL DETACHMENT
Mattie Adams
Originally posted on @retina.rocks January 27, 2025
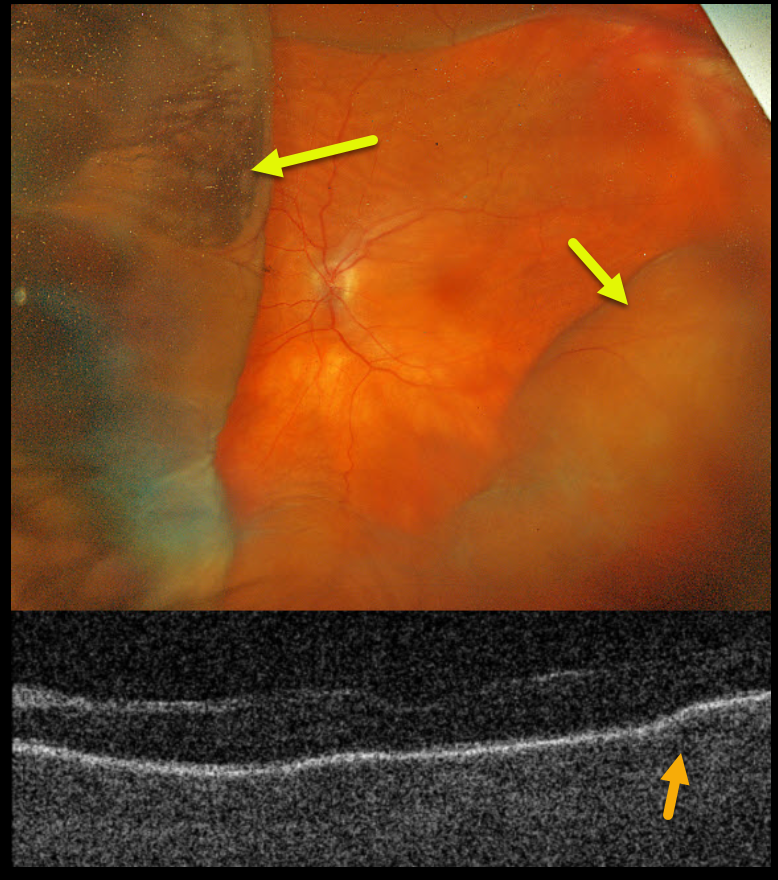
This 78YO female presented with acute vision loss in her left eye. Penetrating keratoplasty (PKP) was performed 9 months earlier. When seen on 8/26/24, vision was counting fingers in part due to irregular astigmatism from the residual PKP sutures, which were then removed. The cornea was Seidel negative after removal. She returned one week later complaining of a curtain in her visual field. Her anterior chamber was flat, and her corneal graft was dehisced for 3 clock hours.
Optos color RGB imaging shows a variably elevated choroidal detachment. Triton swept-source OCT shows chorioretinal folds.
Learning Points:
A choroidal detachment is defined by the abnormal presence of fluid or blood in the suprachoroidal space. Serous choroidal detachments, also known as choroidal effusions, are a frequent complication of glaucoma surgery. Several causative mechanisms are believed to be at play: hypotony allows fluid to accumulate in the suprachoroidal space and inflammation increases the choroidal permeability. The detached ciliary body may also produce less aqueous, thus creating a self-perpetuating cycle. Often, observation is sufficient but topical steroids and cycloplegics can be helpful to aid in resolution.
Hypotony maculopathy is characterized by low IOP and chorioretinal folds, most commonly following glaucoma filtration surgery. Optic nerve edema can also be seen due to decreased axoplasmic transport.
Our patient was immediately taken to surgery for suturing of the dehisced PKP. The choroidals and chorioretinal folds immediately improved and completely resolved two months later (not shown).
CHORIORETINAL FOLDS
Tejaswita Verma and Manish Nagpal
Originally posted on @retina.rocks January 1, 2025
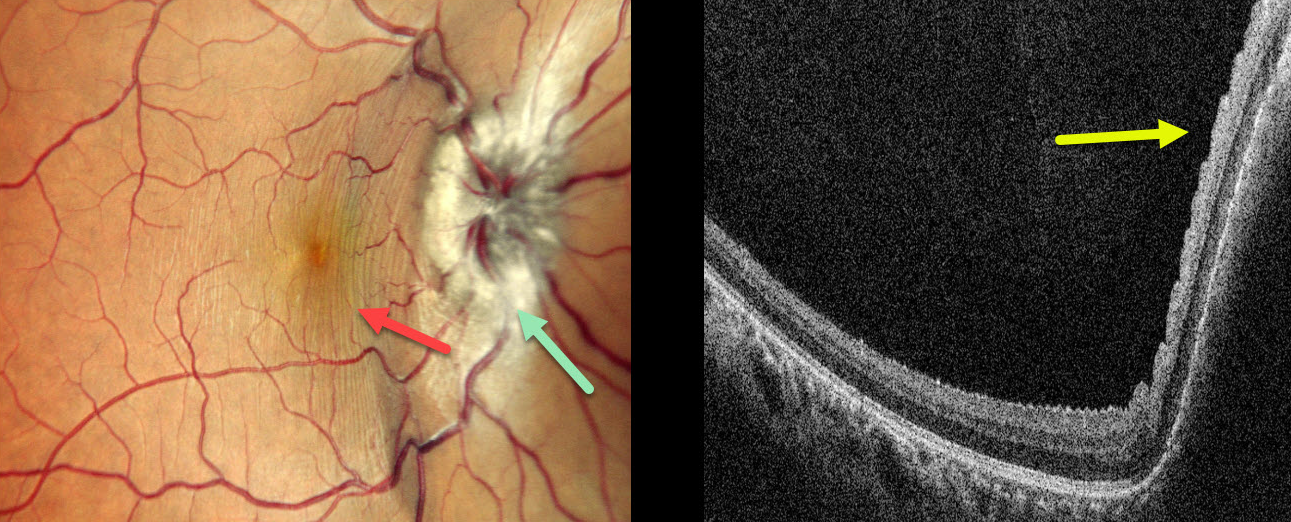
A 26YO male presented with 3 weeks of right eye pain, proptosis, and vision loss. MRI several days earlier was suggestive of an orbital venolymphatic malformation (VLM). Vision was 20/30 OD and 20/20 in his normal OS. The right eye was grossly proptotic.
Multicolor SLO imaging shows right disc edema with nasal macular linear inner retinal folds circumferential to the nerve. On OCT, these folds appear as corrugations along the nasal macular surface.
Learning Points:
Orbital and periorbital VLMs are benign congenital vascular lesions that represent 1-3% of all orbital masses. These are composed of abnormal vascular channels lined by endothelial cells, with a spectrum ranging from venous to lymphatic characteristics. Clinically, these present with progressive ptosis, proptosis, restriction of eye movements, swelling, and, in severe cases, with acute visual loss due to intralesional hemorrhage or optic nerve compression. Treatment includes surgery for superficial VLM and intralesional sclerotherapy with bleomycin for non-resectable or treatment-resistant tumors. Ultrasound-guided intralesional bleomycin was recommended for our patient.
In 1911, Paton and Holmes established that papilledema was due to elevated intracranial pressure rather than inflammation, as was previously thought (Brain 1911;33:389-432). They also noted that nerve edema was associated with “a series of folds which run concentric with the edge of the disc,” which they felt represented retinal folds. Sibony and Kupersmith, correlating OCT with fundus photography, found that these folds represented a variety of structural stresses on the nerve and peripapillary tissues, including peripapillary wrinkles, inner retinal folds, choroidal folds, and outer retinal folds/creases (Ophthalmology 2016;123:1397-1399).
POSTOP DIABETIC TRD WITH INNER RETINAL FOLDS
Originally posted on @retina.rocks September 5, 2024
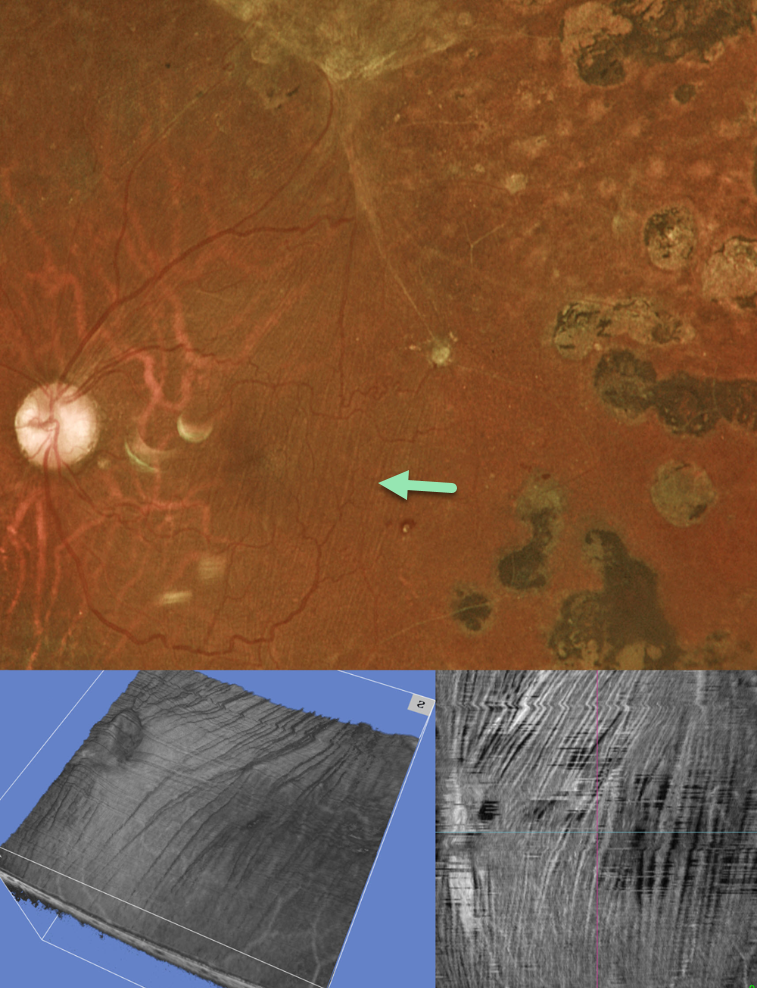
This 35YO diabetic male underwent prior vitrectomy surgery for a diabetic traction retinal detachment (TRD) five years earlier. Vision was stable at 20/40.
Optos color RG imaging shows fine macular striae extending superiorly towards the area of prior traction. Triton swept-source OCT 3D reconstruction and inner retinal en face show differing perspectives of these inner retinal folds.
Inner retinal folds are common following vitrectomy for diabetic TRD. They often fail to completely resolve, and vision can be quite good despite the persisting findings.
TRACTIONAL RETINAL DETACHMENT
Originally posted on @retina.rocks June 10, 2024
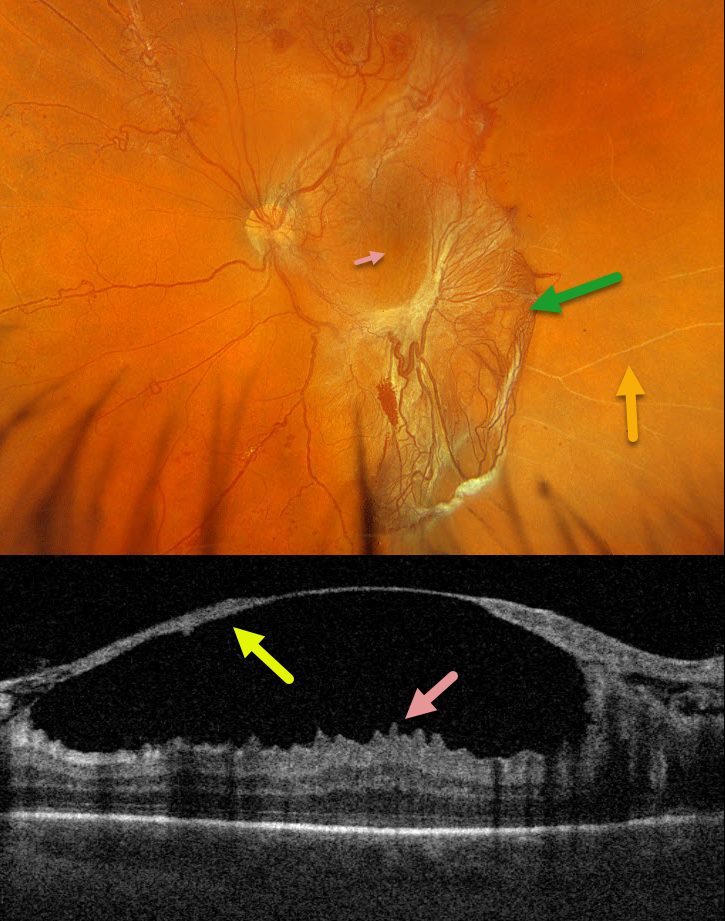
This 42YO male with type 2 diabetes presented with 1 week of vision loss in his left eye. Vision was 20/40 OD and 20/100 OS.
Optos color RGB imaging shows a large patch of variably fibrosed retinal neovascularization extending from the temporal macula into the inferior midperiphery. Vertical macular striae are drawn towards the neovascularization inferiorly. Scattered neovascularization is seen elsewhere, along with nonperfused large retinal vessels temporally.
Triton swept-source OCT through the macular center shows a thickened detached posterior hyaloid that extends from the optic nerve into the temporal macula. The macular striae noted on the Optos image correspond to inner macular folds on OCT. Vitrectomy surgery was scheduled.
HYPOTONY MACULOPATHY
Originally posted on @retina.rocks May 13, 2024
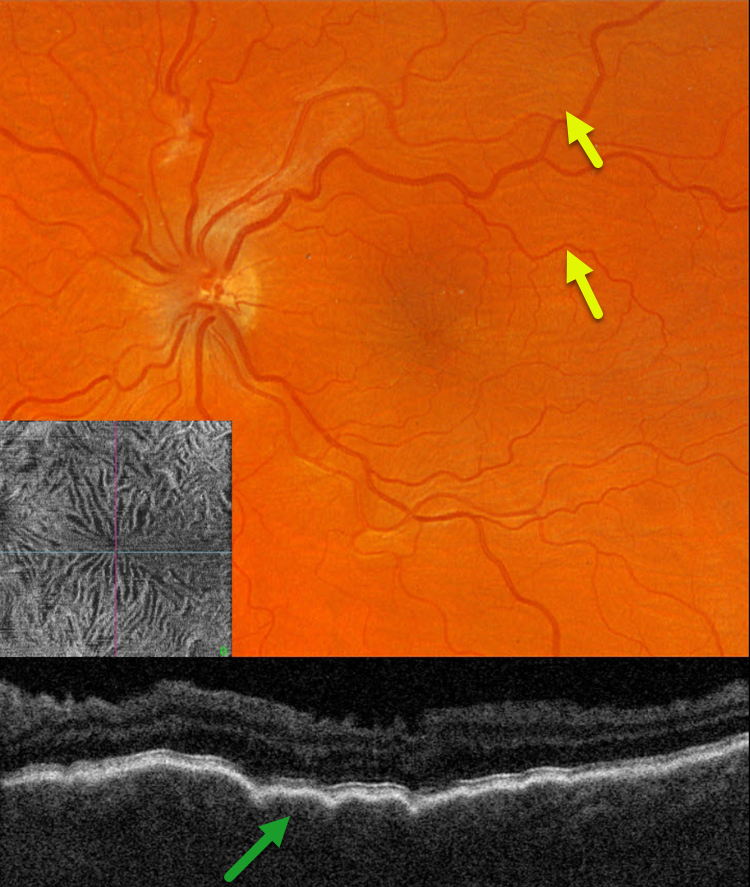
This 39YO male with a history of pigmentary glaucoma underwent goniotomy surgery by an outside practice in his left eye 3 weeks earlier. This eye has been hypotonus since, and vision was 20/150.
Optos color RG imaging shows faint diffuse chorioretinal folds throughout the posterior pole. Triton swept-source OCT B-scan shows a thickened choroid with overlying folds, and an irregularly rippled inner retina. En face OCT through the internal limiting membrane provides a unique perspective on inner retinal distortion.
Learning Points:
Hypotony maculopathy is characterized by low IOP and chorioretinal folds, most commonly following glaucoma filtration surgery. Optic nerve edema can also be seen due to decreased axoplasmic transport.
We expect our patient’s findings to improve once his intraocular pressure normalizes.
AMD SCAR
Originally posted on @retina.rocks October 4, 2022
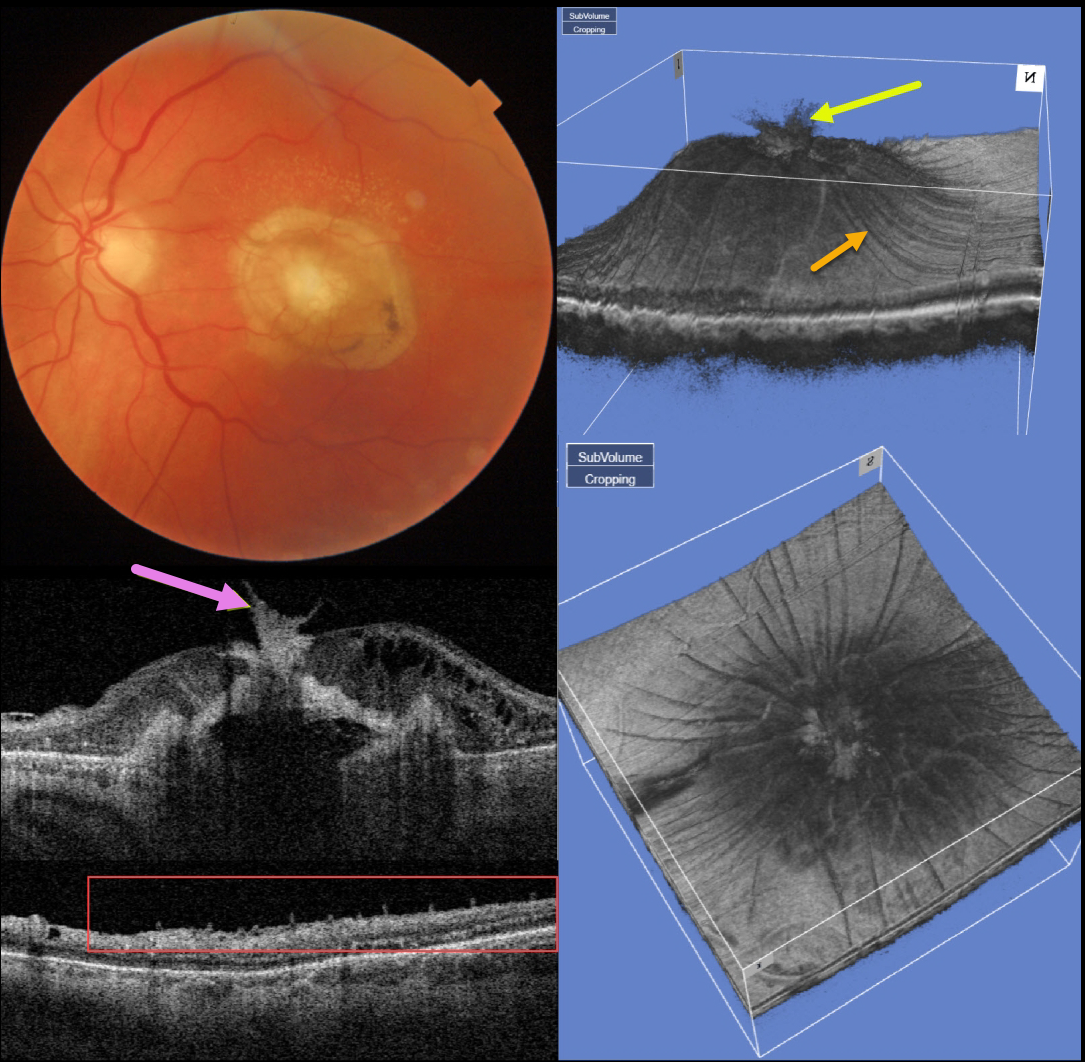
This 77YO man presented counting fingers vision OS with what seems at first to be an uneventful fibrotic disciform scar from neovascular AMD. But multimodal imaging shows several interesting findings.
Swept-source OCT through the macular center shows that the central scar extends through the full-thickness retina and becomes incorporated with the attached vitreous.
A 3D macular reconstruction viewed from above also shows how scar contraction is creating radiating retinal folds.
These folds on a B-scan taken through the peripheral macula give the appearance of numerous needle-like projections emanating from the inner retina.
The needle-like projections, created by imaging the radiating inner retinal folds perpendicular to their orientation, mimic findings felt to be pathognomonic for ocular amyloidosis (Kakuhara et al, Ophthalmology Retina 2021;5:1005-1008).
PAPILLEDEMA
Originally posted on @retina.rocks September 2, 2022
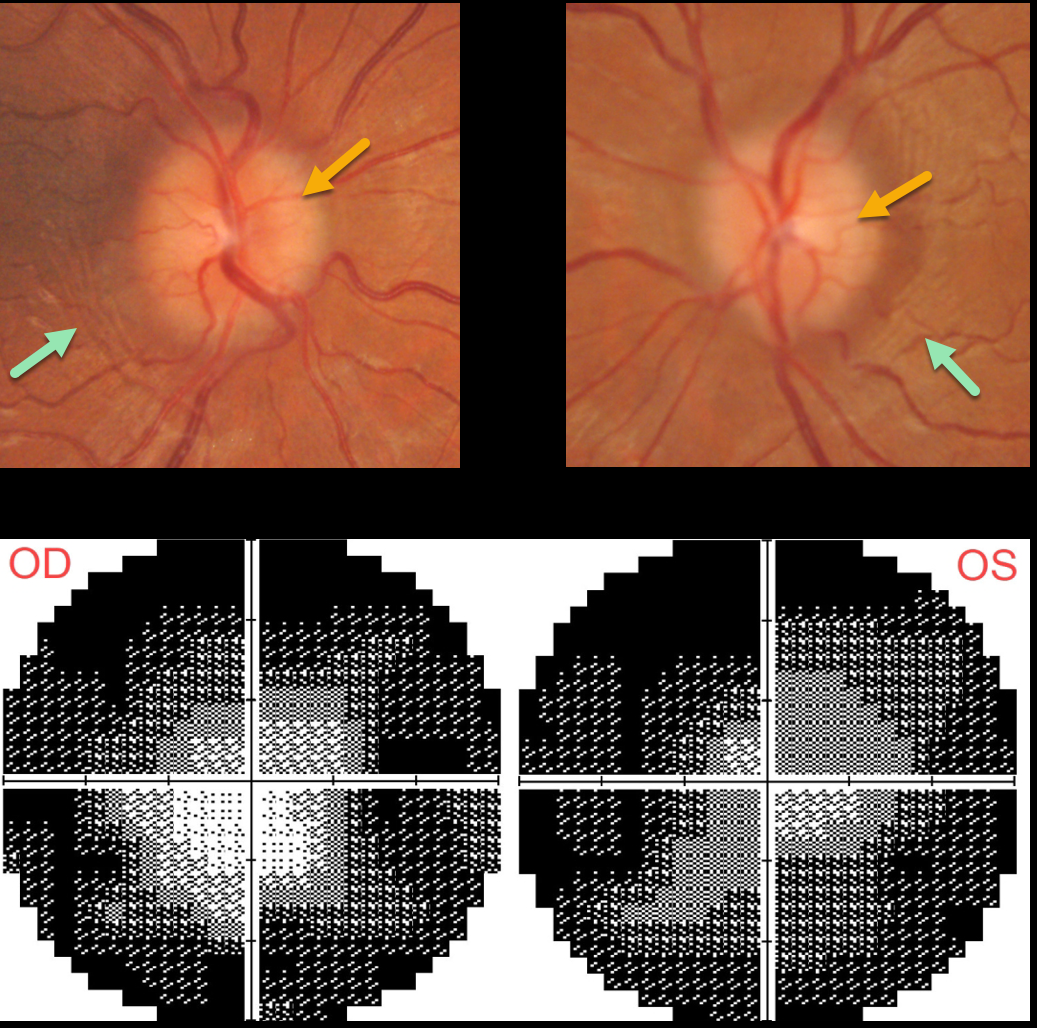
This 30YO female was diagnosed with idiopathic intracranial hypertension (pseudotumor cerebri) in 2020. Her initial lumbar puncture opening pressure was elevated at 25cm H2O.
She was lost to follow-up for about 2 years, when she presented with recurrent headaches, a ‘whooshing’ sound in her ears, and blurred vision. She was off of Topamax for about a year. Vision was 20/30 OD and 20/40 OS.
Both optic nerves are mildly edematous. The retinal nerve fiber layer (not shown) is somewhat thickened bilaterally. Despite the modest nerve edema, prominent temporal circumferential retinal folds (Paton’s folds) surround both nerves. Visual fields are severely constricted.
Learning Points:
In 1911 Paton and Holmes established that papilledema was due to elevated intracranial pressure and not inflammation as was previously thought (Brain 1911;33:389-432).
They also noted that nerve edema was associated with “a series of folds which run concentric with the edge of the disc” which they felt represented retinal folds.
Sibony and Kupersmith, correlating OCT with fundus photography, found that these folds represented a variety of structural stresses on the nerve and peripapillary tissues, including peripapillary wrinkles, inner retinal folds, choroidal folds and outer retinal folds/creases (Ophthalmology 2016;123:1397-1399).
HYPOTONY MACULOPATHY
Originally posted on @retina.rocks April 12, 2022
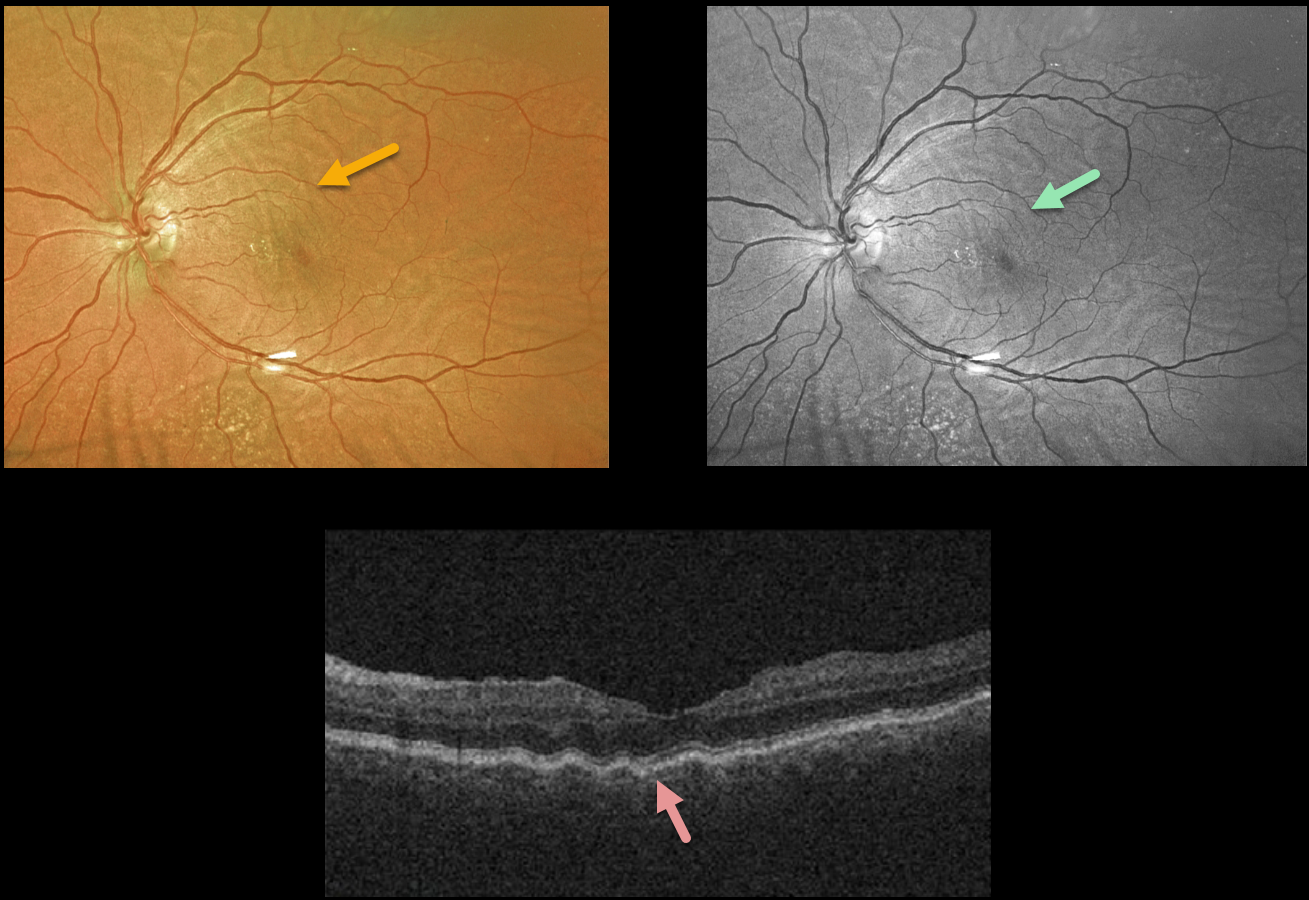
This 60YO female developed hypotony in her left eye following a Baerveldt implant.
Chorioretinal folds are seen on the Optos color photo and are more pronounced in the green channel. OCT shows the unilateral radiating left macular folds.
Although pressures were initially almost zero for about 2 months postoperatively, they have since risen to about 10 with persistence of the chorioretinal folds.
Vision is 20/30, and we continue to follow her.
HARADA DISEASE
Originally posted on @retina.rocks February 7, 2022
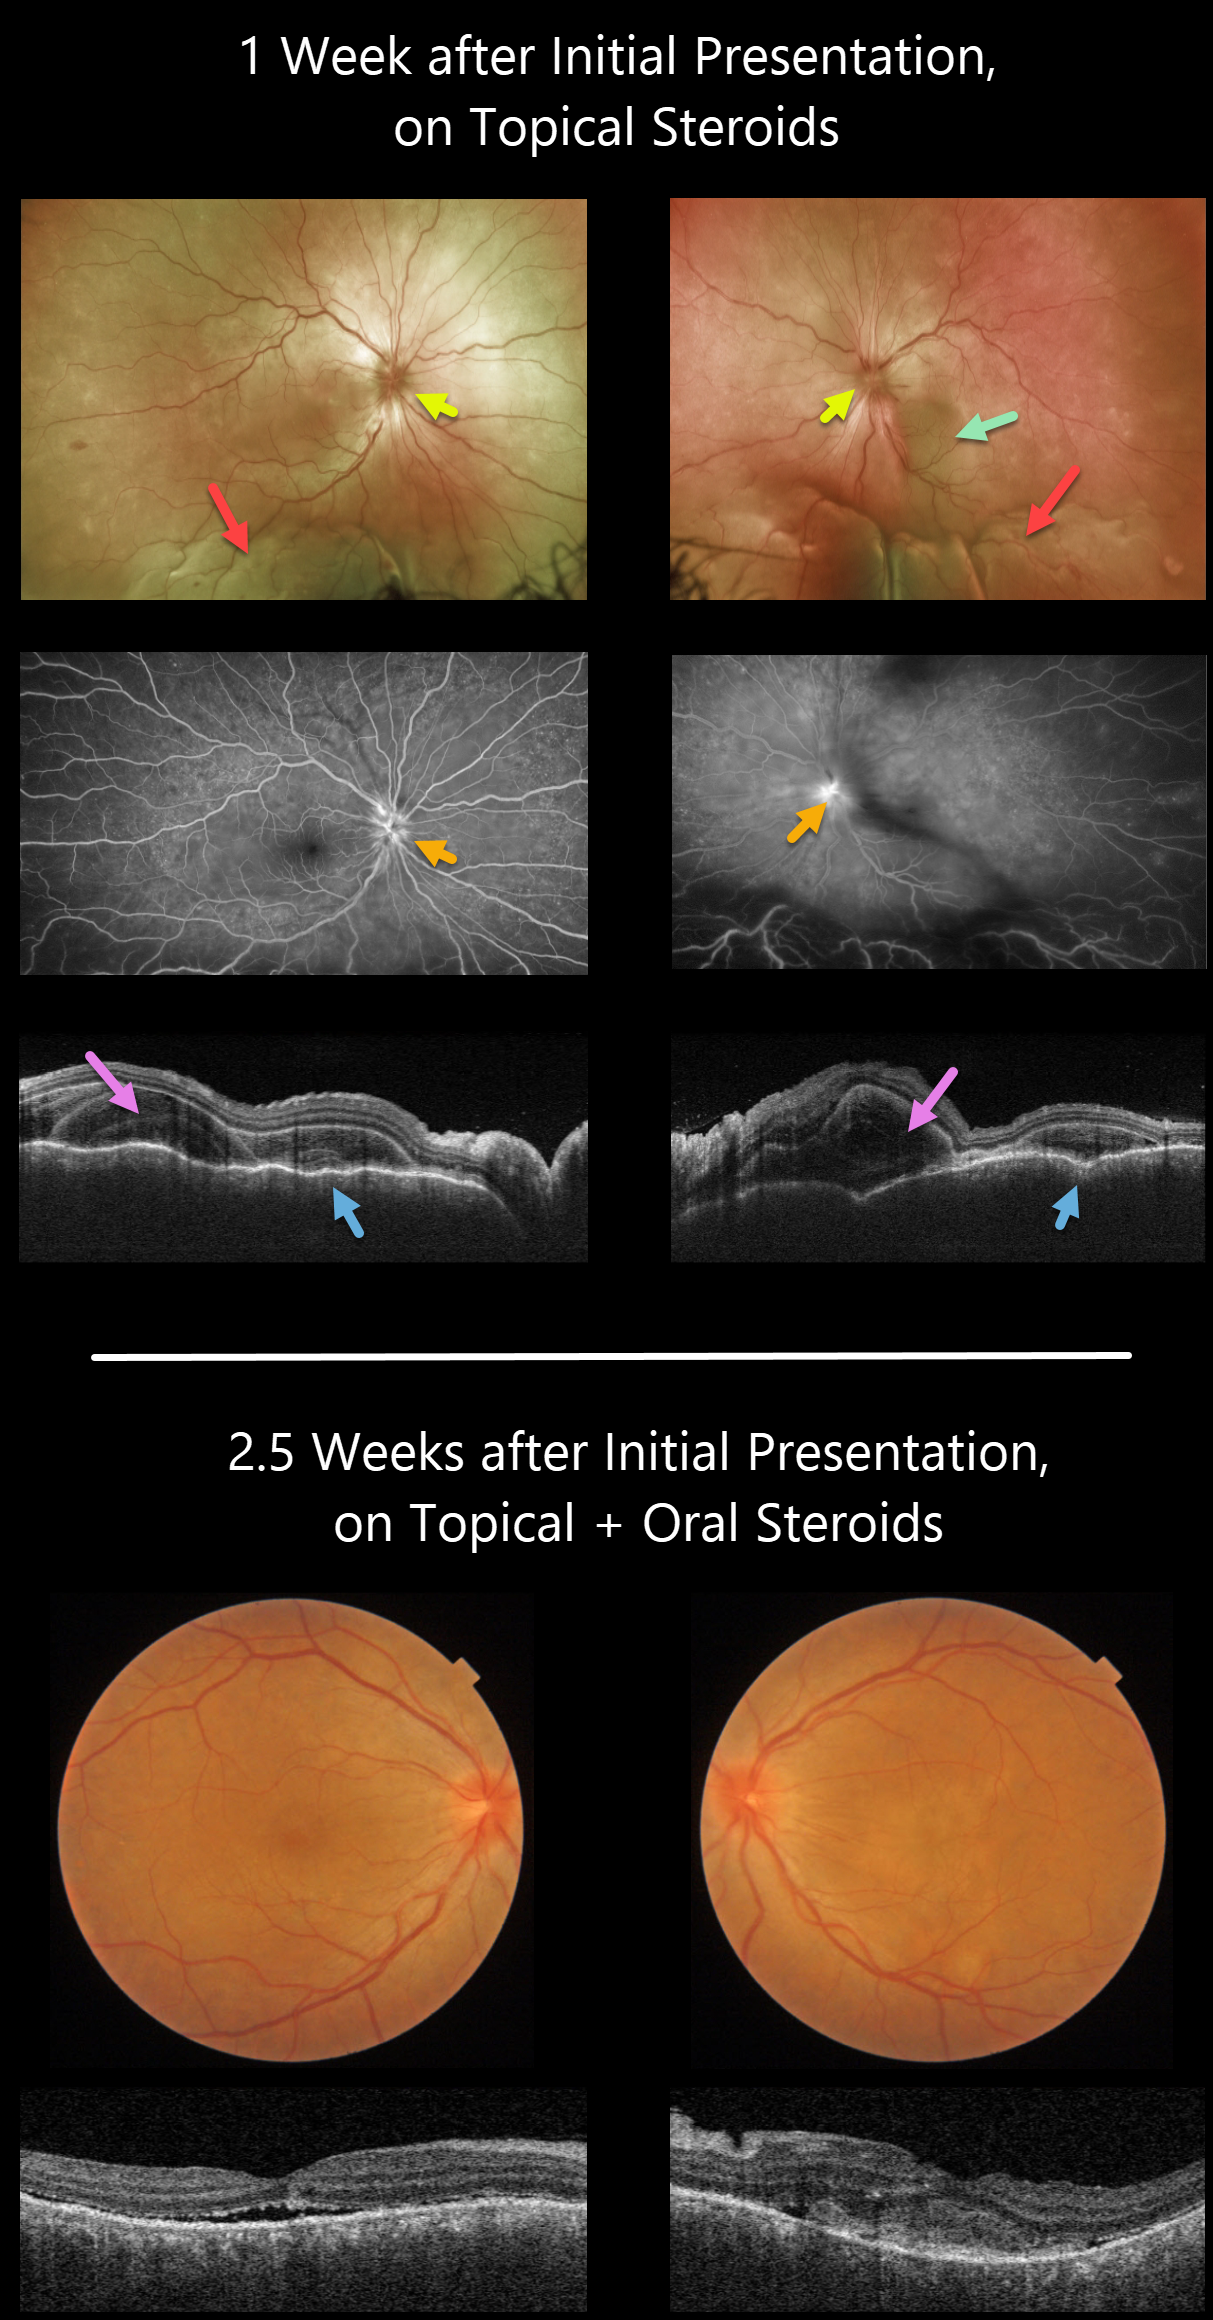
This 35YO female presented with a 2-week history of severe bilateral vision loss, photophobia, and red eyes. There was no significant past medical history.
Vision was counting fingers OU. There was moderate bilateral conjunctival injection, severe cells with moderate flare, moderate fibrin, and 360-degree posterior synechiae. Topical cycloplegia and steroids were prescribed.
One week later, she was referred to our retinal service. There was marked improvement of her anterior uveitis and the posterior synechiae were mostly broken throughout. There were moderate bilateral vitreous cells, markedly swollen optic nerves, irregular diffuse macular exudative fluid with inferior exudative retinal detachments.
Fluorescein angiography showed bilateral optic nerve leakage. Triton swept-source OCT showed bilateral markedly thickened and rippled choroid with multiple bacillary pockets of outer retinal thickening and fluid. She started oral prednisone 80mg daily.
Around 10 days later, vision improved to 20/200 OU, with improvement in optic nerve edema, macular fluid, bacillary detachments, and choroidal thickening. The inferior exudative detachments were also resolving (not imaged).
Learning Points:
This case has many classic findings for Harada disease, including bilateral panuveitis, optic nerve swelling, thickened choroid, chorioretinal folds, and multifocal serous exudative retinal detachments.
Given the severity of the panuveitis and exudative subretinal fluid, we were surprised that angiography did not show the more classic multifocal subretinal leaks with pooling in the overlying serous detachments and bacillary cavities.
Patients with just ocular findings have Harada disease, whereas those with additional systemic findings (including vitiligo, poliosis, headache, vertigo, and hearing loss) have Vogt-Koyanagi-Harada disease.
BILATERAL DIFFUSE UVEAL MELANOCYTIC PROLIFERATION (BDUMP)
Originally posted on @retina.rocks September 29, 2021
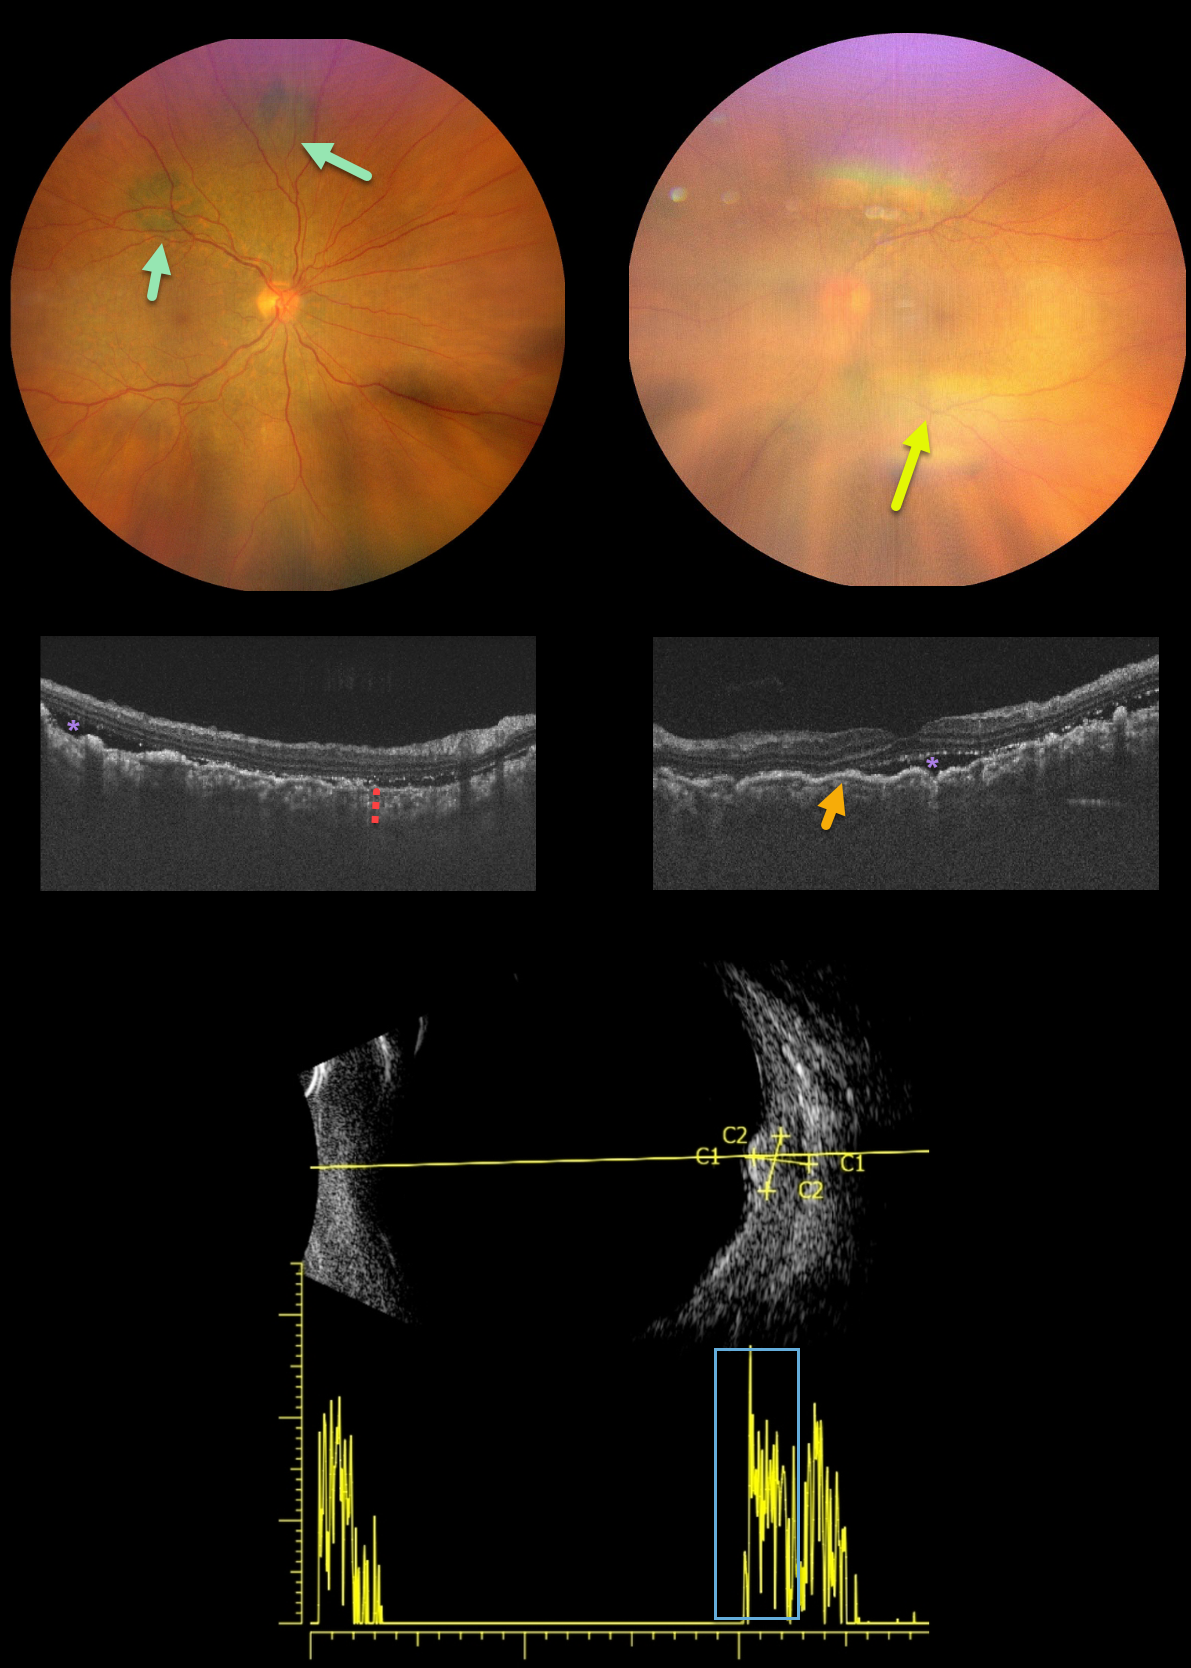
This is a 62YO female presented with bilateral vision loss over the past 3 months. Her vision was 20/200 OD and counting fingers OS compared to 20/20 OU at baseline. She was diagnosed with stage 4 ovarian cancer one month earlier.
New multifocal, elevated, pigmented choroidal lesions are noted superonasally in the right eye. View of the left fundus is limited due to a significant progressive cataract.
OCT reveals bilateral choroidal thickening with overlying folds and some subretinal fluid. B-scan ultrasonography through one of the choroidal lesions in the right eye shows moderate homogenous internal reflectivity.
Learning Points:
Initially described by Machemer in 1966, the five cardinal features of bilateral diffuse uveal melanocytic proliferation (BDUMP) include:
(1) multiple round or oval subtle red patches at the level of the RPE
(2) a striking pattern of multifocal areas of fluorescein angiographic hyperfluorescence from these lesions
(3) multiple slightly elevated pigmented and nonpigmented uveal melanocytic tumors with diffuse uveal thickening
(4) exudative retinal detachment
(5) rapidly progressive cataracts (Gass et al, Arch Ophthalmology 1990;108:527-533).
The thickened choroid and pigmentary changes are secondary to infiltration by benign uveal melanocytes, possibly in response to a primary visceral tumor (ovarian and uterine carcinomas in women, lung carcinoma in men) that produces melanocytic growth factors. Vision typically deteriorates to near blindness within a year of presentation. The serous detachments can resolve with plasmapheresis, although the overall prognosis is generally poor, with a mean survival of about 1 year from the time of ocular diagnosis.
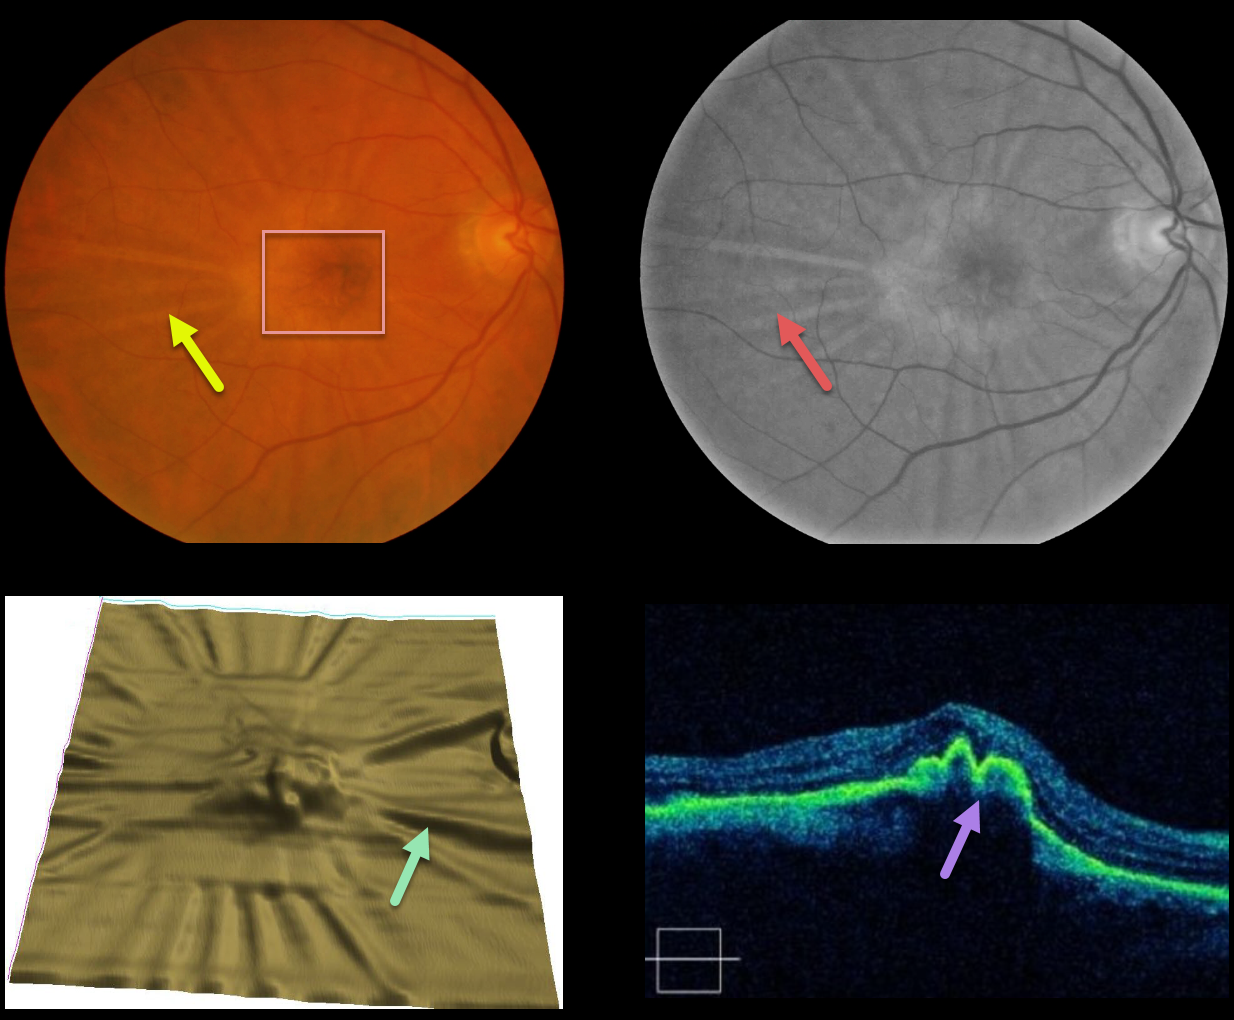
MACULAR NEOVASCULARIZATION (MNV)
Originally posted on @retina.rocks September 14, 2021
This patient developed radiating chorioretinal folds from an involuted type 1 macular neovascularization (MNV, located below the RPE) following multiple intravitreal Avastin injections.
These folds are imaged on the color and red-free photos, as well as on the OCT thickness map and B-scans. Remarkably, vision has been stable at 20/30 for years.
Learning Points:
Macular neovascularization is also known by other terms, including choroidal neovascular membrane and subretinal neovascular membrane.
However, since these vessels are now known not to necessarily arise just from the choroid, the proper term is macular neovascularization (see Consensus on Neovascular Age-Related Macular Degeneration Nomenclature Study Group Ophthalmology 2020;127;616-636).
MNV is classified according to the location of the new vessels in relation to the RPE and neurosensory retina: type 1 (below the RPE), type 2 (between the RPE and neurosensory retina, and type 3 (within the neurosensory retina).
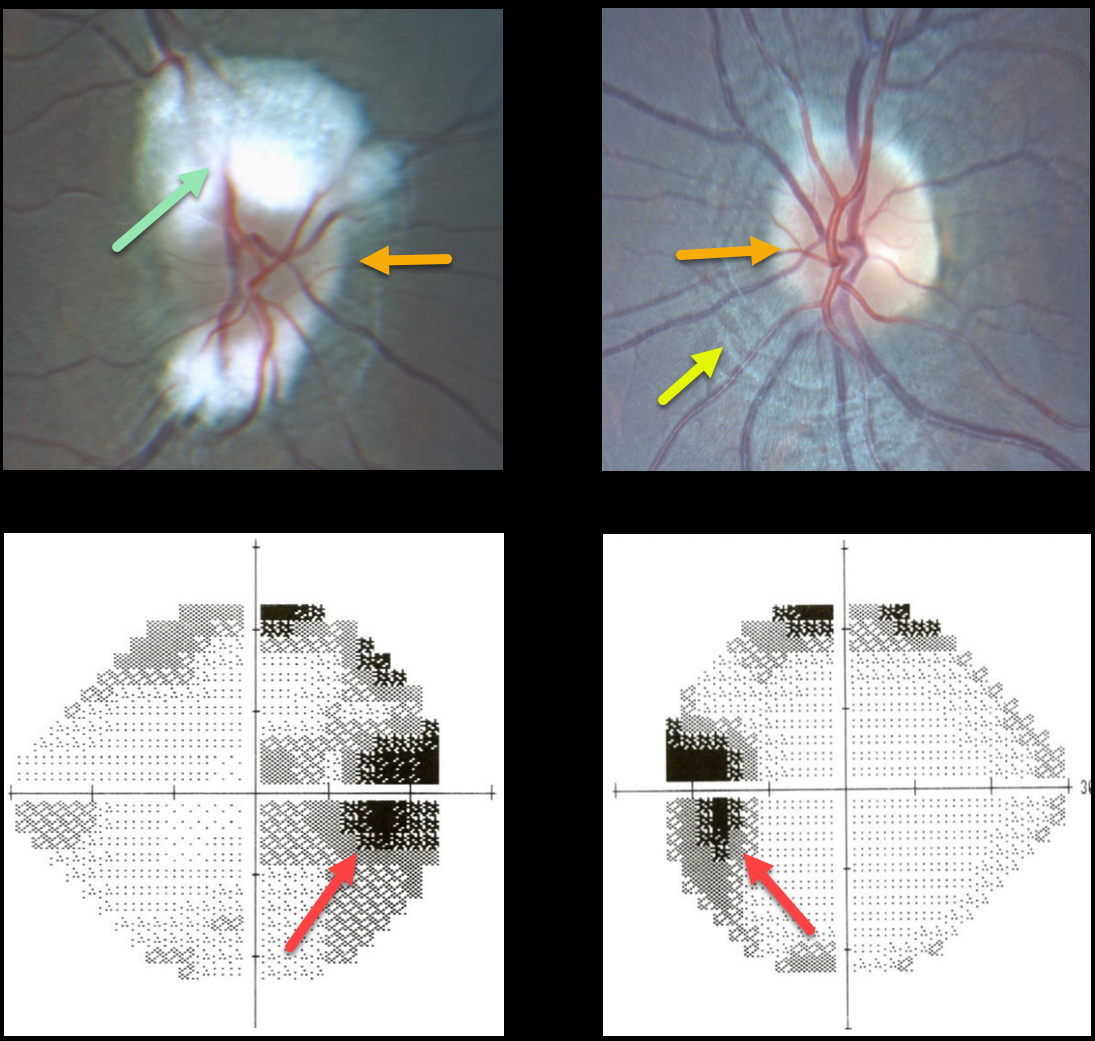
PAPILLEDEMA
Originally posted on @retina.rocks July 28, 2021
This 14YO presented with mild bilateral optic nerve edema and enlarged blind spots. Evaluation of the right nerve was difficult due to the myelinated nerve fiber layer.
There are prominent circumferential retinal lines (Paton’s folds) surrounding the left nerve.
MRI and MRV scanning were normal, and lumbar puncture opening pressure was elevated at 26mm H2O. The patient was diagnosed with idiopathic intracranial hypertension (pseudotumor cerebri).
Learning Points:
In 1911, Paton and Holmes established that papilledema was due to elevated intracranial pressure rather than inflammation, as previously thought (Brain 1911;33:389-432).
They also noted that nerve edema was associated with “a series of folds which run concentric with the edge of the disc,” which they felt represented retinal folds.
Sibony and Kupersmith, correlating OCT with fundus photography, found that these folds represented a variety of structural stresses on the nerve and peripapillary tissues, including peripapillary wrinkles, inner retinal folds, choroidal folds, and outer retinal folds/creases (Ophthalmology 2016;123:1397-1399).
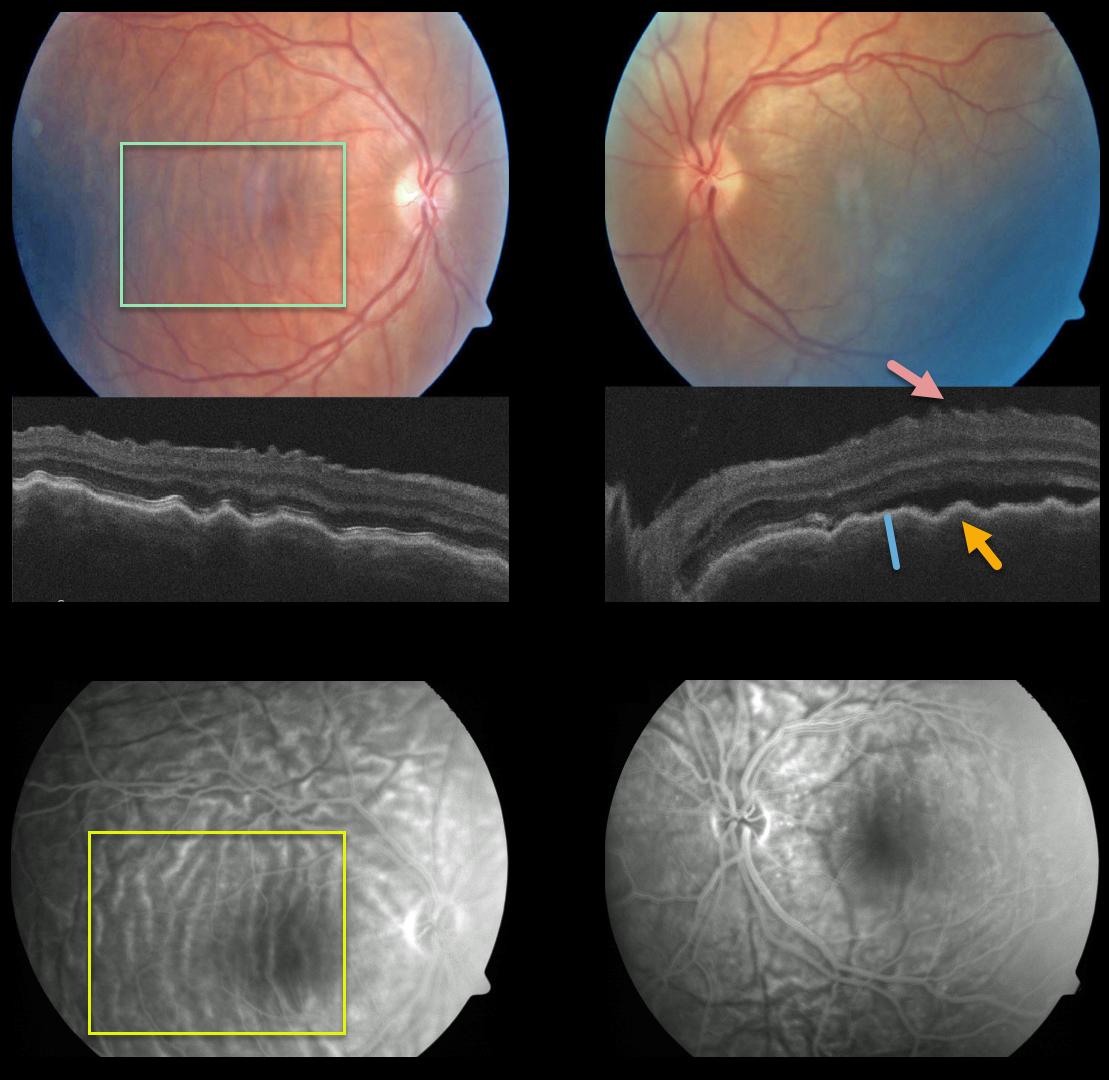
POSTERIOR SCLERITIS
Originally posted on @retina.rocks June 17, 2021
This patient presented with bilateral posterior pole chorioretinal folds, confirmed on OCT as inner retinal folds, outer retinal/RPE folds, and thickened choroid, and on fluorescein angiography.
Our patient most likely had the diffuse type of posterior scleritis. Unfortunately, we don’t have any further images or clinical information.
Learning Points:
Posterior scleritis can present either as a diffuse thickening of the entire posterior sclera or as a nodular type with localized scleral thickening (see Agrawal et al, Retina 2016;36:392-401).
Nodular inflammation appears as a posterior pole subretinal yellowish mass lesion, often with overlying serous fluid and chorioretinal folds.
B-scan ultrasonography may show fluid in the Tenon space (“T” sign). Unlike anterior scleritis, the eyes are usually quiet and pain-free.
Initial treatment is usually with oral non-steroidal anti-inflammatories or corticosteroids, although patients may also require immunosuppressive therapy.
For a large case series of posterior scleritis, see McCluskey et al, Ophthalmology 1999;106:2380-2386.
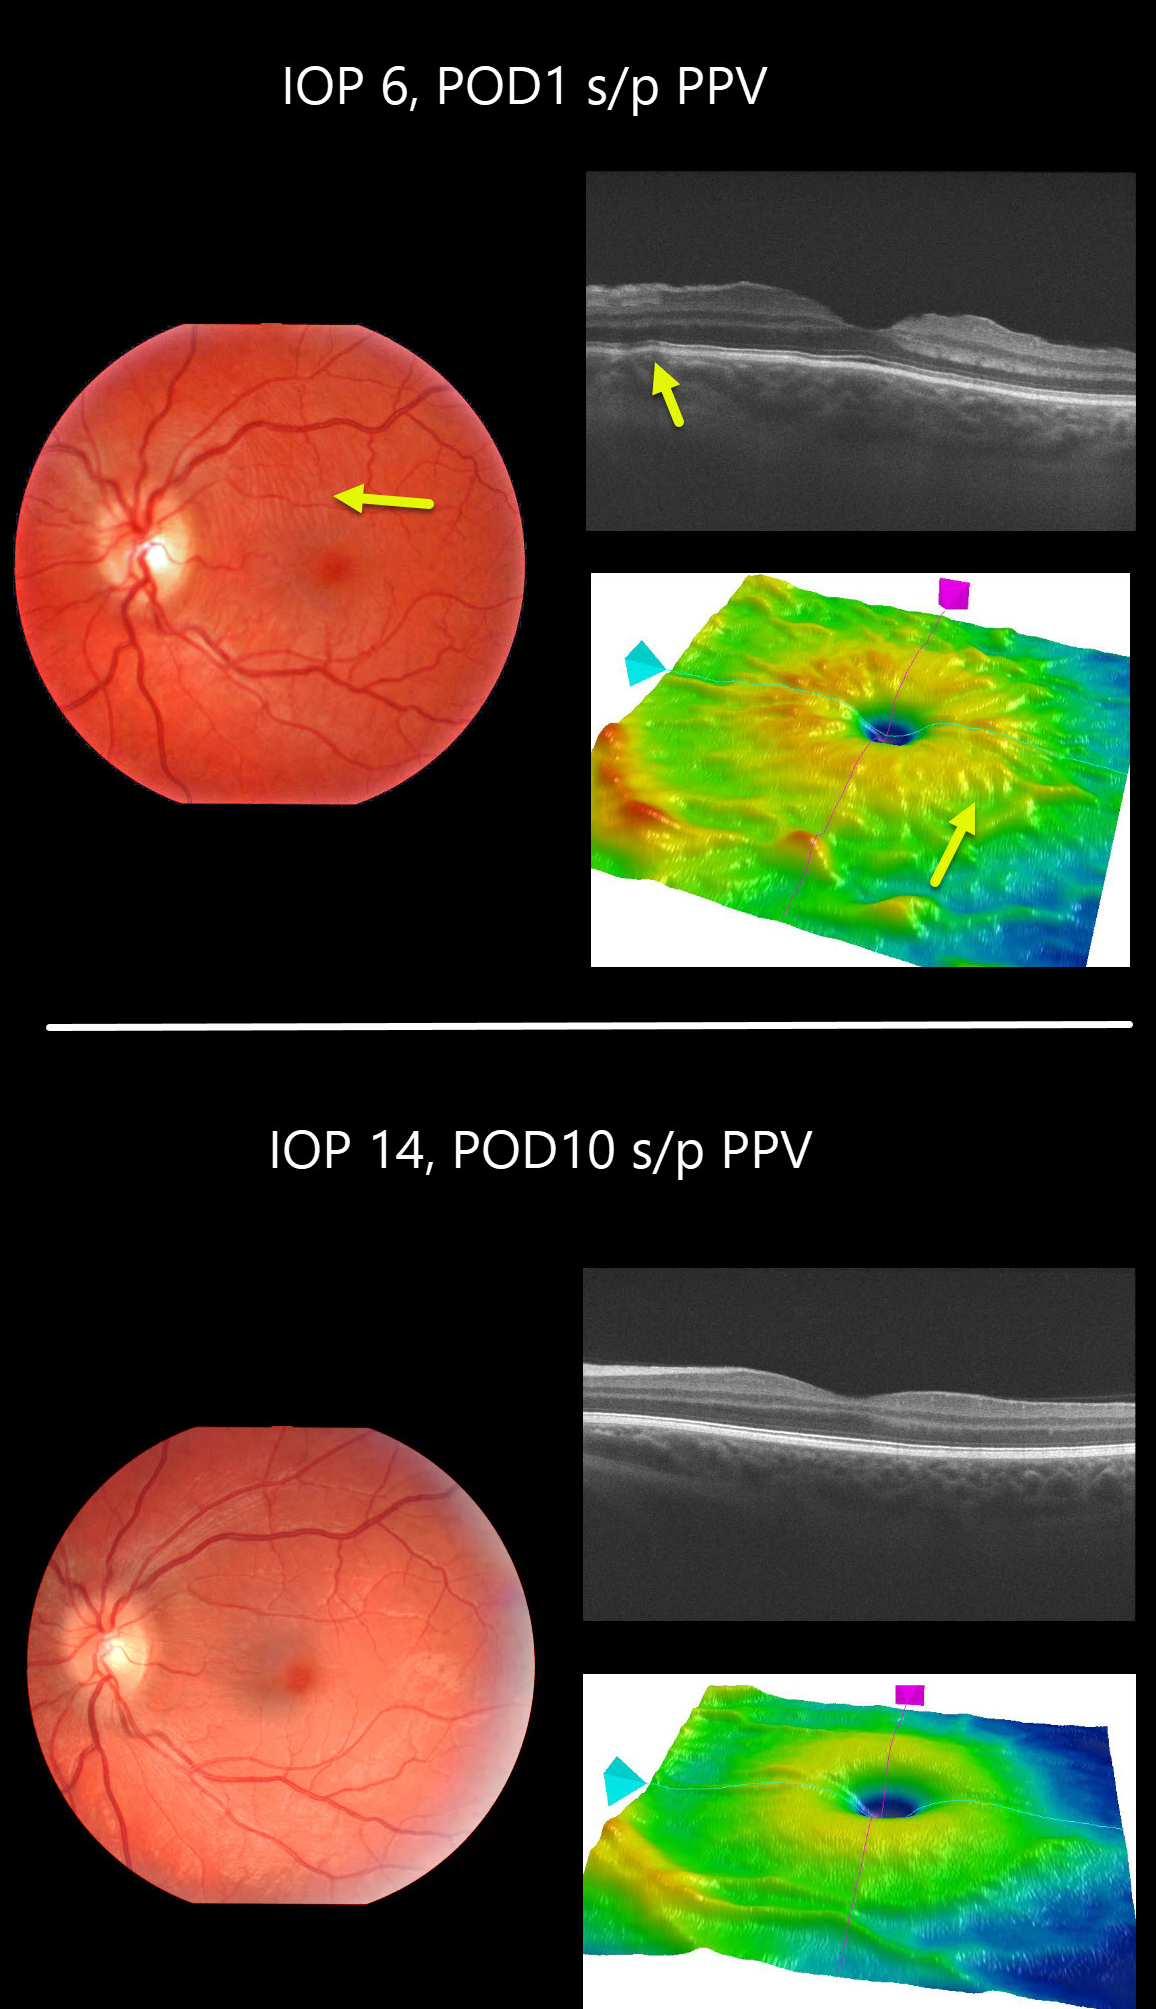
HYPOTONY MACULOPATHY
Originally posted on @retina.rocks September 1, 2020
This patient developed hypotony maculopathy one day following vitrectomy for vitreous floaters. Intraocular pressure was 6mmHg and all sclerotomy sites appeared tight. The retinal vessels are somewhat engorged and dilated.
Chorioretinal folds are seen in the fundus photo, OCT B-scan and thickness map.
These findings completely resolved 9 days later when his IOP recovered spontaneously to 14mmHg.
Learning Points:
Hypotony maculopathy is characterized by low IOP and chorioretinal folds, most commonly following glaucoma filtration surgery. Optic nerve edema can also be seen due to decreased axoplasmic transport.
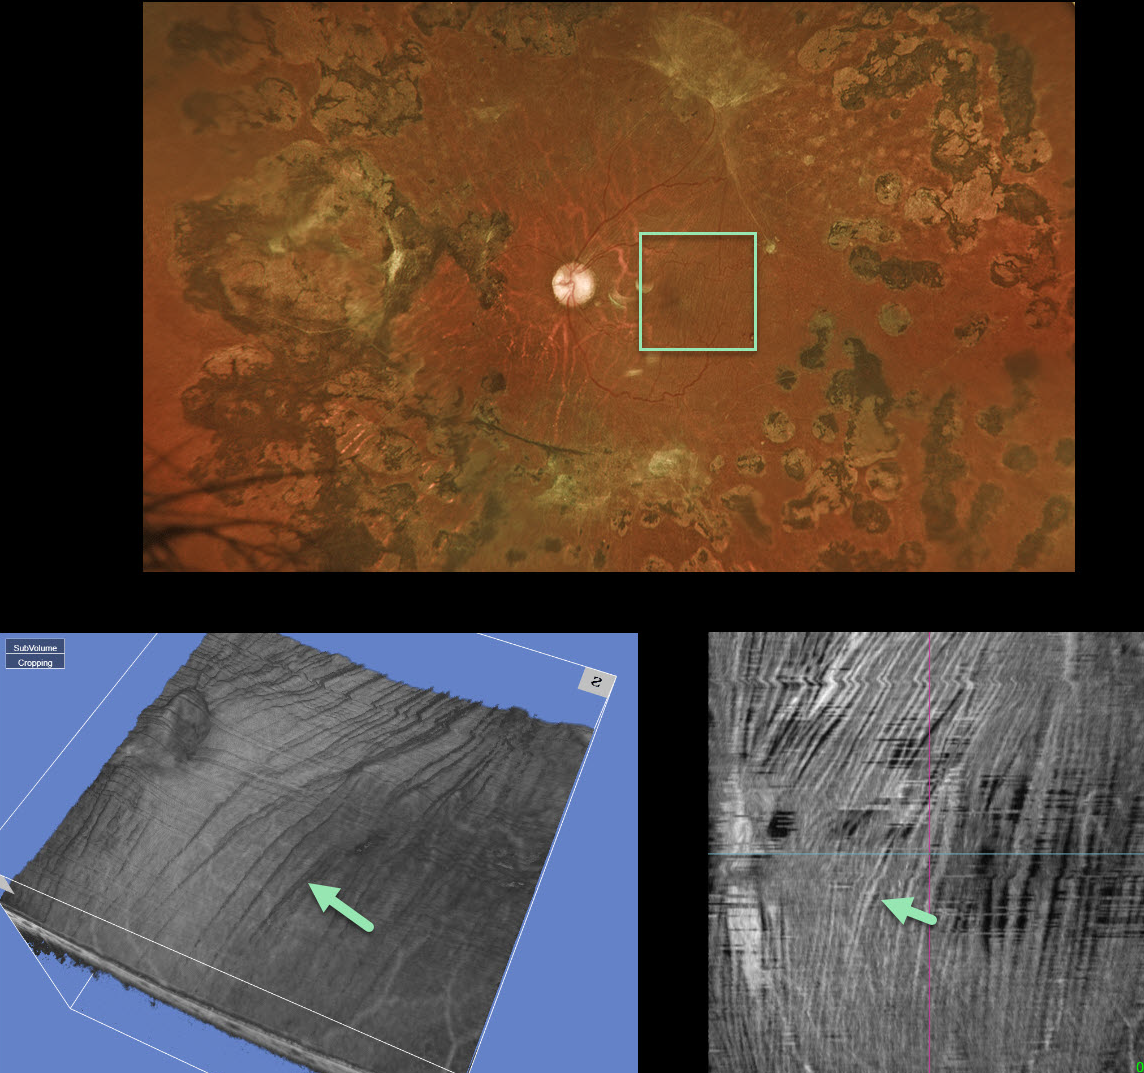
RETINAL STRIAE FOLLOWNG VITRECTOMY FOR DIABETIC TRD
Originally posted on @retina.rocks May 21, 2020
This 35 YO male had a severe diabetic tractional retinal detachment with subsequent pars plana vitrectomy a few years prior.
Now, macular striae are apparent in the inner retina and are especially dramatic on en face imaging (image 4). Remarkably, this patient maintains 20/40 vision. It is quite common for these postoperative traction detachments to have residual retinal striae, which usually don’t adversely affect vision.
Learning Points:
En face OCT is extremely helpful in evaluating and managing retinal disease, offering a unique perspective for viewing pathology.
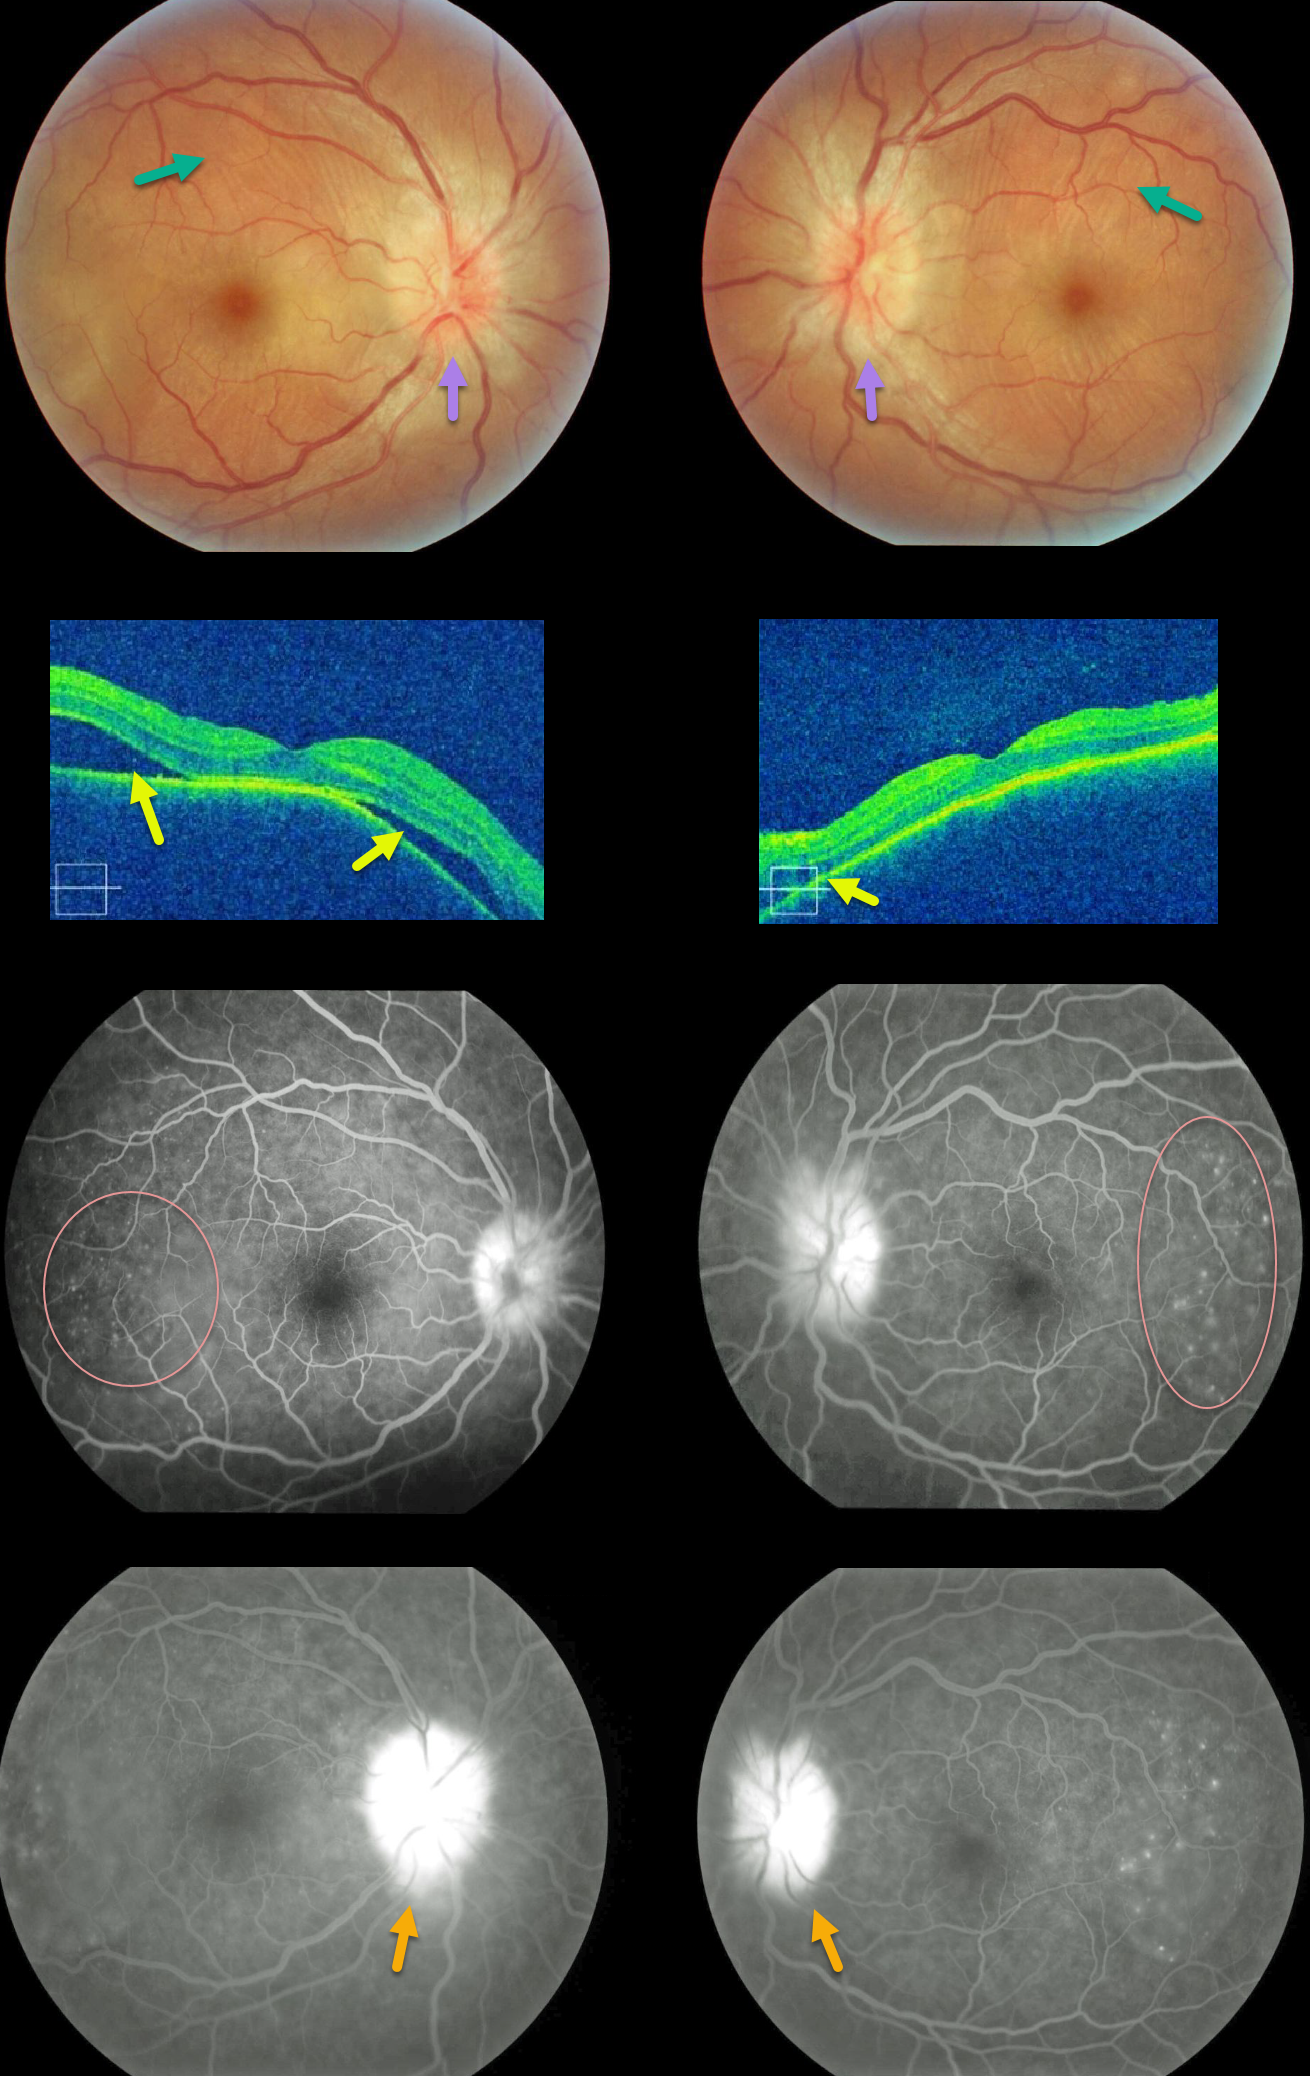
HARADA DISEASE
Originally posted on @retina.rocks May 19, 2020
Our patient shows classic findings for acute Harada’s. The fundus photos and OCT images show bilateral multifocal subretinal exudative detachments with irregular, scattered overlying chorioretinal folds and bilateral optic disc swelling.
Fluorescein angiography (FA) shows multifocal subretinal leaks with pooling of fluid below the retina and within outer retinal cystoid spaces, along with leaking “hot” nerves.
These findings dramatically resolved after just 1 week of oral prednisone (not pictured).
Learning Points:
Bilateral, multifocal yellow-white, serous retinal detachments are the hallmark sign of acute Vogt-Koyanagi-Harada (VKH) disease.
The choroid is markedly thickened with overlying chorioretinal folds. The multiple sets and various orientations of these folds are quite different from those seen with idiopathic chorioretinal folds.
The optic nerves are usually inflamed and swollen. Patients often have a panuveitis with anterior chamber and vitreous cells.
Those with just ocular findings have Harada disease, whereas patients with additional systemic findings (including vitiligo, poliosis, headache, vertigo, and hearing loss) have Vogt-Koyanagi-Harada disease.


