

Rhegmatogenous Retinal Detachment (RRD) Meniscus Micropyon
<< Back to Cases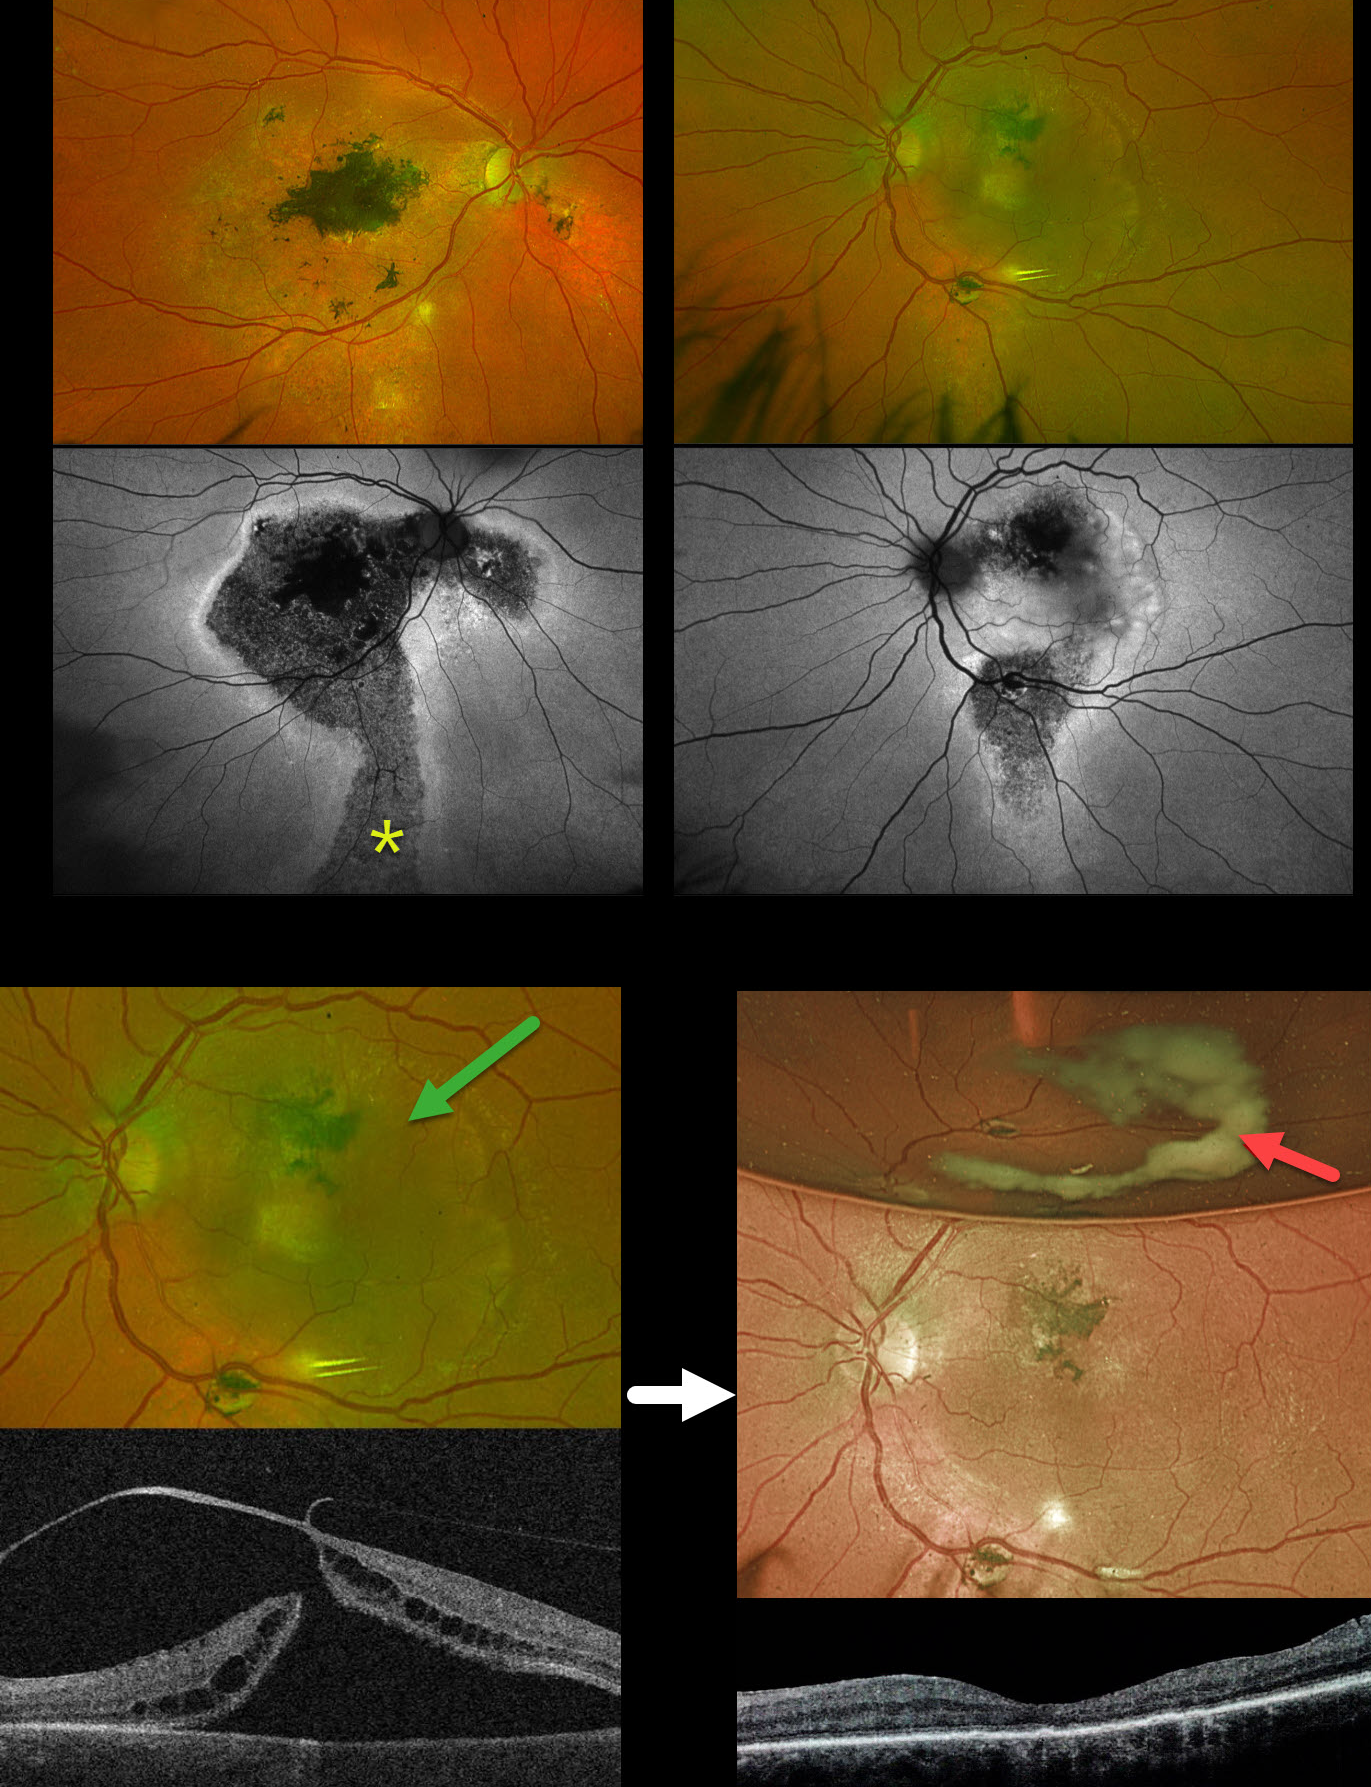
PRIOR CHRONIC ICSC WITH NEW TRACTIONAL MACULAR HOLE-RRD WITH POSTOPERATIVE MENISCUS MICROPYON
Originally posted on @retina.rocks October 29, 2025
This 58YO male was referred for a retinal detachment in his left eye. He has a long history of idiopathic central serous chorioretinopathy (ICSC). He was previously treated elsewhere for neovascular AMD OD. For many years, he has been receiving intravitreal Avastin OS every 1-2 months. Vision was counting fingers OD and 20/400 OS.
Optos color RG imaging shows bilateral macular scarring with confluent hyperpigmented foveal changes and intraretinal pigment migration, especially in his right eye. Inferior hypopigmented gutters are most obvious on fundus autofluorescence (FAF) as hypo-FAF with surrounding hyper-FAF margins. A rhegmatogenous retinal detachment (RRD) occupies the entire left macula. Triton swept-source OCT shows a full-thickness macula hole, active vitreoretinal traction on the temporal edge of the hole, and a macular detachment.
The tractional macular hole with secondary RRD in our patient’s left eye is completely unrelated to his poorly treated ICSC. One month following vitrectomy, vision improved to 20/100. The retina was completely attached, and the macular hole was closed. A meniscus micropyon is adherent to the inferior meniscus of the gas bubble.
Learning Points:
Photodynamic therapy (PDT) is currently the standard of care for ICSC with symptomatic acute or chronic subretinal fluid. Unfortunately, Visudyne is rarely available outside the US, which has led to the adoption of unproven therapies, including mineralocorticoid receptor antagonists (eplerenone), beta blockers, and intravitreal anti-VEGF agents. Recent meta-analyses and systematic reviews confirm that these alternative therapies are ineffective (Felipe et al Int J Retina Vitreous 2022;8;34 and Kim et al Ophthalmology 2025;132:343-353). Despite the clear lack of efficacy in the literature, specialists both within and outside the US continue to use these drugs (Vankatesh et al Int J Retina Vitreous 2023;9;61). Our patient’s macular findings are a testament to what can happen when proven therapies are ignored.
Russell et al recently reported a unique ophthalmoscopic sign, a meniscus micropyon, that follows PPV with gas tamponade for all causes (Retina 2024;44:1766-1776). Features they noted that distinguish this sterile micropyon from post-PPV fibrin include a delayed appearance, hyperautofluorescence, and absence of anterior chamber or vitreous fibrinous strands/sheets. Vitreous biopsy in two of their cases revealed predominantly white blood cells. The micropyon appearance was associated with epiretinal proliferation (80%). Recurrent RRD from proliferative vitreoretinopathy (PVR) developed 33% of eyes, 12% re-detached without frank PVR, and 18% developed worsening epiretinal membranes.
Our patient’s meniscus micropyon disappeared as the bubble resolved. Three months postoperatively, vision was 20/60, and the retina remained completely reattached without PVR.
MENISCUS MICROPYON
Mattie Adams
Originally posted on @retina.rocks April 3, 2025
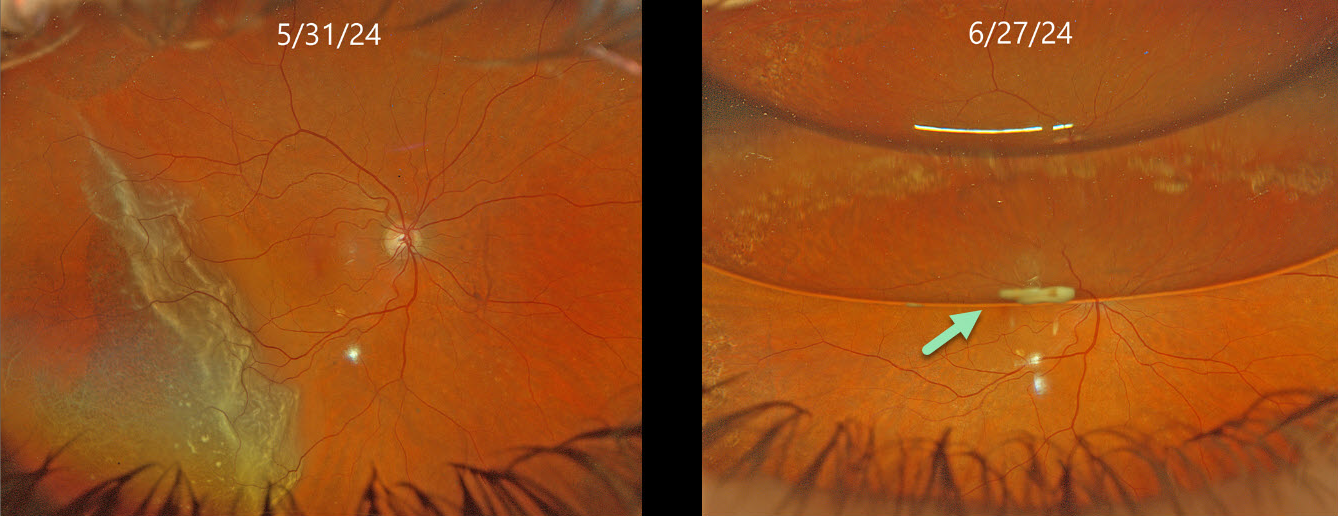
This 72YO female presented with one day of peripheral vision loss in her right eye. Vision was 20/25 OD and 20/25 in her healthy OS.
Optos color RG imaging (image 2, top) shows a temporal macula-on rhegmatogenous retinal detachment (RRD). Pars plana vitrectomy (PPV) with a C3F8 bubble was performed later that day. On her 1-month postoperative visit, vision was 20/50 with about a 50% gas bubble. A greyish globular deposit was adherent to the inferior edge of the gas meniscus.
Learning Points:
Russell et al recently reported a unique ophthalmoscopic sign, a meniscus micropyon, that follows PPV with gas tamponade for all causes (Retina 2024;44:1766-1776). Features they noted that distinguish this sterile micropyon from post-PPV fibrin include delayed appearance, hyperautofluorescence, and absence of fibrinous strands or sheets in the anterior chamber or vitreous. Vitreous biopsy in two of their cases revealed predominantly white blood cells. The micropyon appearance was associated with epiretinal proliferation (80%). Recurrent RRD from proliferative vitreoretinopathy (PVR) developed in 33% of eyes, 12% re-detached without frank PVR, and 18% developed worsening epiretinal membranes.
Fortunately, our patient’s postoperative course was uneventful. The micropyon resolved at the following visit and 4 months postoperatively, vision was 20/20 and the retina remained completely attached without epiretinal proliferation (not shown). Since the publication of Russell’s article, we have seen several patients with this biomarker, so we suspect it to be a not uncommon finding.
CHOROIDAL DETACHMENT
Originally posted on @retina.rocks December 11, 2023
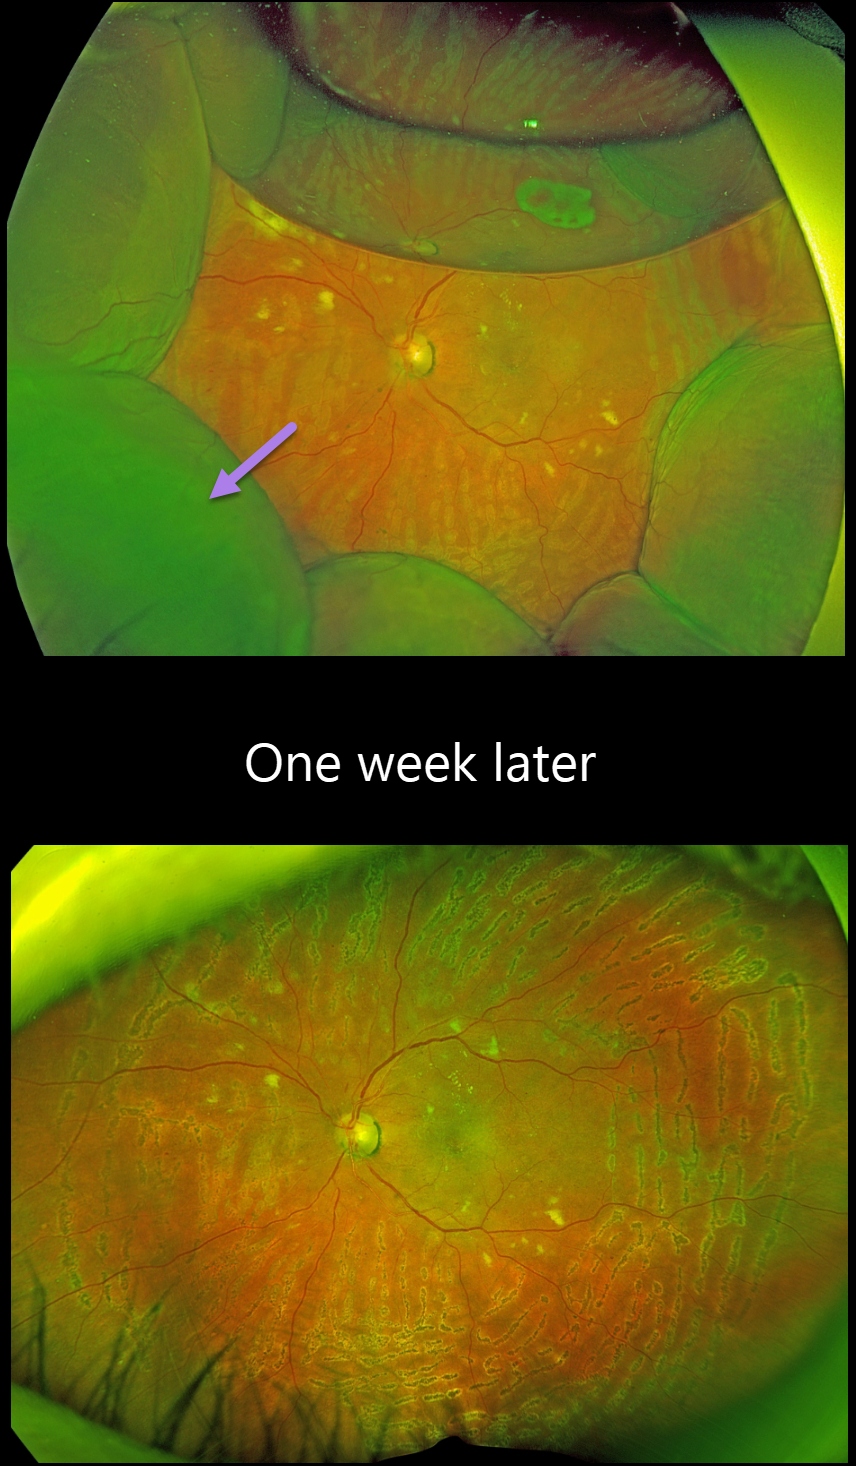
This 66YO female presented for her postoperative exam following an uneventful pars plana vitrectomy one day earlier for a diabetic traction retinal detachment.
Optos RG imaging shows 360 degrees of peripheral choroidal detachments with a 30% air bubble. Fresh panretinal photocoagulation burns are noted, and the retina is attached. All wounds were secure, and the intraocular pressure was 20mmHG.
We are not sure why our patient presented with these choroidals 1 day postoperatively, since her pressure was normal and there were no wound leaks.
Uveal effusion is a rare transient complication following heavy panretinal photocoagulation (Gentile et al, Ophthalmology 1996;103:827-832), although our patient’s endolaser did not appear overly intense.
When examined one week later, vision was 20/400, and the IOP was 17. The choroidals had spontaneously and completely resolved.


