

Serpiginous Choroidopathy
<< Back to Cases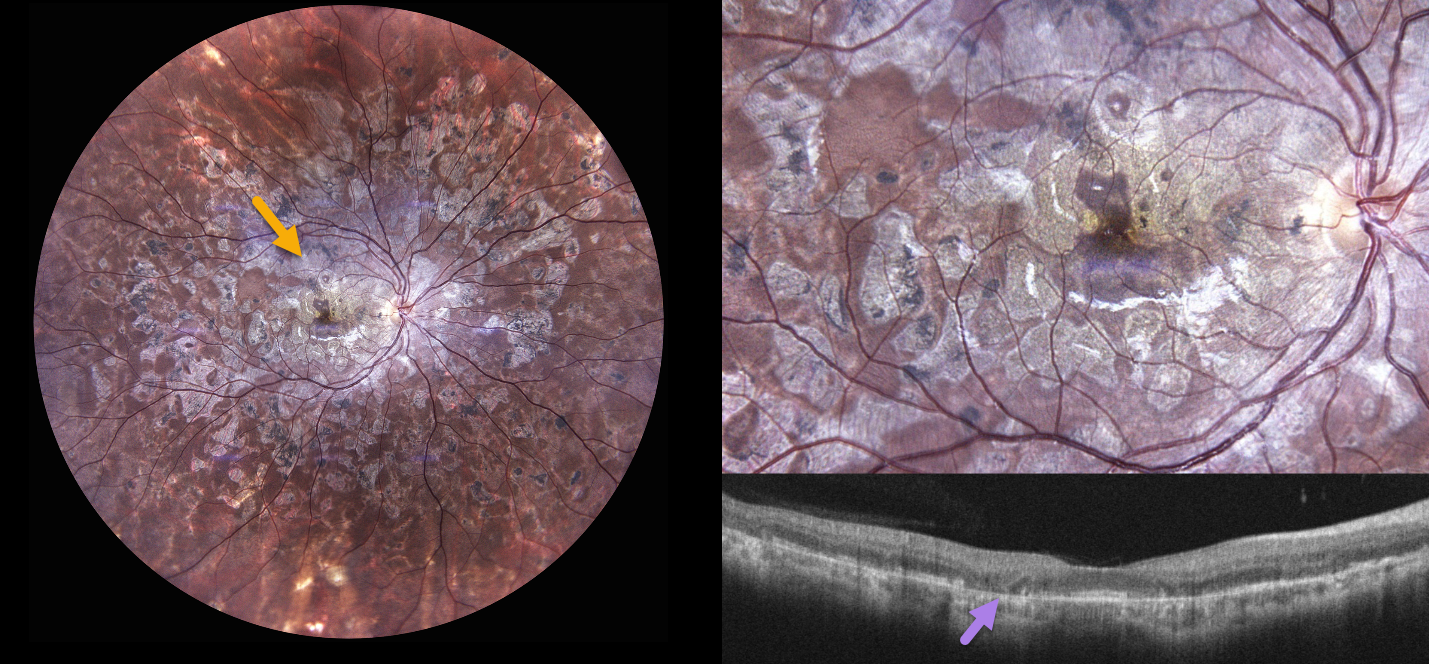
TUBERCULAR SERPIGINOUS-LIKE CHOROIDITIS
Aniruddh Soni
Originally posted on @retina.rocks July 6, 2026
A 30YO female presented with a 1.5-year history of bilateral floaters and blurred vision. She was diagnosed elsewhere with ‘choroiditis’ and treated with oral steroids and azathioprine, with 2 recurrences. When seen in our office, vision was 20/30 OU.
Color photography OD shows extensive, variably confluent, and meandering chorioretinal scarring extending from the disc and macula to the retinal periphery. The foveal center is just spared. OCT scanning shows variable outer retinal and RPE atrophy. Identical findings were noted in her left eye (not shown).
Tuberculin skin testing and QuantiFERON-TB Gold were positive. She was referred to pulmonary and infectious disease specialists, was diagnosed with latent TB, and started on anti-tuberculosis treatment (ATT) with tapering oral steroids.
Learning Points:
Although TB most commonly presents with pulmonary involvement, extrapulmonary sites can involve the gastrointestinal, skin, cardiovascular, genitourinary, and central nervous systems, as well as the eyes. Ocular involvement, like syphilis, can mimic virtually any type of uveitis, including anterior, intermediate, posterior, and panuveitis, retinitis, and retinal vasculitis, neuroretinitis, optic neuropathy, choroidal granuloma, choroiditis, and scleritis.
Tubercular serpiginous-like choroiditis mimics serpiginous but affects younger patients with more multifocal and peripheral recurrences, foveal sparing, vitritis, and progression if untreated (Agarwal et al, AJO 2020;220:160-169). Although the exact mechanism is not yet clear, a direct or indirect infectious trigger by the Mycobacterium tuberculosis is thought to cause choroiditis. Its origin is probably immunogenic, as it appears to respond to corticosteroids and other immunosuppressants. Our patient was a bit unusual in that he required systemic steroids, ATT, and adalimumab to finally control his disease.
SERPIGINOUS CHORIORETINOPATHY
César Adrián Gómez Valdivia
Originally posted on @retina.rocks June 2, 2026
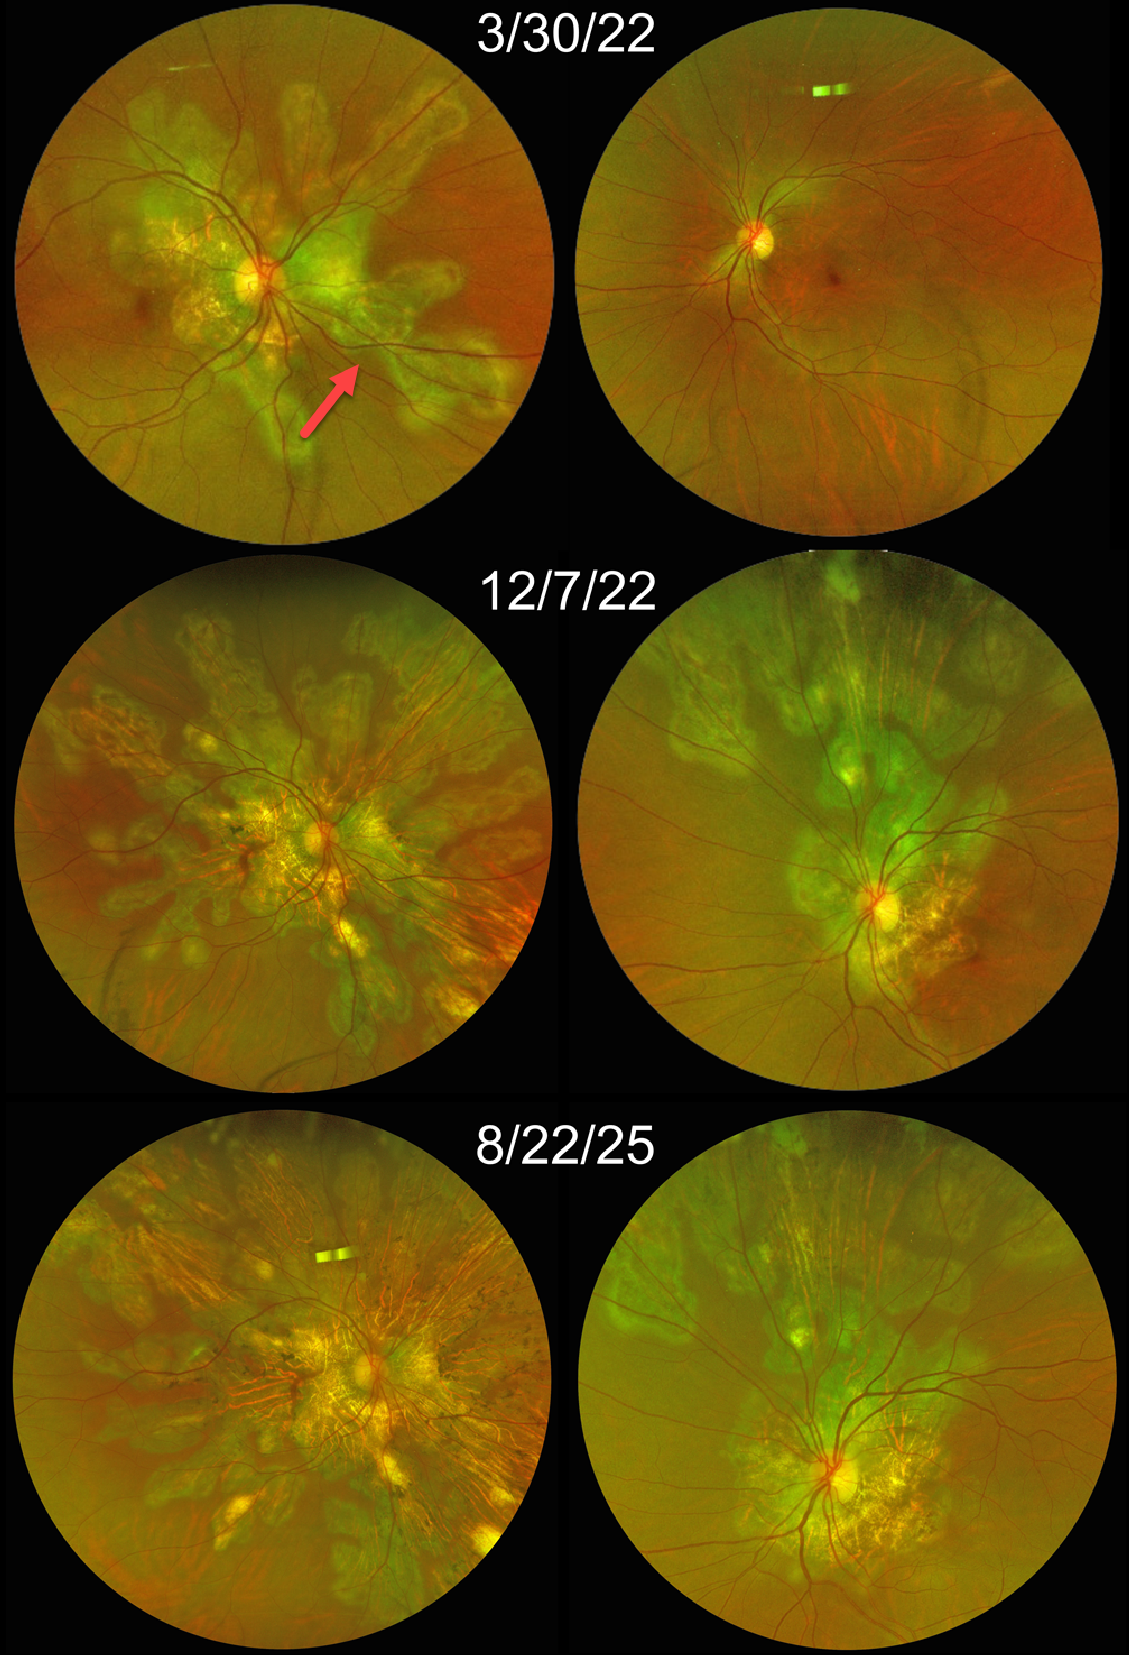
This 41YO female presented on 3/30/22 with a paracentral scotoma and metamorphopsia in her right eye. Vision was 20/800 OD and 20/20 in his initially normal OS.
Optos color RG imaging at that time shows multifocal meandering scars radiating outwards from the disc and macula, consistent with serpiginous chorioretinopathy. All scarring appears inactive except for a possible active lesion inferonasally. General laboratory testing and chest CT were all negative. The PPD was positive; however, given that she lived in a TB-endemic area, this was further evaluated with QuantiFERON, which was negative.
Over the following months, the disease evolved in a chronic relapsing pattern, with recurrent and aggressive activity despite intravenous methylprednisolone pulses along with cyclophosphamide.
When last examined on 8/22/25, vision was hand motion OD and 20/150 OS. Current systemic therapy includes azathioprine 100 mg and prednisone 60 mg daily. She is currently awaiting initiation of adalimumab as biologic immunomodulatory therapy, with the goal of achieving better inflammatory control and reducing cumulative corticosteroid exposure.
Learning Points:
Serpiginous choroiditis is an idiopathic, usually bilateral chorioretinal inflammatory condition, most commonly found in middle-aged men (Khanamiri and Rao, Surv Ophthalmology 2013;58:203-232). Recurrent areas of inflammation develop along the edge of a previous scar, producing scarring that meanders from the optic nerve outward into the macula. Vision is good unless scarring or macular neovascularization extends through the macular center. There is no consensus on the optimal systemic treatment, including corticosteroids and steroid-sparing agents.
TUBERCULAR SERPIGINOUS-LIKE CHOROIDITIS
Akansha Sharma
Originally posted on @retina.rocks March 9, 2026
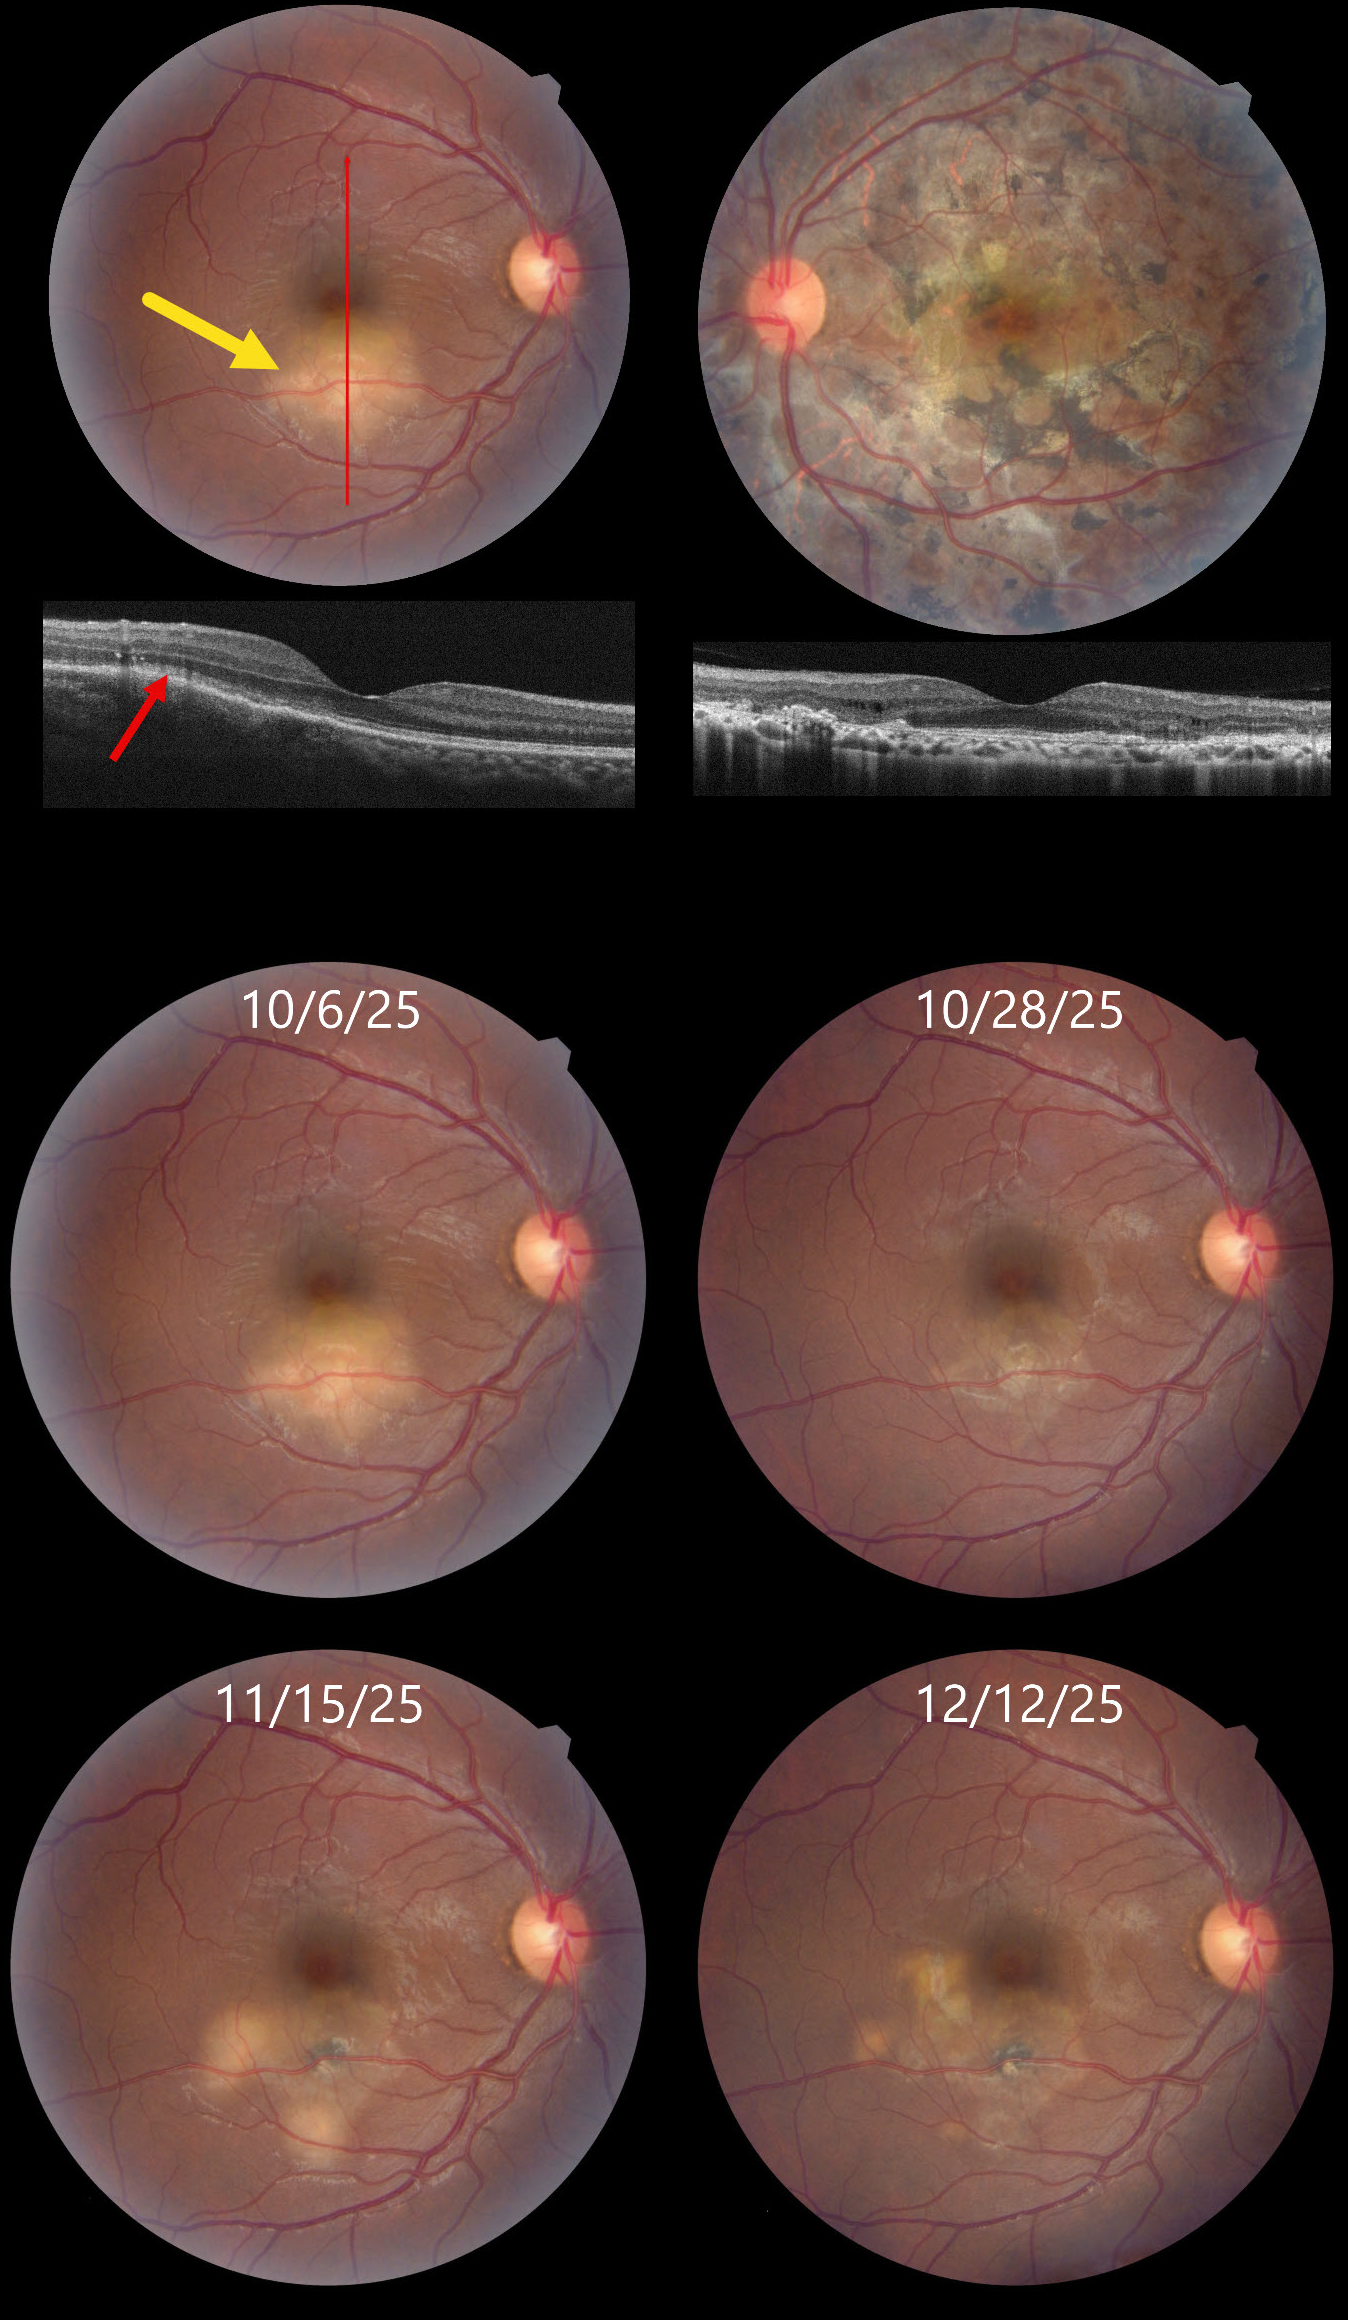
This 32YO male presented on 10/6/25 with a 6-day history of decreased vision in his right eye. About 2 years earlier, he was diagnosed elsewhere with tubercular serpiginous-like choroiditis in his left eye. Extensive workup at the time, including a chest X-ray, was negative except for a positive QuantiFERON TB Gold result. He was lost to follow-up without treatment for his latent tuberculosis (TB). Vision in our office was 20/30 OU.
Color photography shows a deep, creamy-white retinal inflammatory lesion in the inferior macula. OCT shows outer retinal hyperreflectivity with loss of the outer retinal band details. Extensive scarring is noted throughout the left posterior pole, with a small island of preserved foveal tissue.
Tapering systemic corticosteroid therapy was begun, followed by anti-tuberculosis treatment. Over the ensuing 2 months, he experienced waxing and waning inflammation necessitating intravitreal Ozurdex, oral steroids, and adalimumab while vision remained stable at 20/30. We continue to follow him closely.
Learning Points:
Although TB most commonly presents with pulmonary involvement, extrapulmonary sites can include the gastrointestinal, skin, cardiovascular, genitourinary, and central nervous systems, as well as the eyes. Ocular involvement, like syphilis, can mimic virtually any type of uveitis, including anterior, intermediate, posterior, and panuveitis, retinitis, and retinal vasculitis, neuroretinitis, optic neuropathy, choroidal granuloma, choroiditis, and scleritis.
Tubercular serpiginous-like choroiditis mimics serpiginous but affects younger patients with more multifocal and peripheral recurrences and progression if untreated (Agarwal et al, AJO 2020;220:160-169). Although the exact mechanism is not yet clear, a direct or indirect infectious trigger by the Mycobacterium tuberculosis is thought to cause choroiditis. Its origin is probably immunogenic since it seems to respond to corticosteroids and other immunosuppressants. Our patient was a bit unusual in that he required systemic steroids, ATT, and adalimumab to finally control his disease.
TUBERCULAR SERPIGINOUS-LIKE CHOROIDITIS
The European VitreoRetinal Society (EVRS) and Vaibhav Sethi
Originally posted on @retina.rocks January 2, 2026
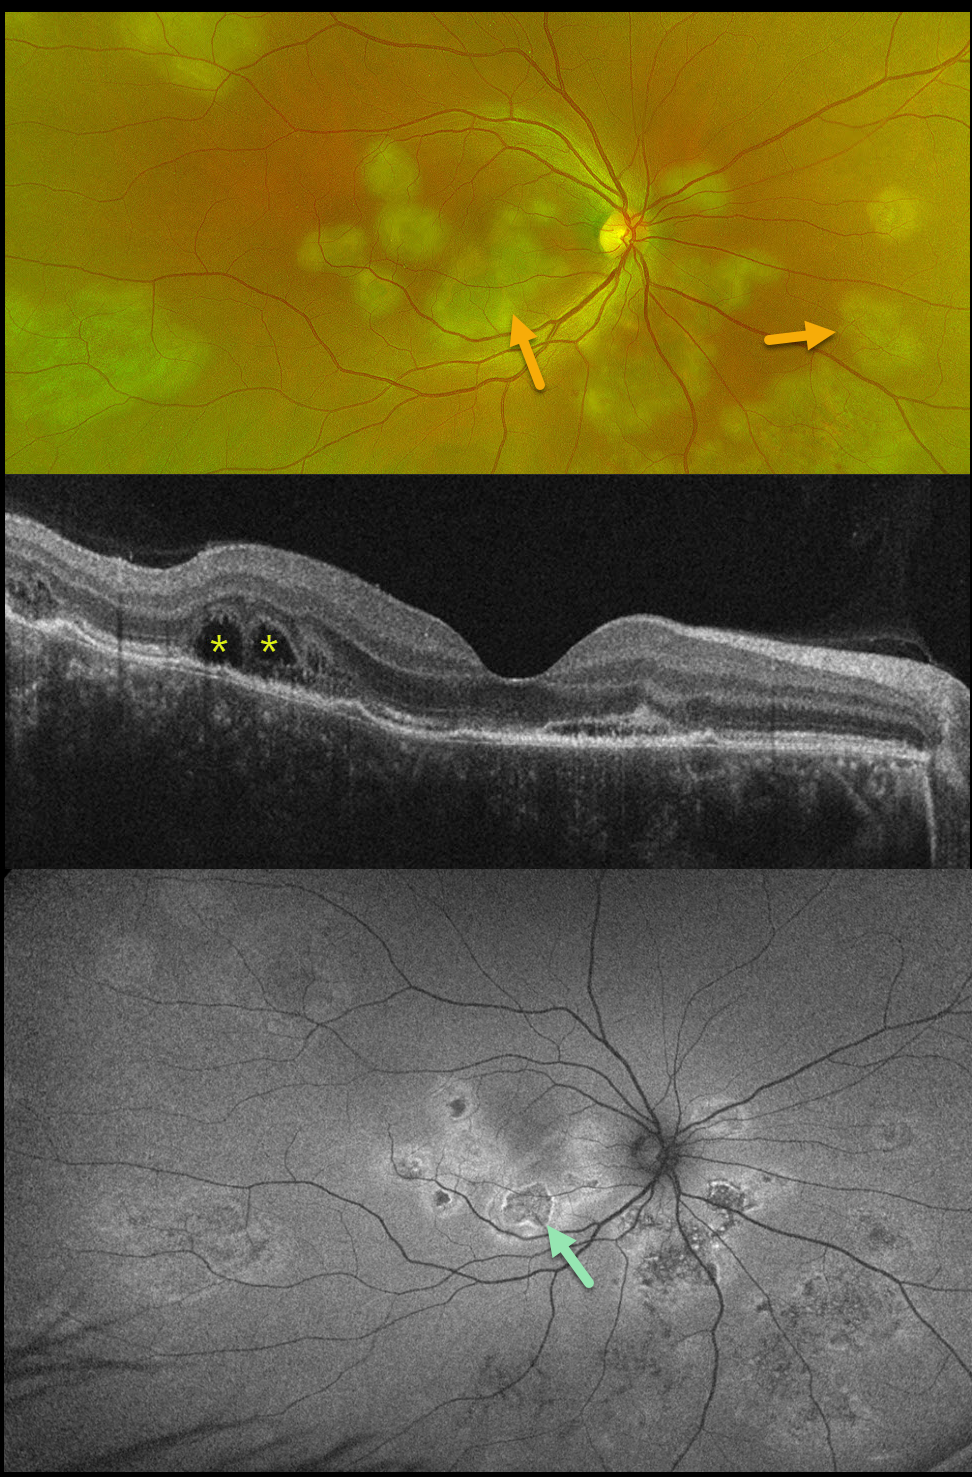
This previously healthy 41YO male presented with 4 days of blurred vision in his right eye. Vision was 20/80 OD and 20/20 in his normal OS.
Optos color RG imaging shows multifocal subretinal creamy white placoid lesions in the macula, peripapillary retina, and midperiphery. OCT scanning shows variable disruption of the outer retinal bands, as well as bacillary layer detachments (BALAD) temporally. The placoid lesions on fundus autofluorescence (FAF) show variable central hypo-FAF with more hyper-FAF borders.
Mantoux skin testing was positive at 24mm, and chest CT revealed left lower lobe ground glass opacities with hilar adenopathy. He was started on anti-tubercular therapy and oral prednisone.
Although tuberculosis most commonly presents with pulmonary involvement, extrapulmonary sites can include the gastrointestinal, skin, cardiovascular, genitourinary, and central nervous systems, as well as the eyes. Ocular involvement, like syphilis, can mimic virtually any type of uveitis, including anterior, intermediate, posterior, and panuveitis, retinitis, and retinal vasculitis, neuroretinitis, optic neuropathy, choroidal granuloma, choroiditis, and scleritis.
Learning Points:
Tubercular serpiginous-like choroiditis mimics serpiginous but affects younger patients with more multifocal and peripheral recurrences and progression if untreated (Agarwal et al, AJO 2020;220:160-169). Although the exact mechanism is not yet clear, a direct or indirect infectious trigger by the Mycobacterium tuberculosis is thought to cause choroiditis. Its origin is probably immunogenic since it seems to respond to corticosteroids and other immunosuppressants.
BALAD appears as a unique dome-shaped collection of intraretinal fluid from photoreceptor splitting. These detachments can be observed in an increasing number of conditions, most classically Vogt-Koyanagi-Harada disease (Cicinelli et al, Ophthalmology Retina 2020;4:454-456).
TUBERCULAR SERPIGINOUS-LIKE CHOROIDITIS
Originally posted on @retina.rocks March 11, 2025
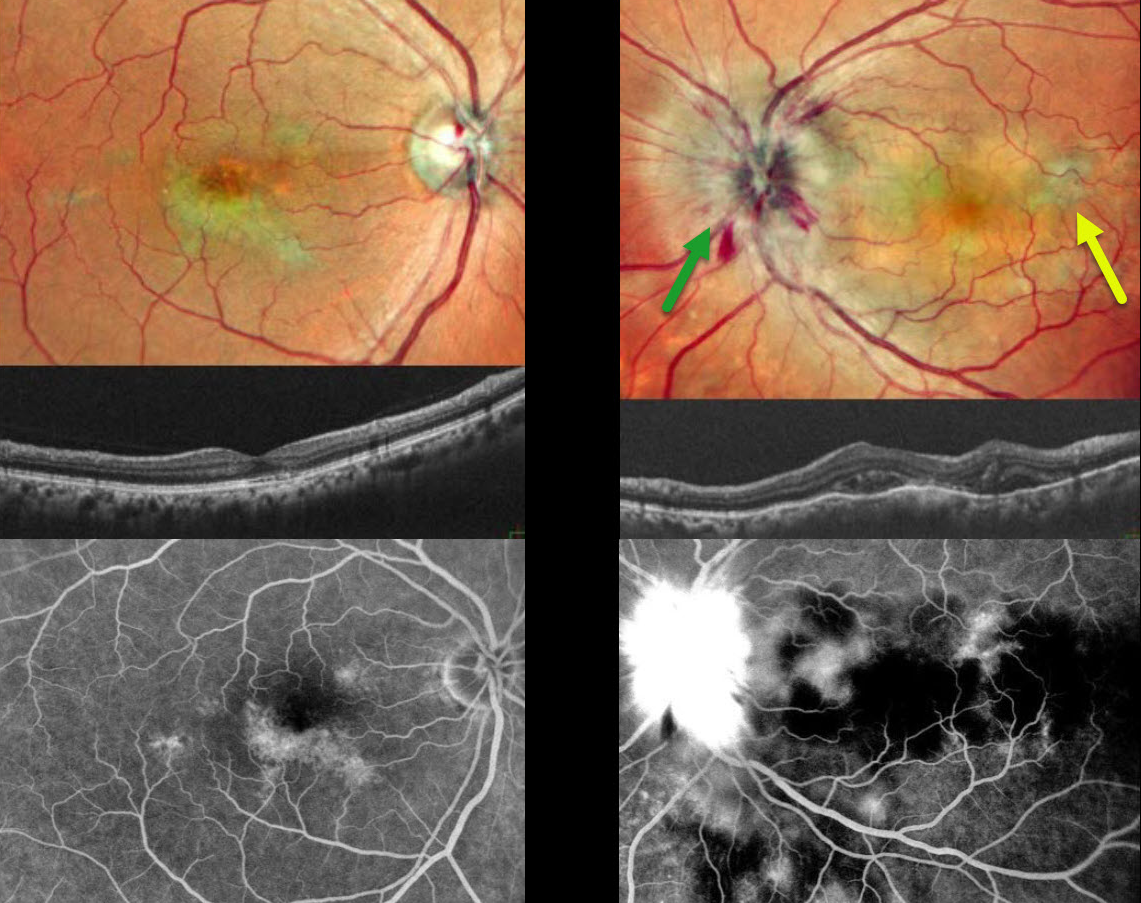
This 54YO male presented with 2 weeks of vision loss in his left eye. He was diagnosed elsewhere with papilledema, and brain MRI scanning was normal. Vision was 20/20 in his asymptomatic OD and counting fingers OS. Pseudocolor SLO imaging of the OS shows marked disc swelling with radiating hemorrhages in the nerve fiber layer. Some deep, hypopigmented retinal lesions are also seen.
OCT scanning shows irregular choroidal thickening vs choroidal folds with overlying pockets of variably reflective subretinal fluid. The right eye shows multifocal serpiginous-like areas of chorioretinal scarring with variable outer retinal thinning on OCT.
On fluorescein angiography, the macular lesions stain OD. The left nerve shows profound leakage, and the choroidal lesions show variable blockage and staining.
We suspected tubercular serpiginous-like choroiditis OD with acute tubercular papillitis and choroiditis OS. Chest X-ray showed a mass pressing on the trachea. Chest CT confirmed the mass, and subsequent biopsy revealed granulomatous thyroiditis. His Mantoux skin test was positive. We advised emergent Infectious disease consultation regarding starting anti-tubercular therapy. Unfortunately, he was immediately lost to follow-up.
Learning Points:
Although tuberculosis most commonly presents with pulmonary involvement, extrapulmonary sites can include the gastrointestinal, skin, cardiovascular, genitourinary, and central nervous systems, as well as the eyes. Ocular involvement, like syphilis, can mimic virtually any type of uveitis, including anterior, intermediate, posterior, and panuveitis, retinitis, and retinal vasculitis, neuroretinitis, optic neuropathy, choroidal granuloma, choroiditis, and scleritis.
Tubercular serpiginous-like choroiditis mimics serpiginous but affects younger patients with more multifocal and peripheral recurrences and progression if untreated (Agarwal et al, AJO 2020;220:160-169). Although the exact mechanism is not yet clear, a direct or indirect infectious trigger by the Mycobacterium tuberculosis is thought to cause the choroiditis. Its origin is probably immunogenic since it seems to respond to corticosteroids and other immunosuppressants.
SERPIGINOUS CHORIORETINITIS
Janelle Adeniran
Originally posted on @retina.rocks November 25, 2024
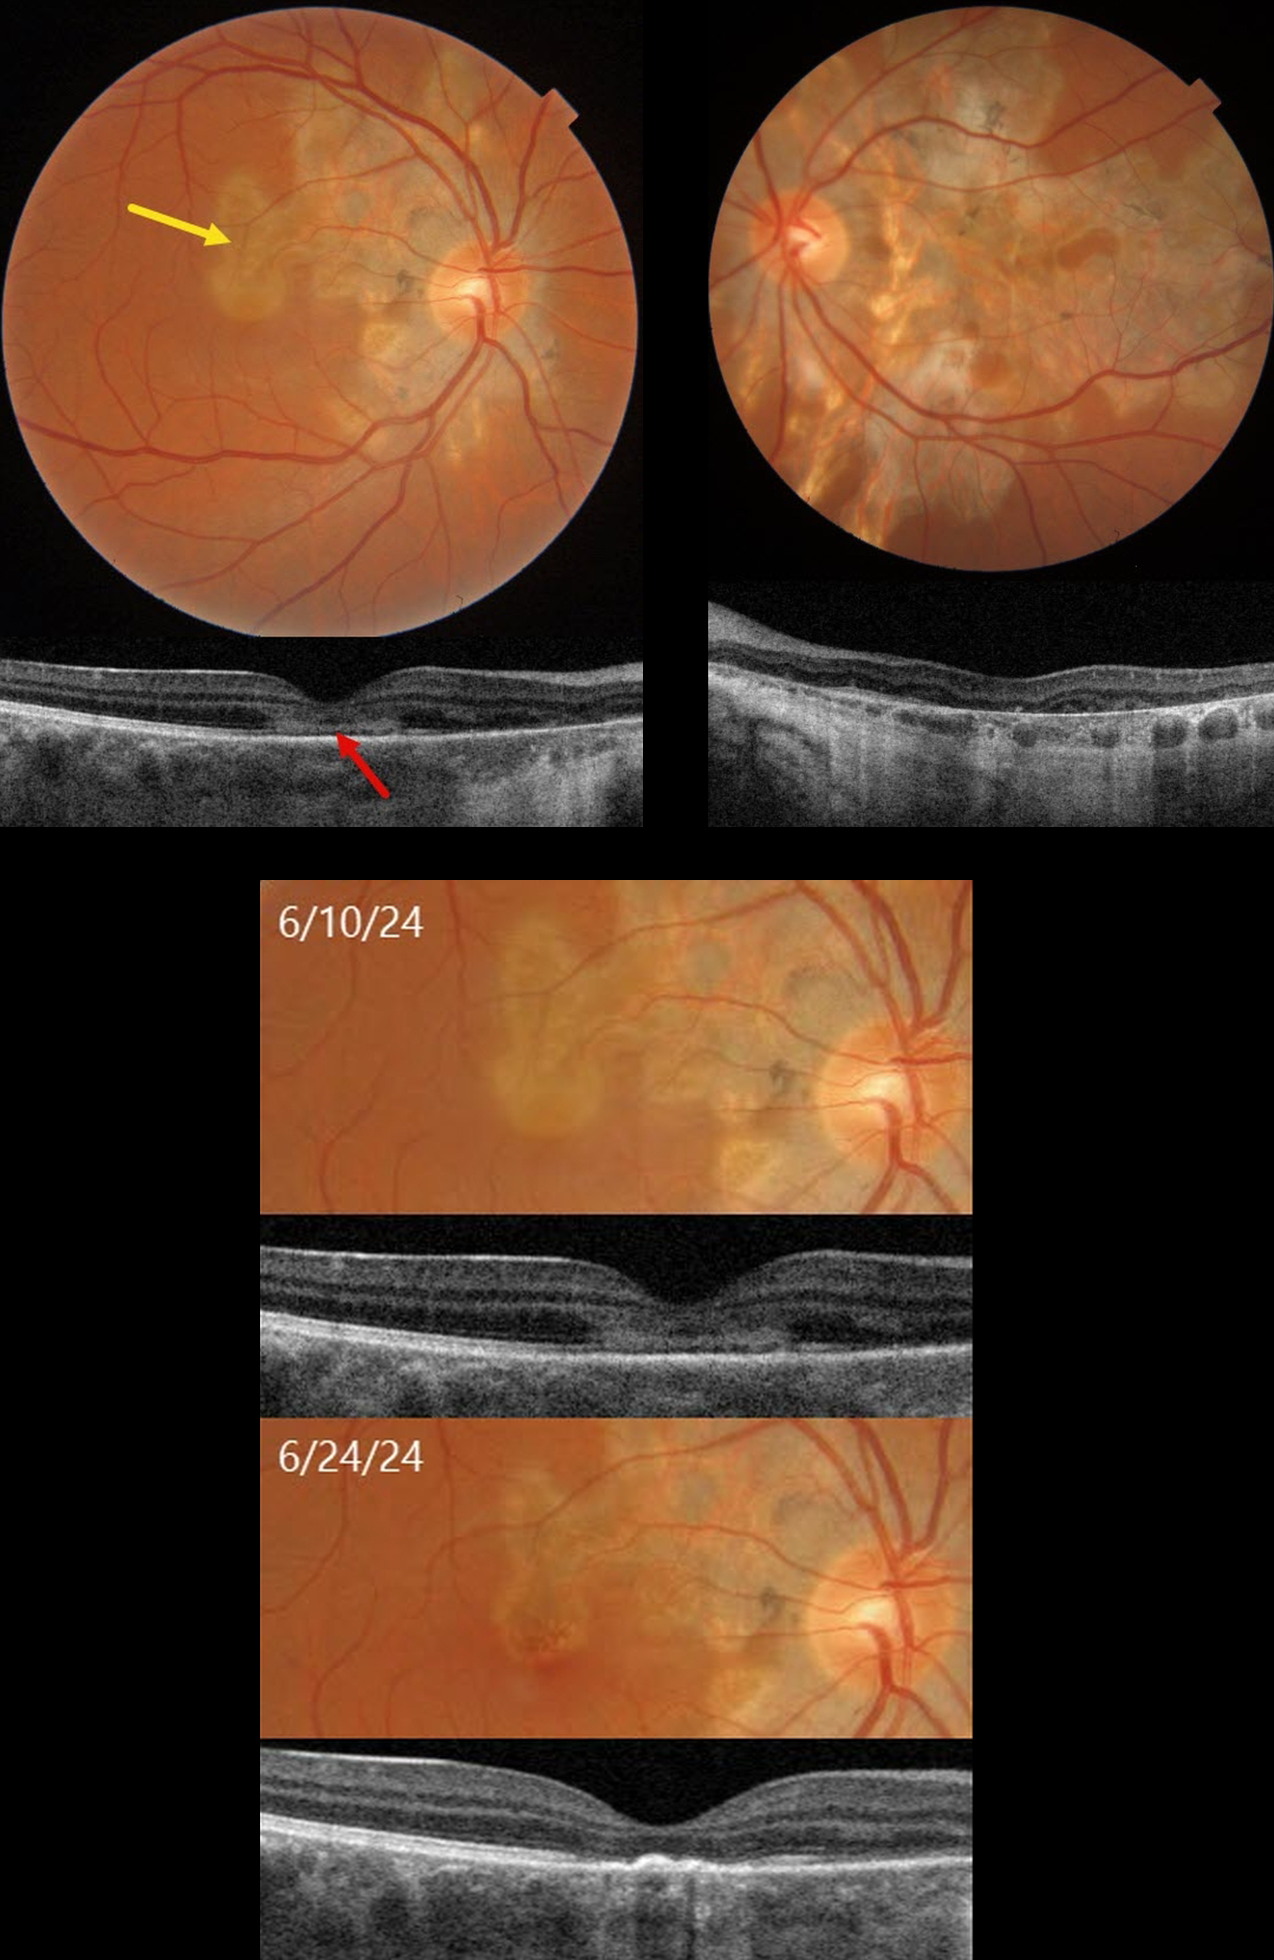
This healthy 37YO male with a known history of serpiginous chorioretinopathy presented with a few weeks of decreased vision in his left eye. Vision was 20/30 OD and 20/400 OS.
Triton color imaging shows bilateral chorioretinal scarring that radiates outwards from each optic nerve. An area of somewhat opaque active outer retinal inflammation just spares the right foveal center, with inactive scarring extending through the left fovea. The active lesion is hyperreflective on Triton swept-source OCT.
Tuberculosis testing was negative. Oral prednisone was started, and 2 weeks later, vision remained at 20/30, but there was marked regression with secondary scarring of the new lesion.
Learning Points:
Serpiginous choroiditis is an idiopathic, usually bilateral chorioretinal inflammatory condition, most commonly found in middle-aged men (Khanamiri and Rao, Surv Ophthalmology 2013;58:203-232). Recurrent areas of inflammation develop along the edge of a previous scar, producing scarring that meanders from the optic nerve outward into the macula. Vision is good unless scarring or macular neovascularization extends through the macular center. There is no consensus on the optimal systemic treatment, including corticosteroids and systemic steroid-sparing agents.
TUBERCULAR SERPIGINOUS-LIKE CHORIORETINITIS
Ogugua Okonkwo, Adekunle Olubola Hassan, Ayodele Harriman, Ogochukwu Sibeudu, and Idris Akintayo Oyekunle
Originally posted on @retina.rocks May 1, 2024
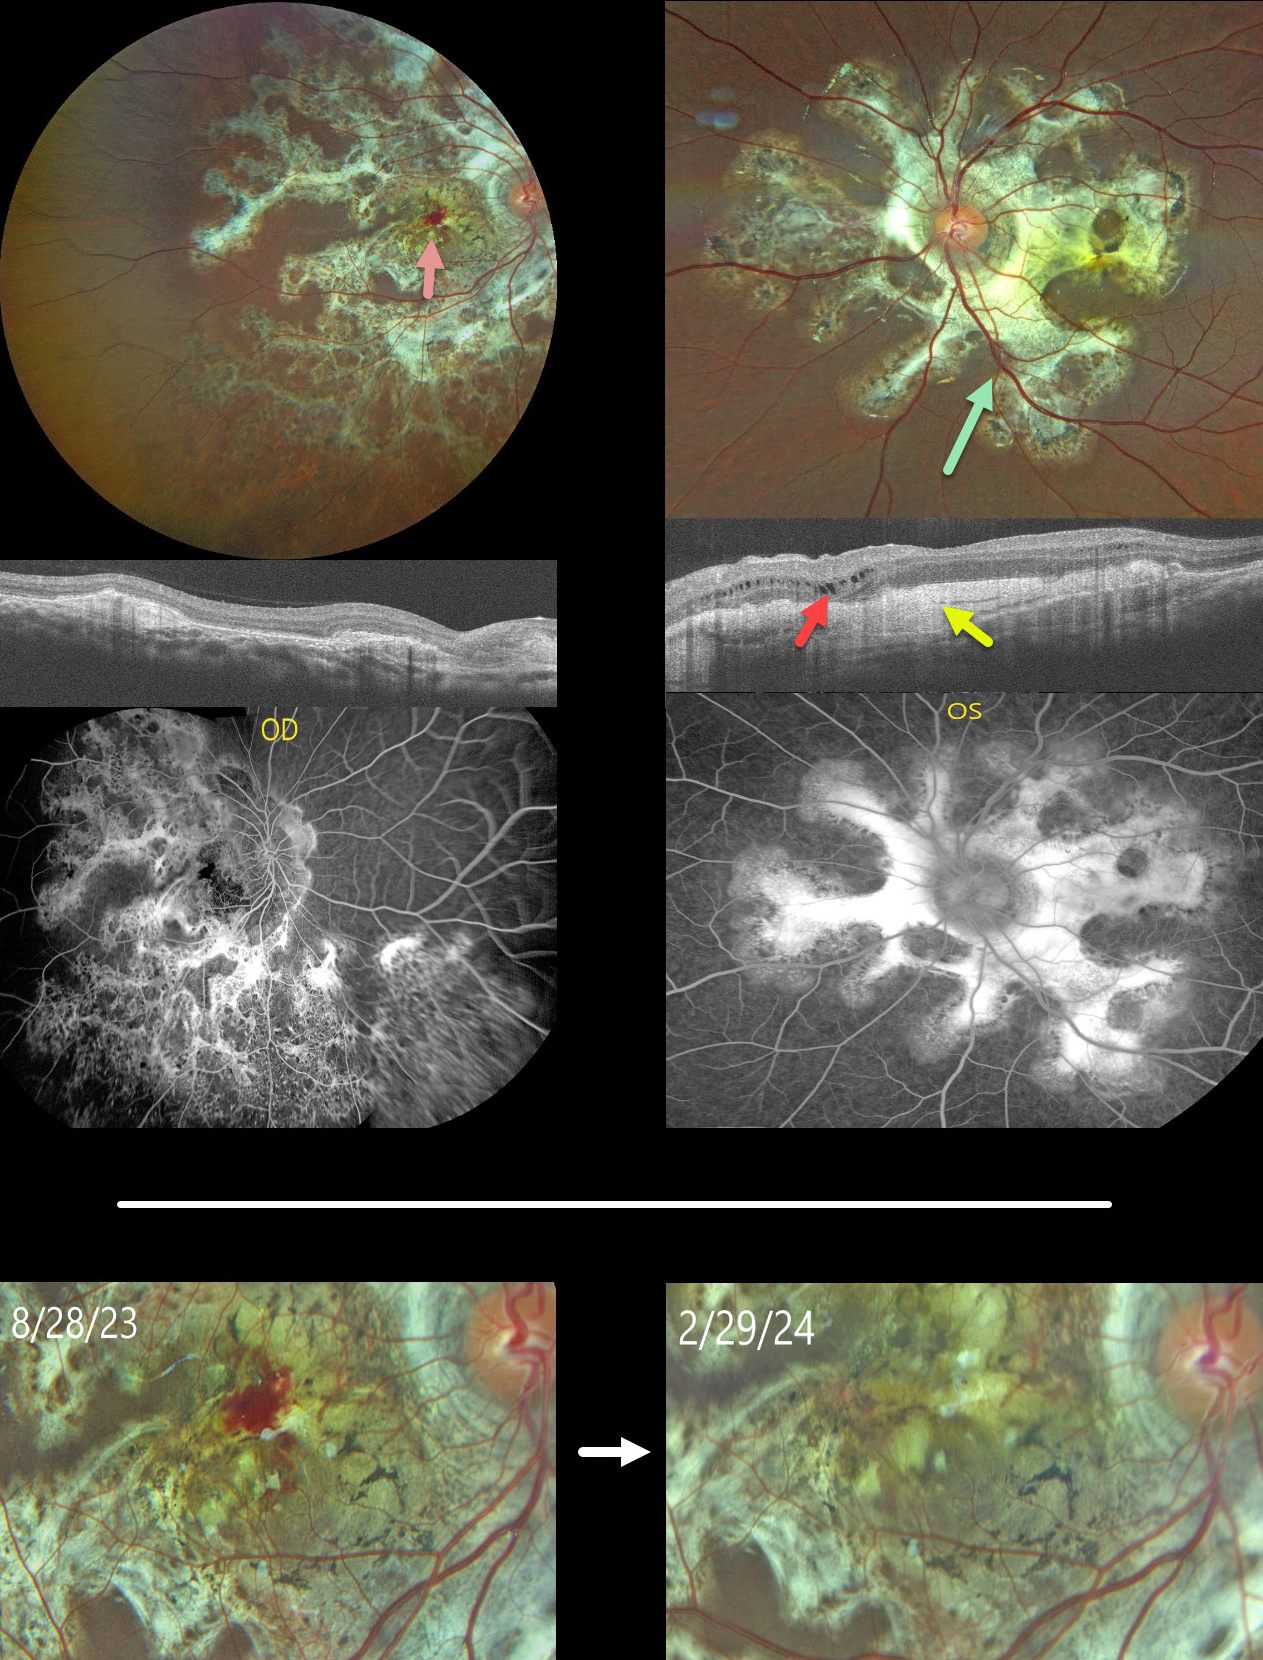
This healthy 13YO male presented with a 5-month history of bilateral vision loss. Vision was 20/200 OU.
Fundus photography shows bilateral subretinal, variably fibrotic peripapillary scarring that extends outwards with finger-like projections. A foveal hemorrhage is noted in the right macula. More mottled pigmented scarring extends into the right inferior periphery.
OCT scanning shows variable bilateral outer retinal atrophy and hyperreflective subretinal fibrosis with mild outer nuclear cysts in the nasal left macula. This scarring stains angiographically.
We were hesitant to start anti-VEGF therapy in a young boy and felt that the macular neovascularization causing the right macular blood might be inflammatory. He was therefore placed on a rapidly tapering course of oral prednisone.
At the 6-month follow-up, vision remained stable at 20/200 in this eye, with resolution of the blood.
Mantoux skin testing was negative. We have made multiple attempts to have the patient get QuantiFERON-TB Gold testing, but to date have been unsuccessful.
Learning Points:
Serpiginous choroiditis is an idiopathic, usually bilateral chorioretinal inflammatory condition, most commonly found in middle-aged men (Khanamiri and Rao, Surv Ophthalmology 2013;58:203-232). Recurrent areas of inflammation develop along the edge of a previous scar, producing scarring that meanders from the optic nerve outwards. Vision is good unless scarring or macular neovascularization extends through the macular center.
Tubercular serpiginous-like choroiditis mimics serpiginous but affects younger patients with more multifocal and peripheral recurrences and progression if untreated (Agarwal et al, AJO 2020;220:160-169). Although the exact mechanism is not yet clear, a direct or indirect infectious trigger by the Mycobacterium tuberculosis is thought to cause the choroiditis. We believe our patient has this diagnosis and will continue to confirm it with further testing.
TUBERCULAR SERPIGINOUS-LIKE CHORIORETINITIS
Asma Samsudeen and Ashish Sharma
Originally posted on @retina.rocks January 18, 2024
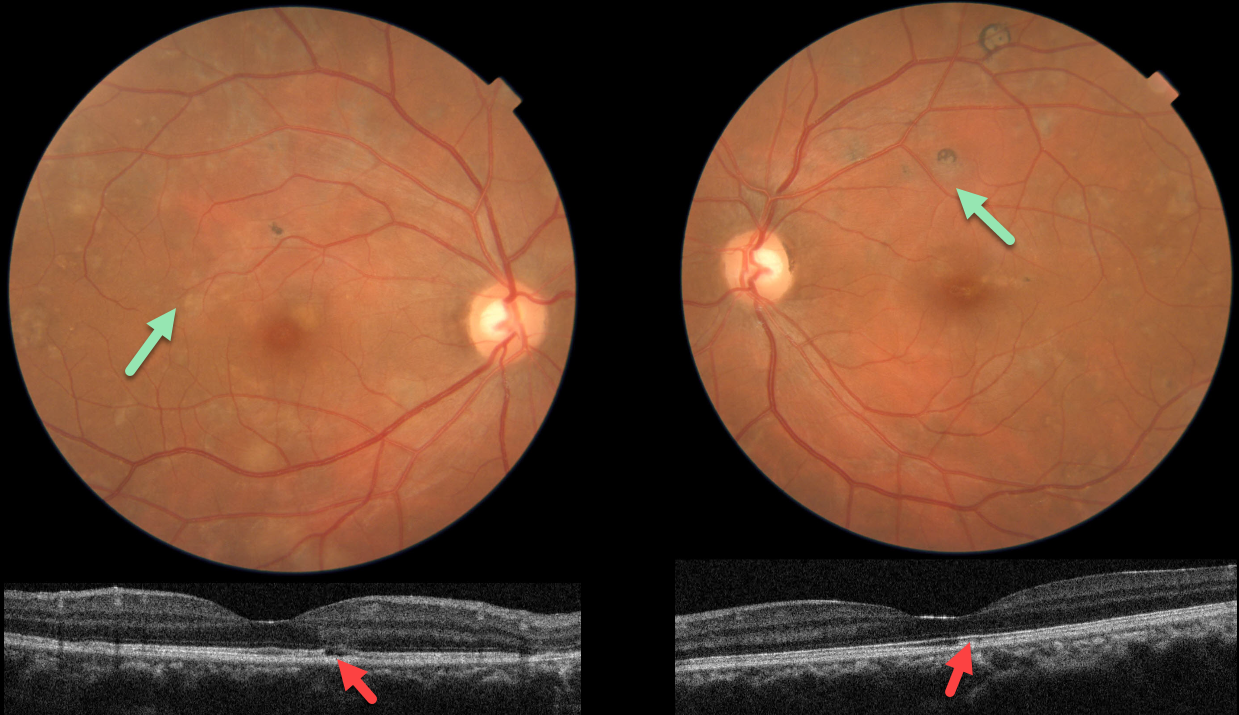
This 38YO male presented with floaters in each eye. He denied any past medical history. Vision was 20/20 OU.
Fundus photos show multifocal patches of variably pigmented chorioretinal scarring throughout each posterior pole.
OCT scanning in each eye shows variable outer retinal atrophy and ellipsoid disruption. Unfortunately, fundus autofluorescence and fluorescein angiography are not available.
Subsequent workup was consistent for active tuberculosis, including a positive QuantiFERON-TB Gold and chest x-ray findings. Systemic anti-tuberculous therapy was begun.
Learning Points:
Serpiginous choroiditis is an idiopathic, usually bilateral chorioretinal inflammatory condition most commonly found in middle-aged men (Khanamiri and Rao, Surv Ophthalmology 2013;58:203-232).
Recurrent areas of inflammation develop along the edge of a previous scar, producing scarring that meanders from the optic nerve outwards. Vision is good unless scarring or macular neovascularization extends through the macular center.
Tubercular serpiginous-like choroiditis mimics serpiginous, but affects younger patients with more multifocal and peripheral recurrences and progression if untreated (Agarwal et al, AJO 2020;220:160-169).
Although the exact mechanism remains unclear, a direct or indirect infectious trigger by Mycobacterium tuberculosis is believed to cause choroiditis.
SERPIGINOUS CHORIORETINITIS
Borivoje Ivezić, Nataša Drača, and Emma Oreškovič
Originally posted on @retina.rocks January 2, 2024
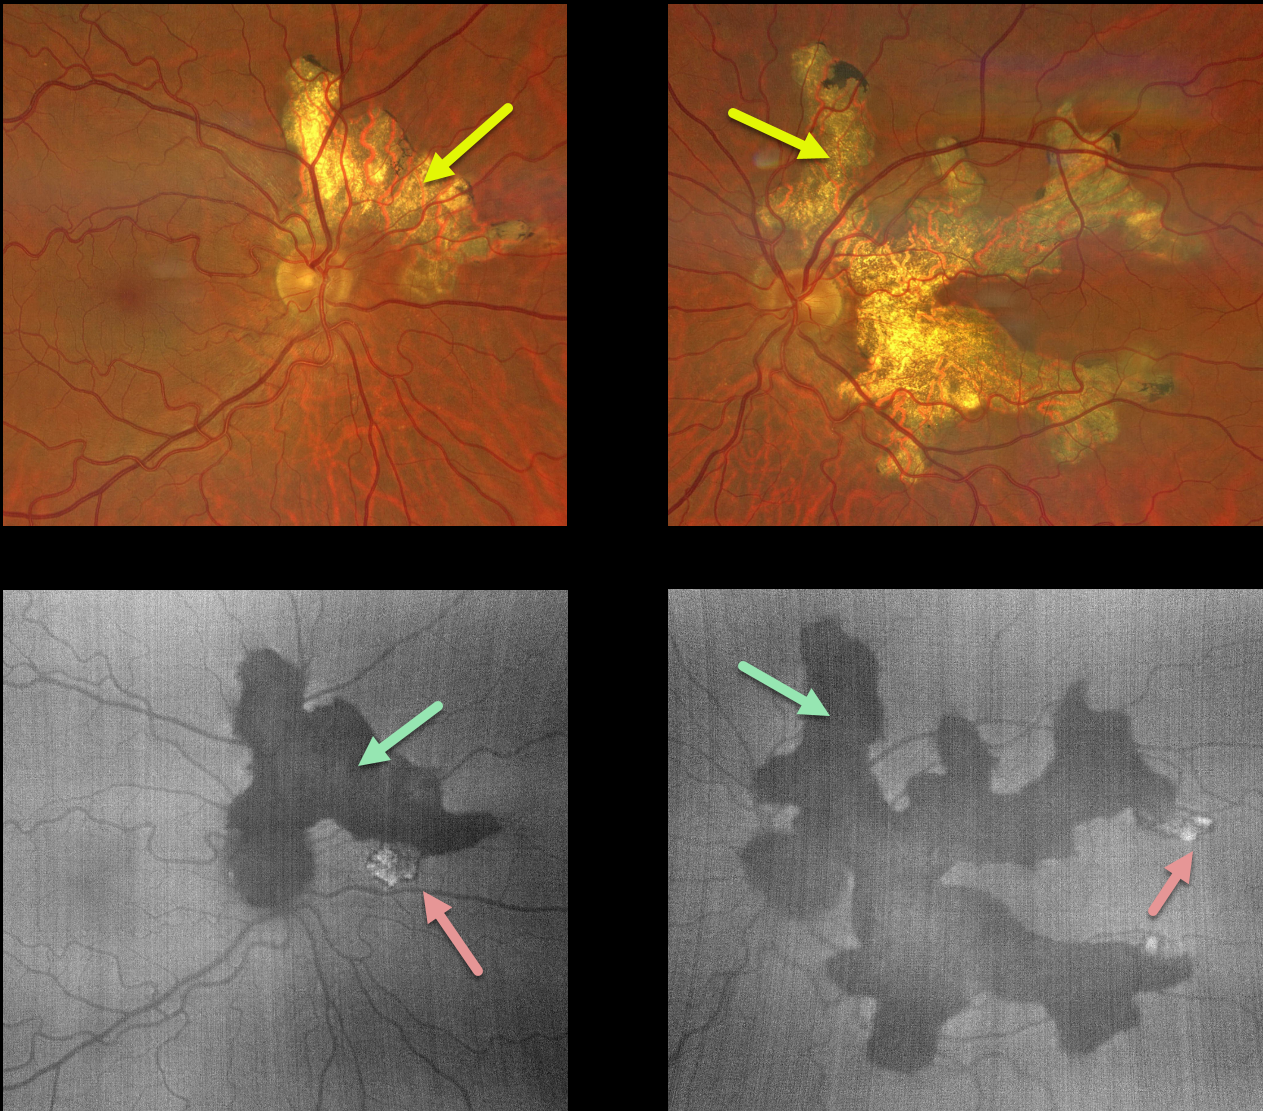
This healthy 54YO male presented for a second opinion for untreated serpiginous chorioretinitis that was diagnosed 2 years earlier. Vision was 20/20 OD and 20/200 OS.
Color imaging shows bilateral chorioretinal scarring that extends outwards from the optic nerves. This scarring is more extensive OS and spares the macular center. On fundus autofluorescence (FAF), this scarring is diffusely hypo-FAF except for a few margins bilaterally that are hyper-FAF.
Learning Points:
Serpiginous choroiditis is an idiopathic, usually bilateral chorioretinal inflammatory condition most commonly found in middle-aged men (Khanamiri and Rao, Surv Ophthalmology 2013;58:203-232). Recurrent areas of inflammation develop along the edge of a previous scar, producing scarring that meanders from the optic nerve outward into the macula.
Vision is good unless scarring or macular neovascularization extends through the macular center. There is no consensus on the optimal systemic treatment, including corticosteroids and systemic steroid-sparing agents.
Tubercular serpiginous-like choroiditis mimics serpiginous, but affects younger patients with more multifocal and peripheral recurrences and progression if untreated (Agarwal et al, AJO 2020;220:160-169).
We felt the hyper-FAF lesions in our patient possibly indicated active disease, so prednisone 40mg PO for 10 days was prescribed. Tuberculosis workup was negative.
SERPIGINOUS CHOROIDITIS
Originally posted on @retina.rocks November 19, 2021
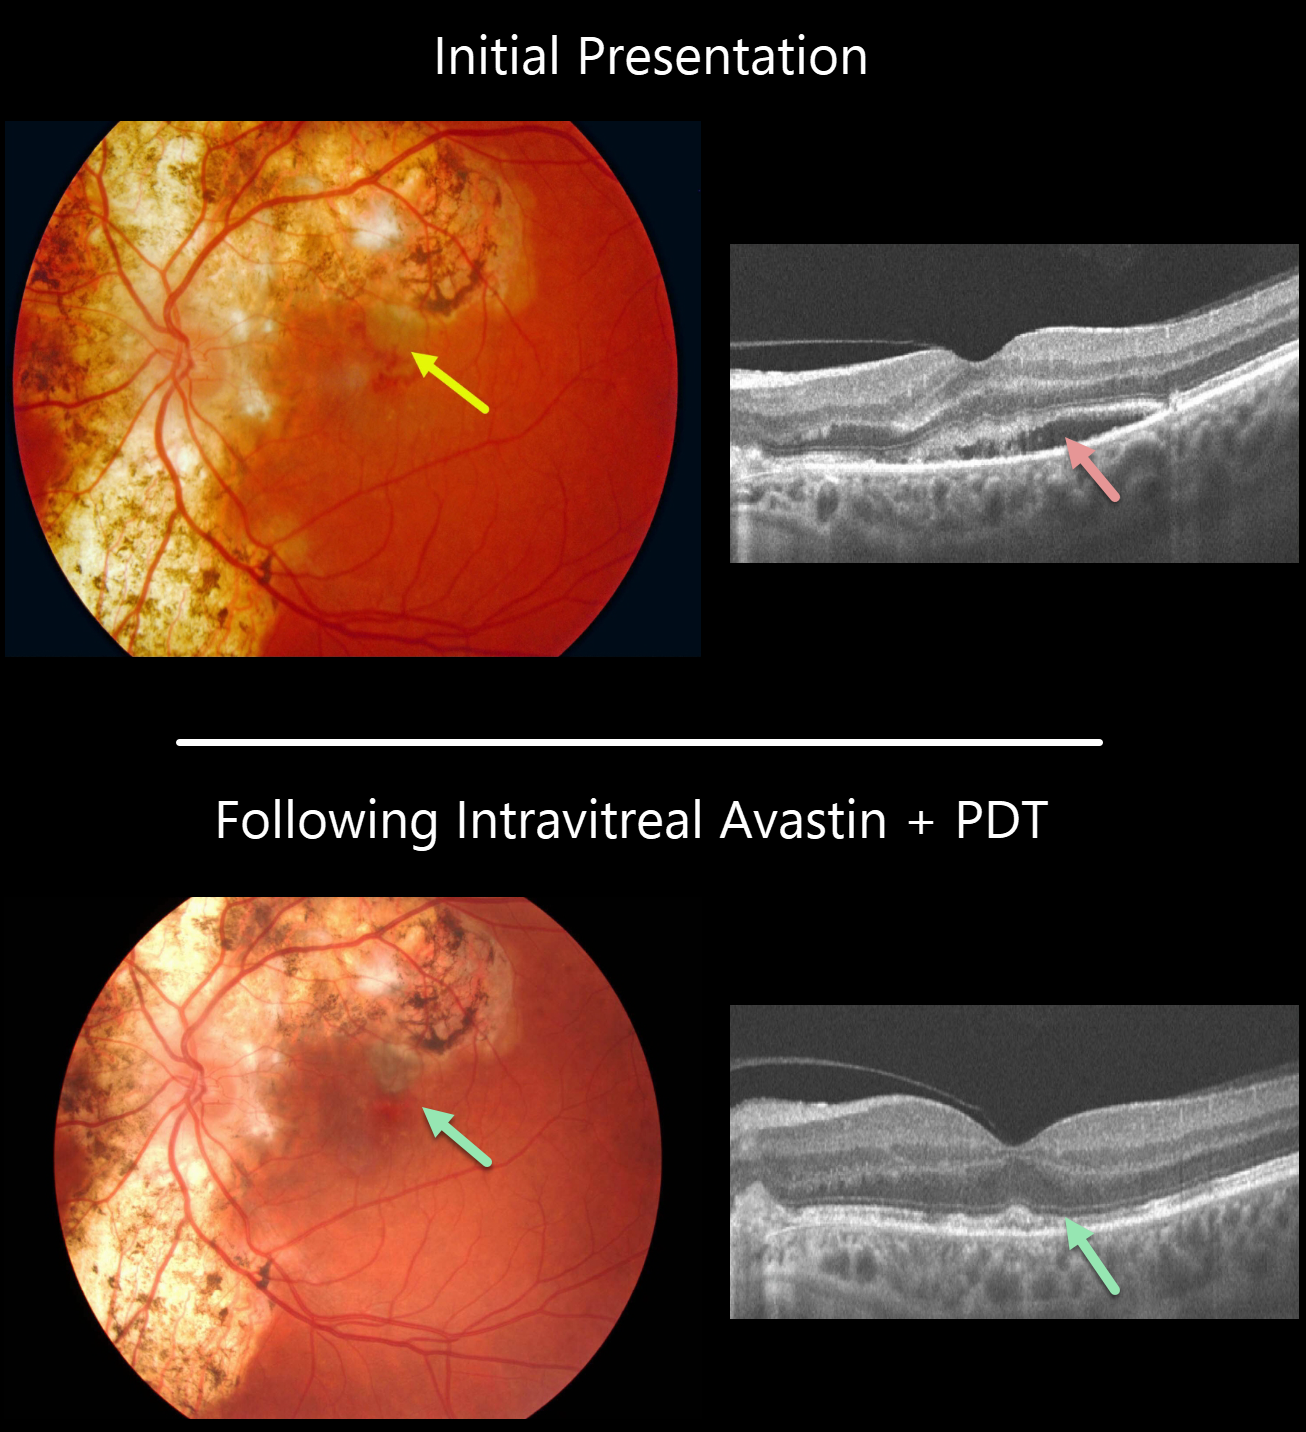
This patient presented with bilateral serpiginous chorioretinopathy scarring (only the left eye pictured). A pigmented macular neovascularization (MNV) with associated subretinal pigment and blood was noted in the superior left fovea. Subretinal fluid is noted on OCT scanning. The MNV was treated with a combination of photodynamic therapy and intravitreal Avaston.
Vision improved from a preoperative 20/400 to 20/30 with resolution of all fluid and blood. The patient continues to need PRN anti-VEGF injections in his left eye.
Learning Points:
Serpiginous choroiditis is an idiopathic, usually bilateral chorioretinal inflammatory condition most commonly found in middle-aged men.
Recurrent areas of inflammation develop along the edge of a previous scar, producing scarring that meanders from the optic nerve outward into the macula.
Vision is good unless scarring (as in this patient) or macular neovascularization extends through the macular center.
SERPIGINOUS CHORIORETINITIS
Originally posted on @retina.rocks March 16, 2021
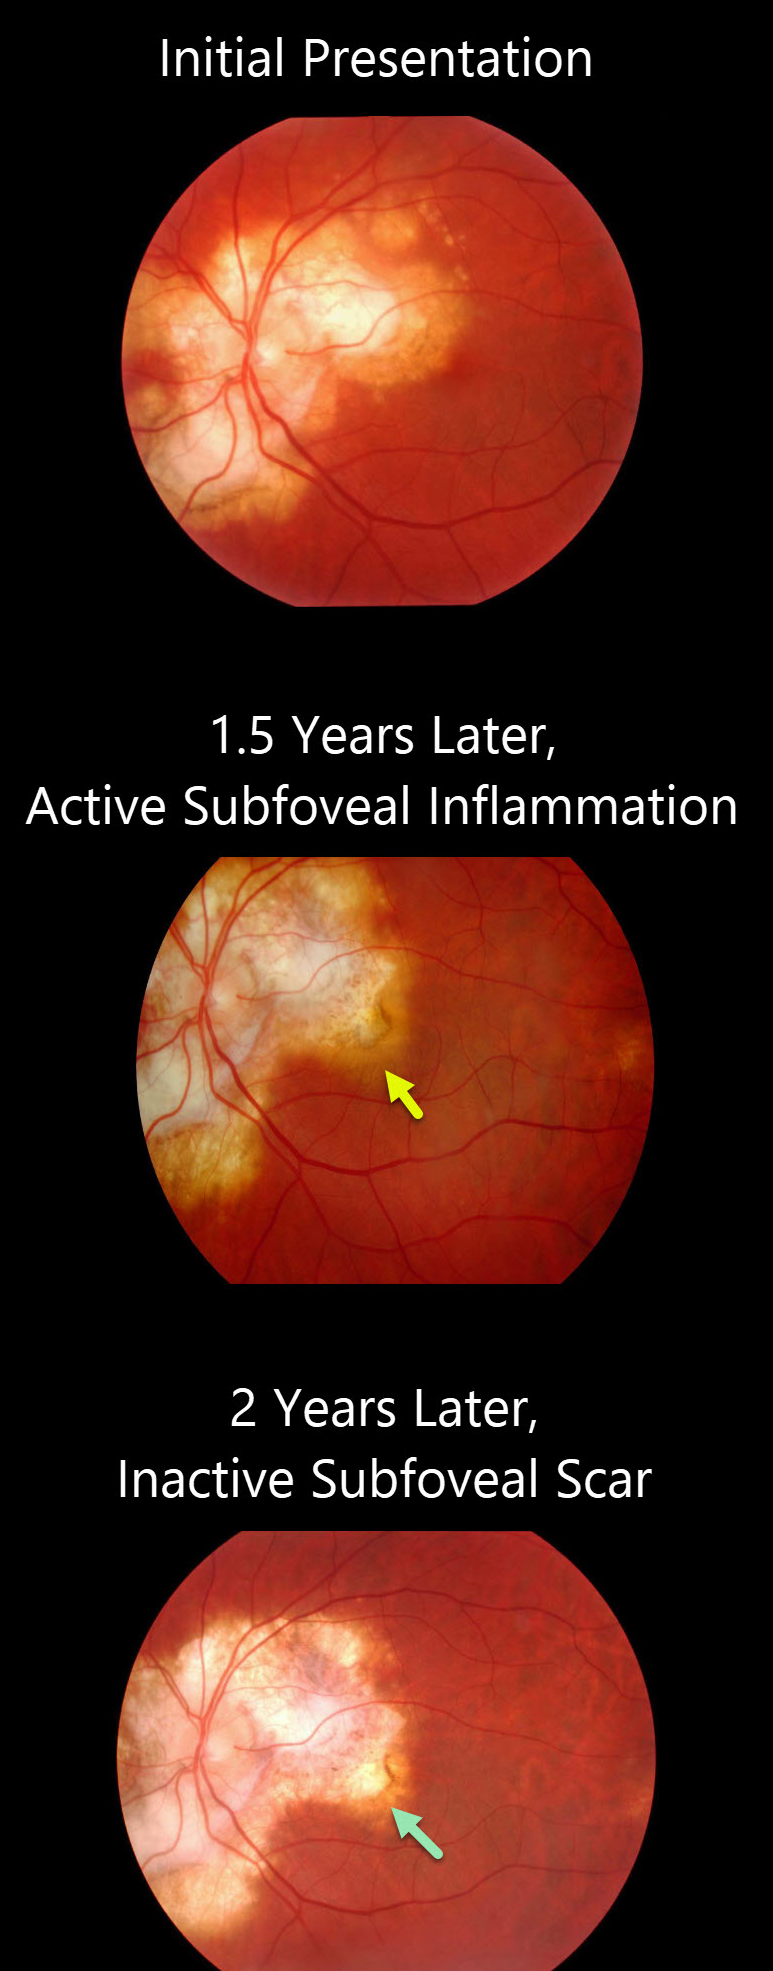
This patient was seen initially with inactive peripapillary and macular chorioretinal scarring from serpiginous choroiditis.
A year and a half later, he presented with new subfoveal active inflammation. One year later, there was inactive atrophic subfoveal scarring.
Learning Points:
Serpiginous choroiditis is an idiopathic, usually bilateral chorioretinal inflammatory condition most commonly found in middle-aged men.
Recurrent areas of inflammation develop along the edge of a previous scar, producing scarring that meanders from the optic nerve outward into the macula.
Vision is good unless scarring (as in this patient) or macular neovascularization extends through the macular center.
SERPIGINOUS CHORIORETINITIS
Originally posted on @retina.rocks January 22, 2020
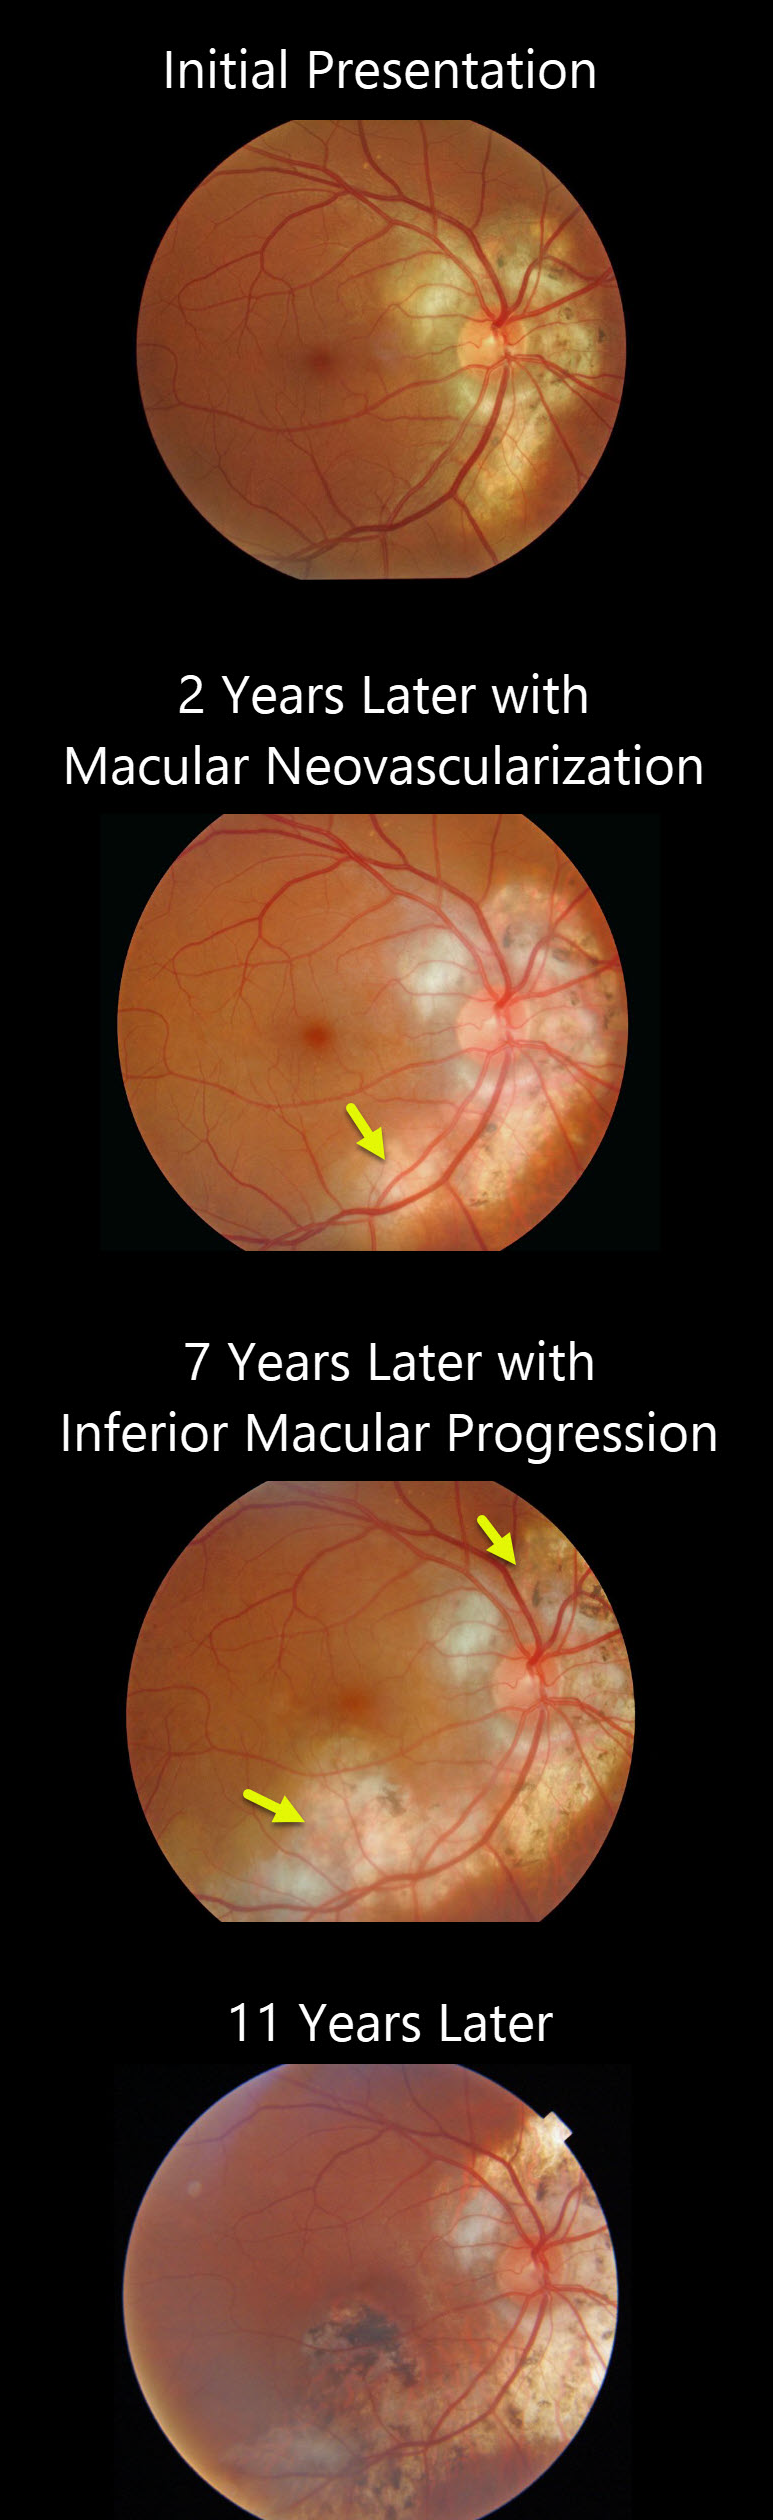
This patient with serpiginous choroiditis shows typical progression of the inflammatory and neovascular process over an 11-year period. Ongoing intravitreal Avastin and Ozurdex injections so far have kept him with good central vision.
Learning Points:
Serpiginous choroiditis is an idiopathic, usually bilateral chorioretinal inflammatory condition most commonly found in middle-aged men.
Recurrent areas of inflammation develop along the edge of a previous scar, producing scarring that meanders from the optic nerve outward into the macula.
Vision is good unless scarring or macular neovascularization extends through the macular center.


