

Tamoxifen Retinopathy
<< Back to Cases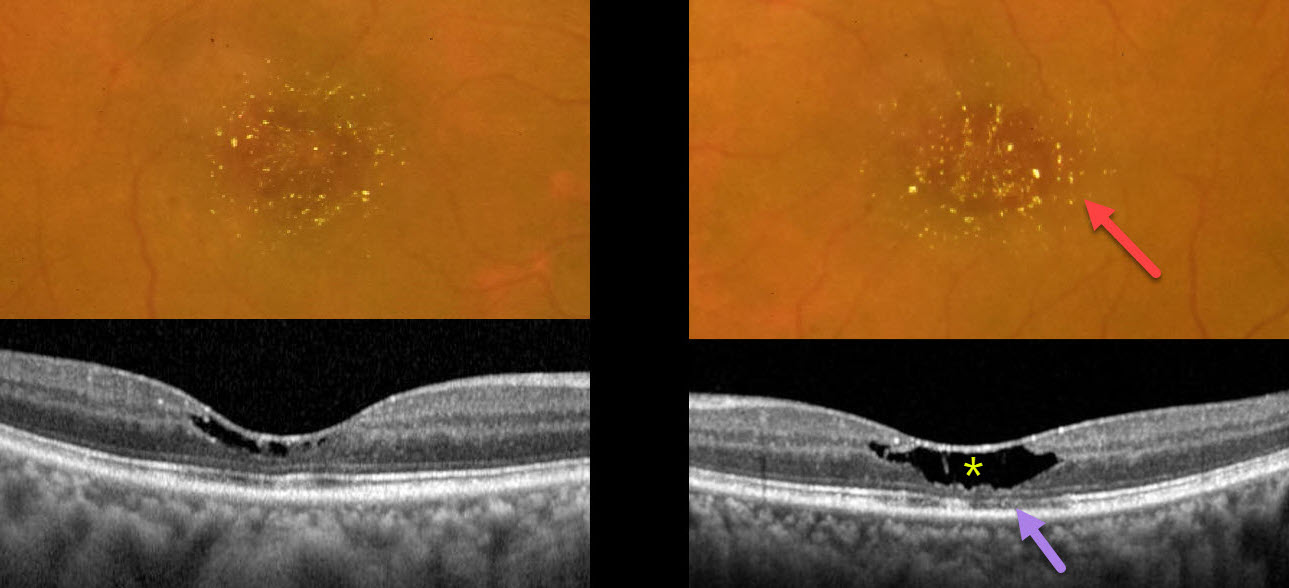
TAMOXIFEN RETINOPATHY
Mauli Shah and Alay Banker
Originally posted on @retina.rocks March 4, 2025
This 51YO female presented with 3 months of bilateral vision loss. She was diagnosed 5 years earlier with breast cancer, followed by a radical mastectomy. Since then, she has been treated with tamoxifen 20mg PO daily. Vision was 20/60 OD and 20/40 OS.
Color photography shows bilateral, symmetric, central macular yellowish crystalline deposits, corresponding to tiny hyperreflective inner retinal lesions on OCT. Central inner retinal cavitations, outer nuclear layer loss, and disruption of the ellipsoid zone and outer segment bands are noted, particularly in the left eye.
Learning Points:
The prevalence of tamoxifen retinopathy for patients taking tamoxifen 20mg daily may be as high as 12% (Kim et al, Ophthalmology 2020;127:555-557). Although most oncologists do not require this, it is not unreasonable to perform ophthalmic screening examinations with OCT following 2 years of therapy (Tenney et al, Surv Ophthalmology 2023;69:42-50).
Tamoxifen inhibits the glutamate-aspartate transporter, leading to excessive intracellular accumulation of glutamate in Müller cells, which are vital in maintaining retinal cell integrity and homeostasis. Tamoxifen retinopathy shows findings very similar to macular telangiectasia type 2 (MacTel 2; Lee et al., Ophthalmology Retina 2020;3:681-689), including retinal cavitations, right-angle venules, and inner retinal crystals. Both disorders likely share Muller cell injury as a common etiology. The changes in MacTel2 are usually in the temporal fovea, whereas they seem to be more diffusely distributed throughout the central macula with tamoxifen (Hess et al, Retina 2023;7:101-110).
Ocular toxicity is more common with a cumulative dose over 100 grams, although our patient still developed classic toxicity despite a cumulative dose of only 35.2 grams. The tamoxifen was discontinued after discussion with the treating oncologist. Three months later, the vision and retinal findings were unchanged (not shown).
TAMOXIFEN RETINOPATHY
Aaron McNulty
Originally posted on @retina.rocks June 19, 2023
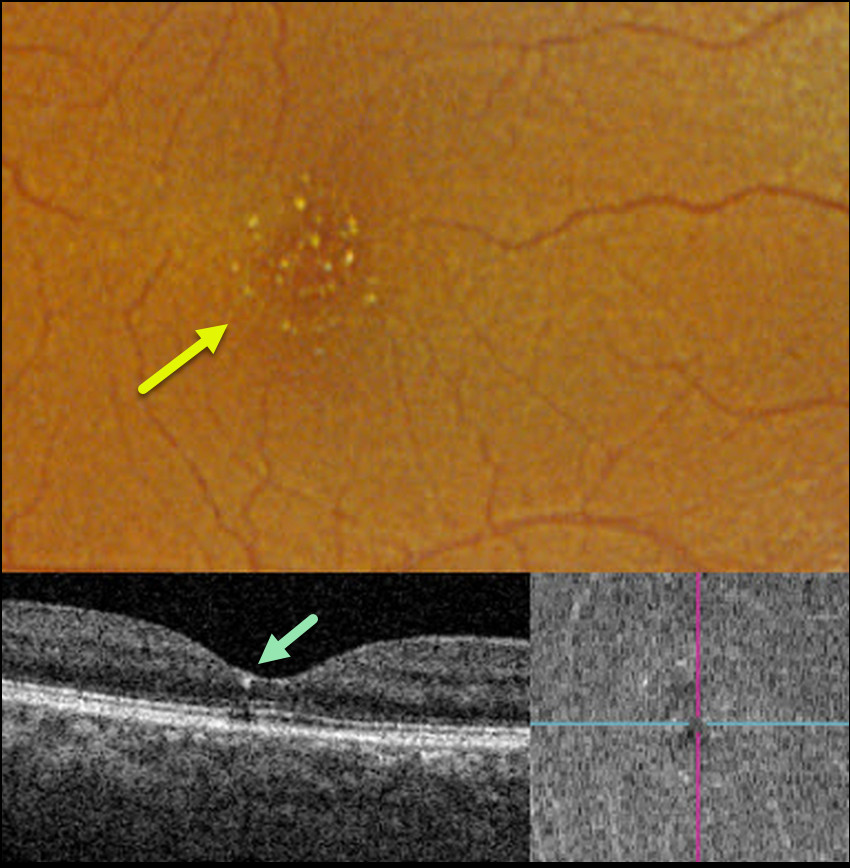
This 56YO female was referred for asymptomatic macular findings. The referring doctor mentioned that she may have retinal changes from the Tamoxifen that she was taking for over 3 years for breast cancer. Vision was 20/50 OD and 20/40 OS.
Optos color RGB imaging shows numerous tiny inner retinal crystalline deposits scattered throughout each fovea. These deposits appeared as tiny hyperreflective dots beneath the ILM on OCT B-scan and en face.
Our patient had already spoken with her oncologist before seeing us and had already stopped the Tamoxifen. The crystalline changes will likely remain and, hopefully, not progress going forward.
Learning Points:
Tamoxifen retinopathy shares phenotypes very similar to those of macular telangiectasia type 2 (MacTel 2, Lee et al., Ophthalmology Retina 2020;3:681-689), especially in the early stages, including retinal cavitations, right-angle venules, and inner retinal crystals.
The changes in Tamoxifen are confined to the central macula, whereas in MacTel2 they are present in a slightly larger area with an epicenter temporal to the foveal center (Hess et al, Ophthalmology Retina 2023;7:101-110). The retinal changes for both disorders likely share Muller cell dysfunction as the common cause.
TAMOXIFEN RETINOPATHY
Originally posted on @retina.rocks September 9, 2020
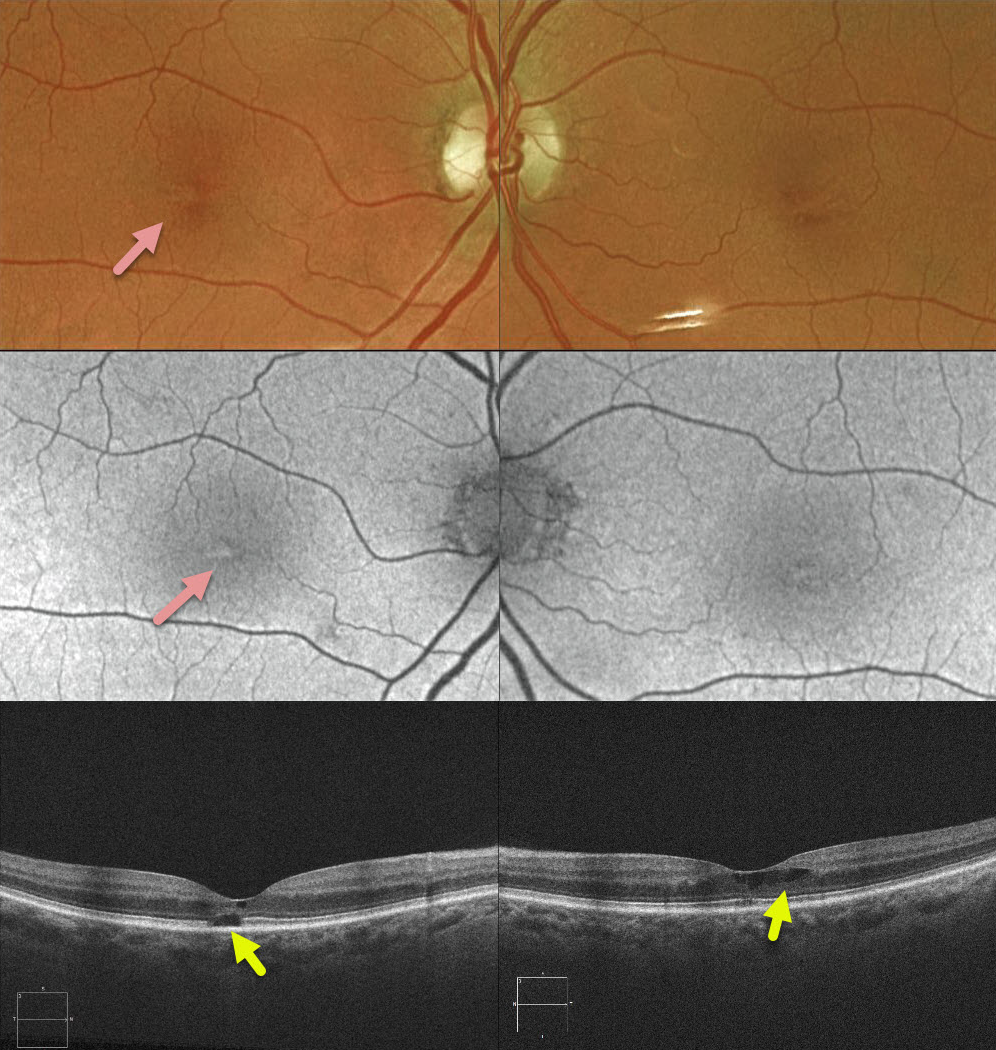
This 72YO female recently completed a 5-year course of Tamoxifen as adjunctive treatment for breast cancer. She had no visual symptoms with 20/30 vision bilaterally.
Clinically, there were subtle bilateral foveal pigmentary changes. B-scan and en-face OCT showed bilateral cavitary changes.
Learning Points:
Tamoxifen retinopathy shares findings very similar to those of macular telangiectasia type 2 (MacTel2), including retinal cavitations, right-angle venules, and inner retinal crystals. The changes in MacTel2 are usually confined to the temporal fovea, whereas with Tamoxifen, they seem more diffusely distributed throughout the entire central macula. The retinal changes for both disorders likely share Muller cell injury as the underlying cause.
The prevalence of Tamoxifen retinopathy may be as high as 12%. Although most oncologists do not require this, periodic ophthalmic screening, OCT, and examinations may be indicated since patients can lose central vision if toxicity develops.


