

Uveal Malignant Melanoma (MM)
<< Back to Cases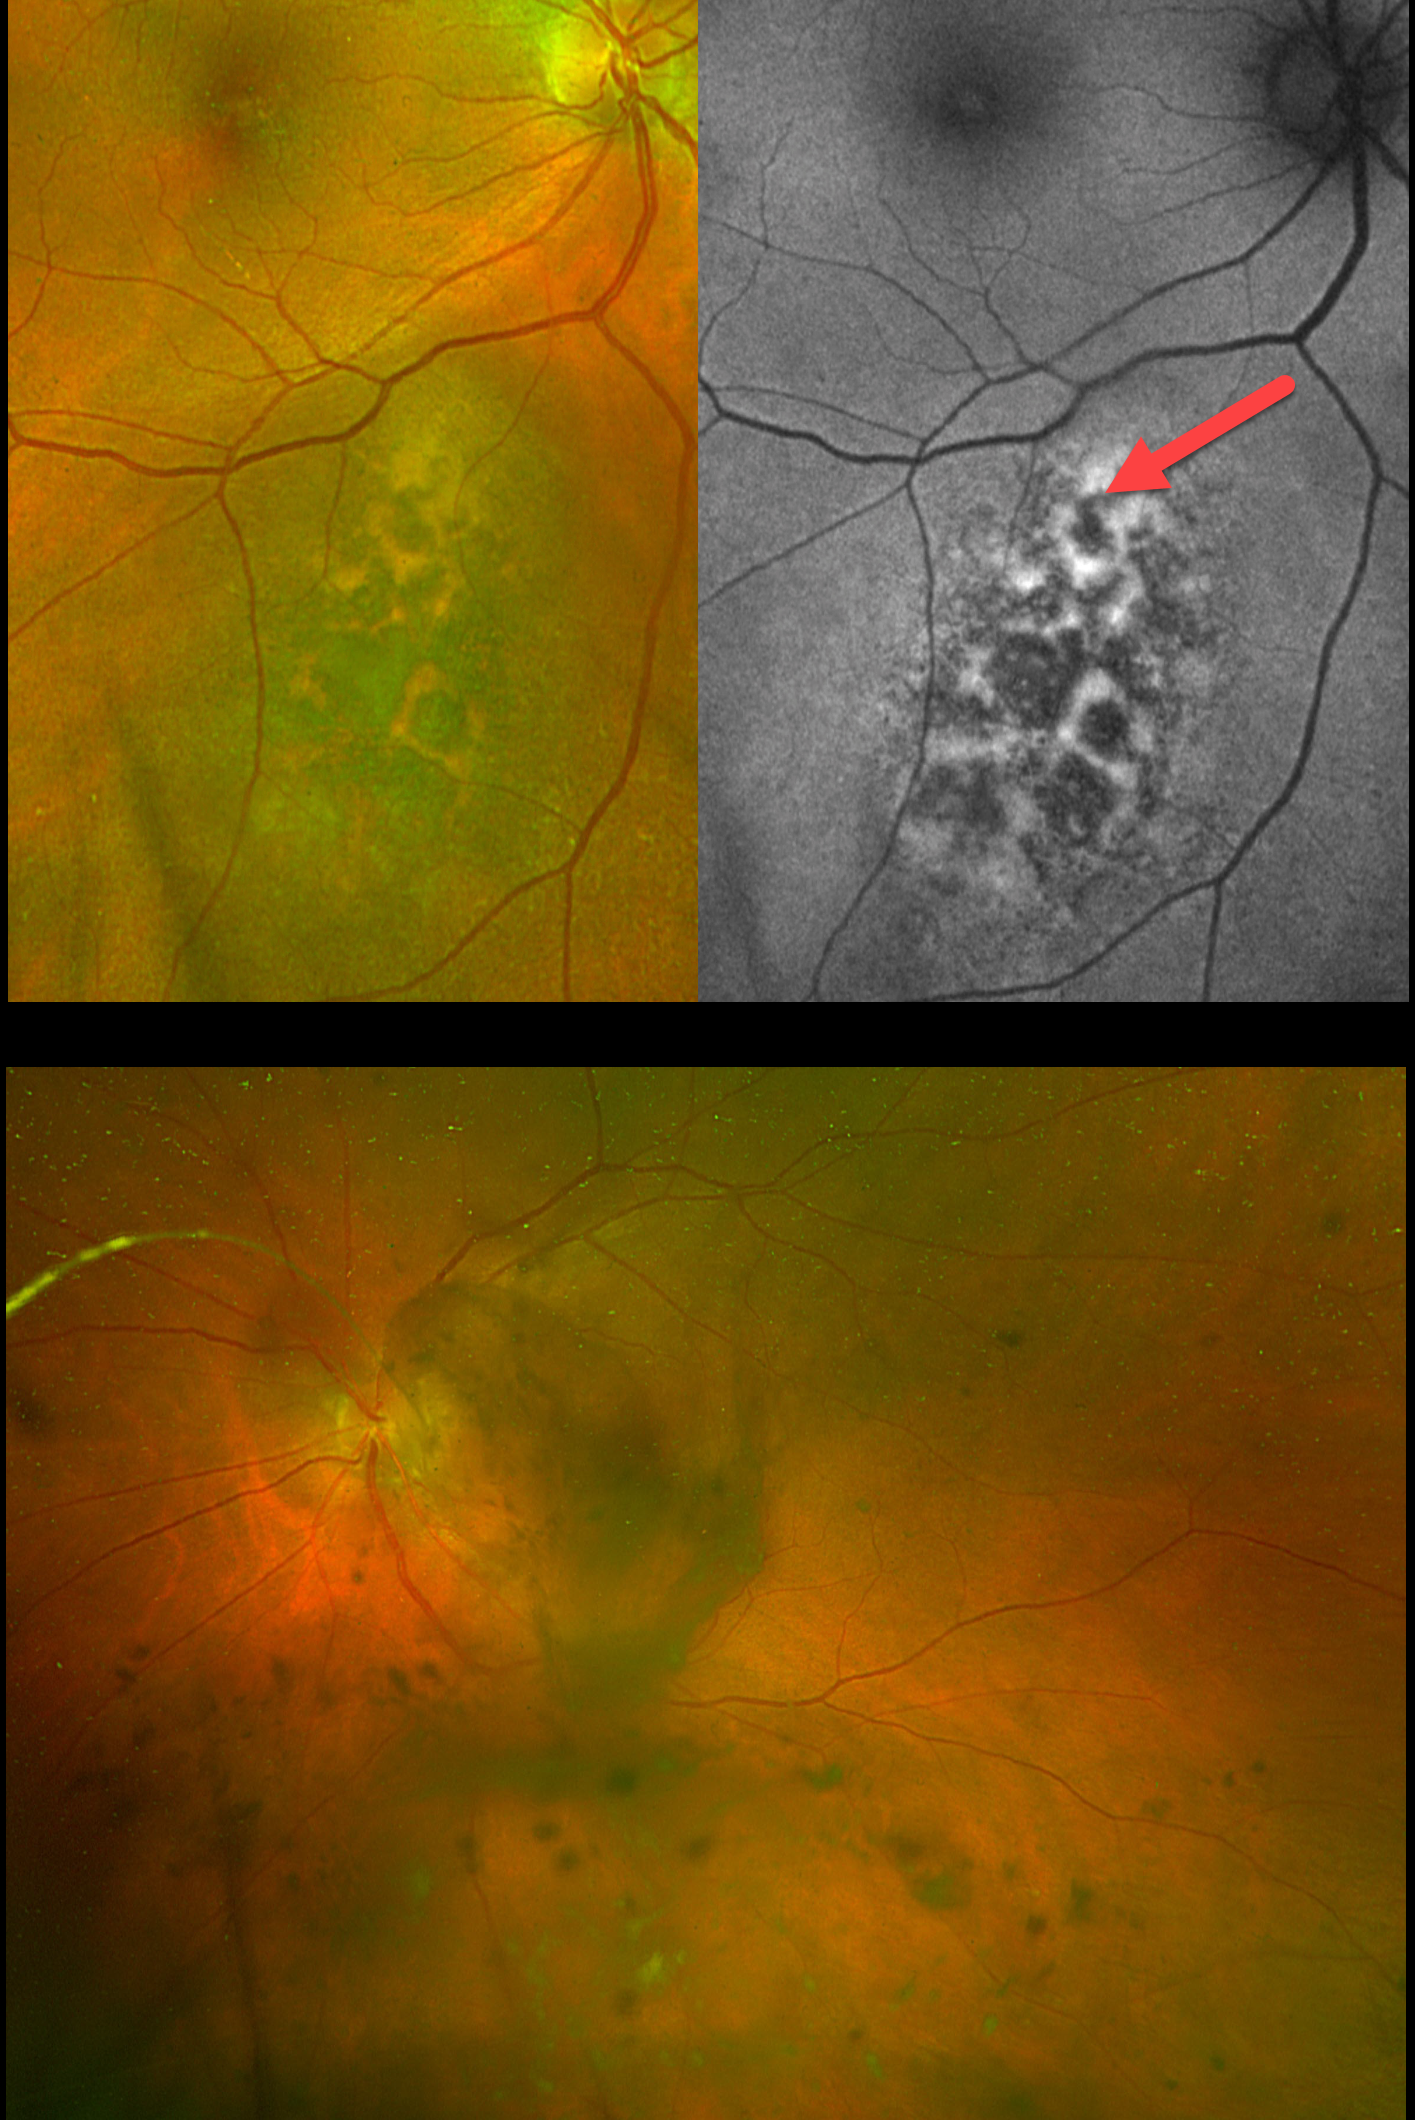
METASTATIC MELANOMA OF UNKNOWN ORIGIN, SUSPECT CHOROIDAL NEVUS OD AND PROBABLE MELANOMA OS
Mattie Adams
Originally posted on @retina.rocks January 19, 2026
This 67YO female presented with a 3-week history of floaters in her left eye. She has a known history of metastatic melanoma of unknown origin, including numerous brain lesions. There was no family history of ocular or cutaneous melanoma. Vision was 20/20 OD and 20/40 OS.
Optos color RG imaging OD shows a suspect choroidal nevus just inferonasal to the macula. There is overlying orange lipofuscin pigment, which is hyperautofluorescent. Optos imaging OS shows extensive pigmented vitreous debris variably obscuring the posterior pole.
Learning Points:
Uveal malignant melanoma (MM) and cutaneous melanoma are rarely associated with each other. The exception is the presence of a mutated tumor suppressor gene, BRCA1-associated protein 1 (BAP1), which is associated with autosomal-dominant uveal MM and other primary cancers, including cutaneous melanoma.
Our patient did not have a primary for her metastatic disease. The presence of a suspect nevus in her right eye and possible metastatic melanoma to her left eye argues for a pathogenic BAP1 mutation. We discussed this possibility with her oncologist, who felt this was highly unlikely given the negative family history. Given her relatively good vision and poor systemic prognosis, observation was recommended as the initial management for her ocular findings. Unfortunately, she died 3 months later.
PSEUDO-UVEAL MELANOMA FROM CHOROIDAL DETACHMENT
Originally posted on @retina.rocks December 25, 2025
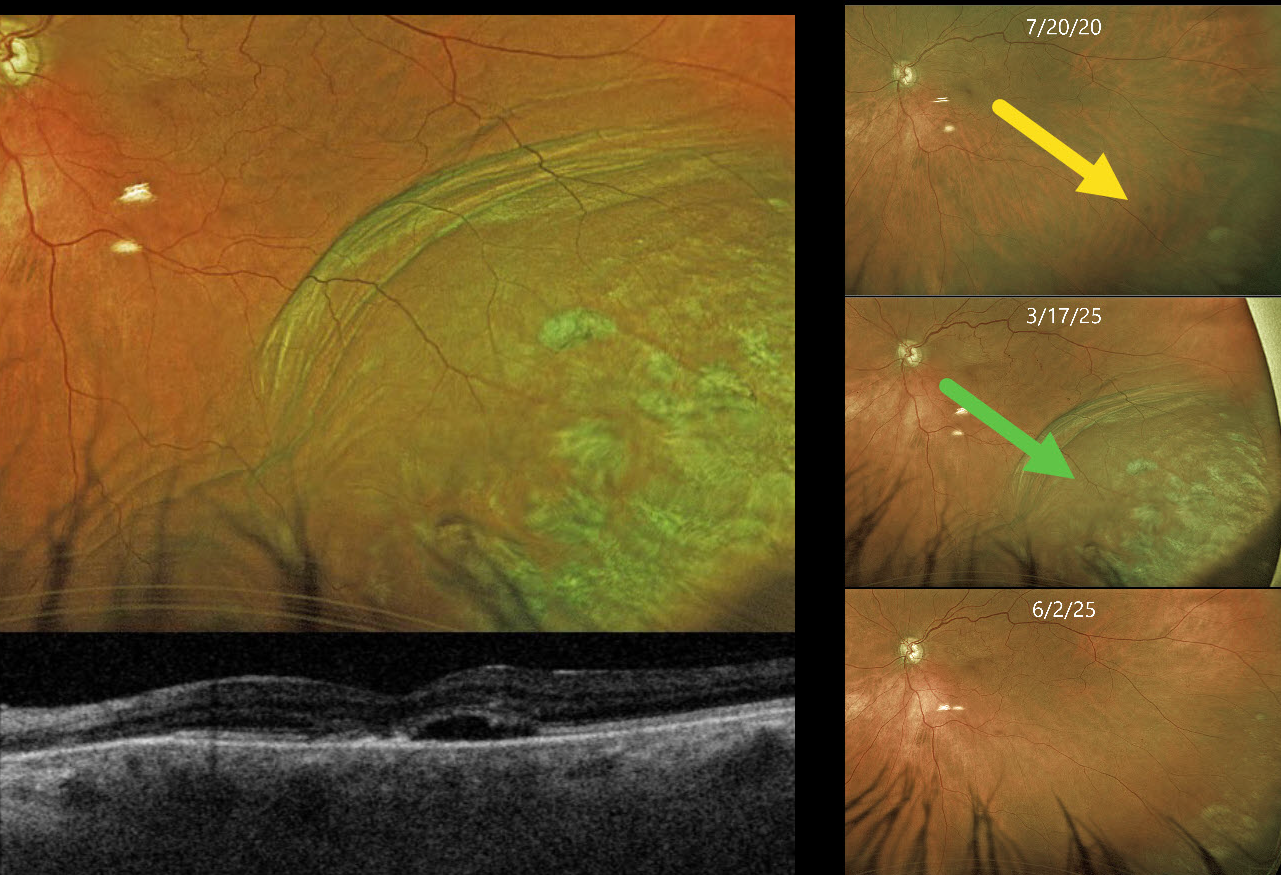
This 85YO female presented with an elevated pigmented choroidal mass in her inferotemporal periphery, which extended into her distal macula (Optos color RG). This mass was absent 5 years earlier. Circumferential choroidal folds extend along the posterior edge of the lesion. Triton swept-source OCT shows a blister of subretinal fluid and a thickened choroid.
She has a history of uncontrolled glaucoma and underwent a XEN Gel Stent procedure 8 days earlier. Intraocular pressure (IOP) was 8 mmHg.
Learning Points:
A choroidal detachment is defined by the abnormal presence of fluid or blood in the suprachoroidal space. Serous choroidal detachments, also known as choroidal effusions, are a frequent complication of glaucoma surgery. Several causative mechanisms are believed to be at play: hypotony allows fluid to accumulate in the suprachoroidal space, and inflammation increases the choroidal permeability. The detached ciliary body may also produce less aqueous, thus creating a self-perpetuating cycle. Often, observation is sufficient, but topical steroids and cycloplegics can be helpful in promoting resolution.
Other than the obvious appearance of this lesion immediately following glaucoma surgery, clues to this not being a uveal MM include the choroidal folds along the posterior extent of the choroidal detachment and an OCT consistent with hypotony maculopathy. About 10 weeks later, the IOP was 9 mmHg, and the choroidal effusion had completely resolved.
UVEAL MELANOMA
by Ayushi Gupta and Vishal Agrawal
Originally posted on @retina.rocks December 22, 2025
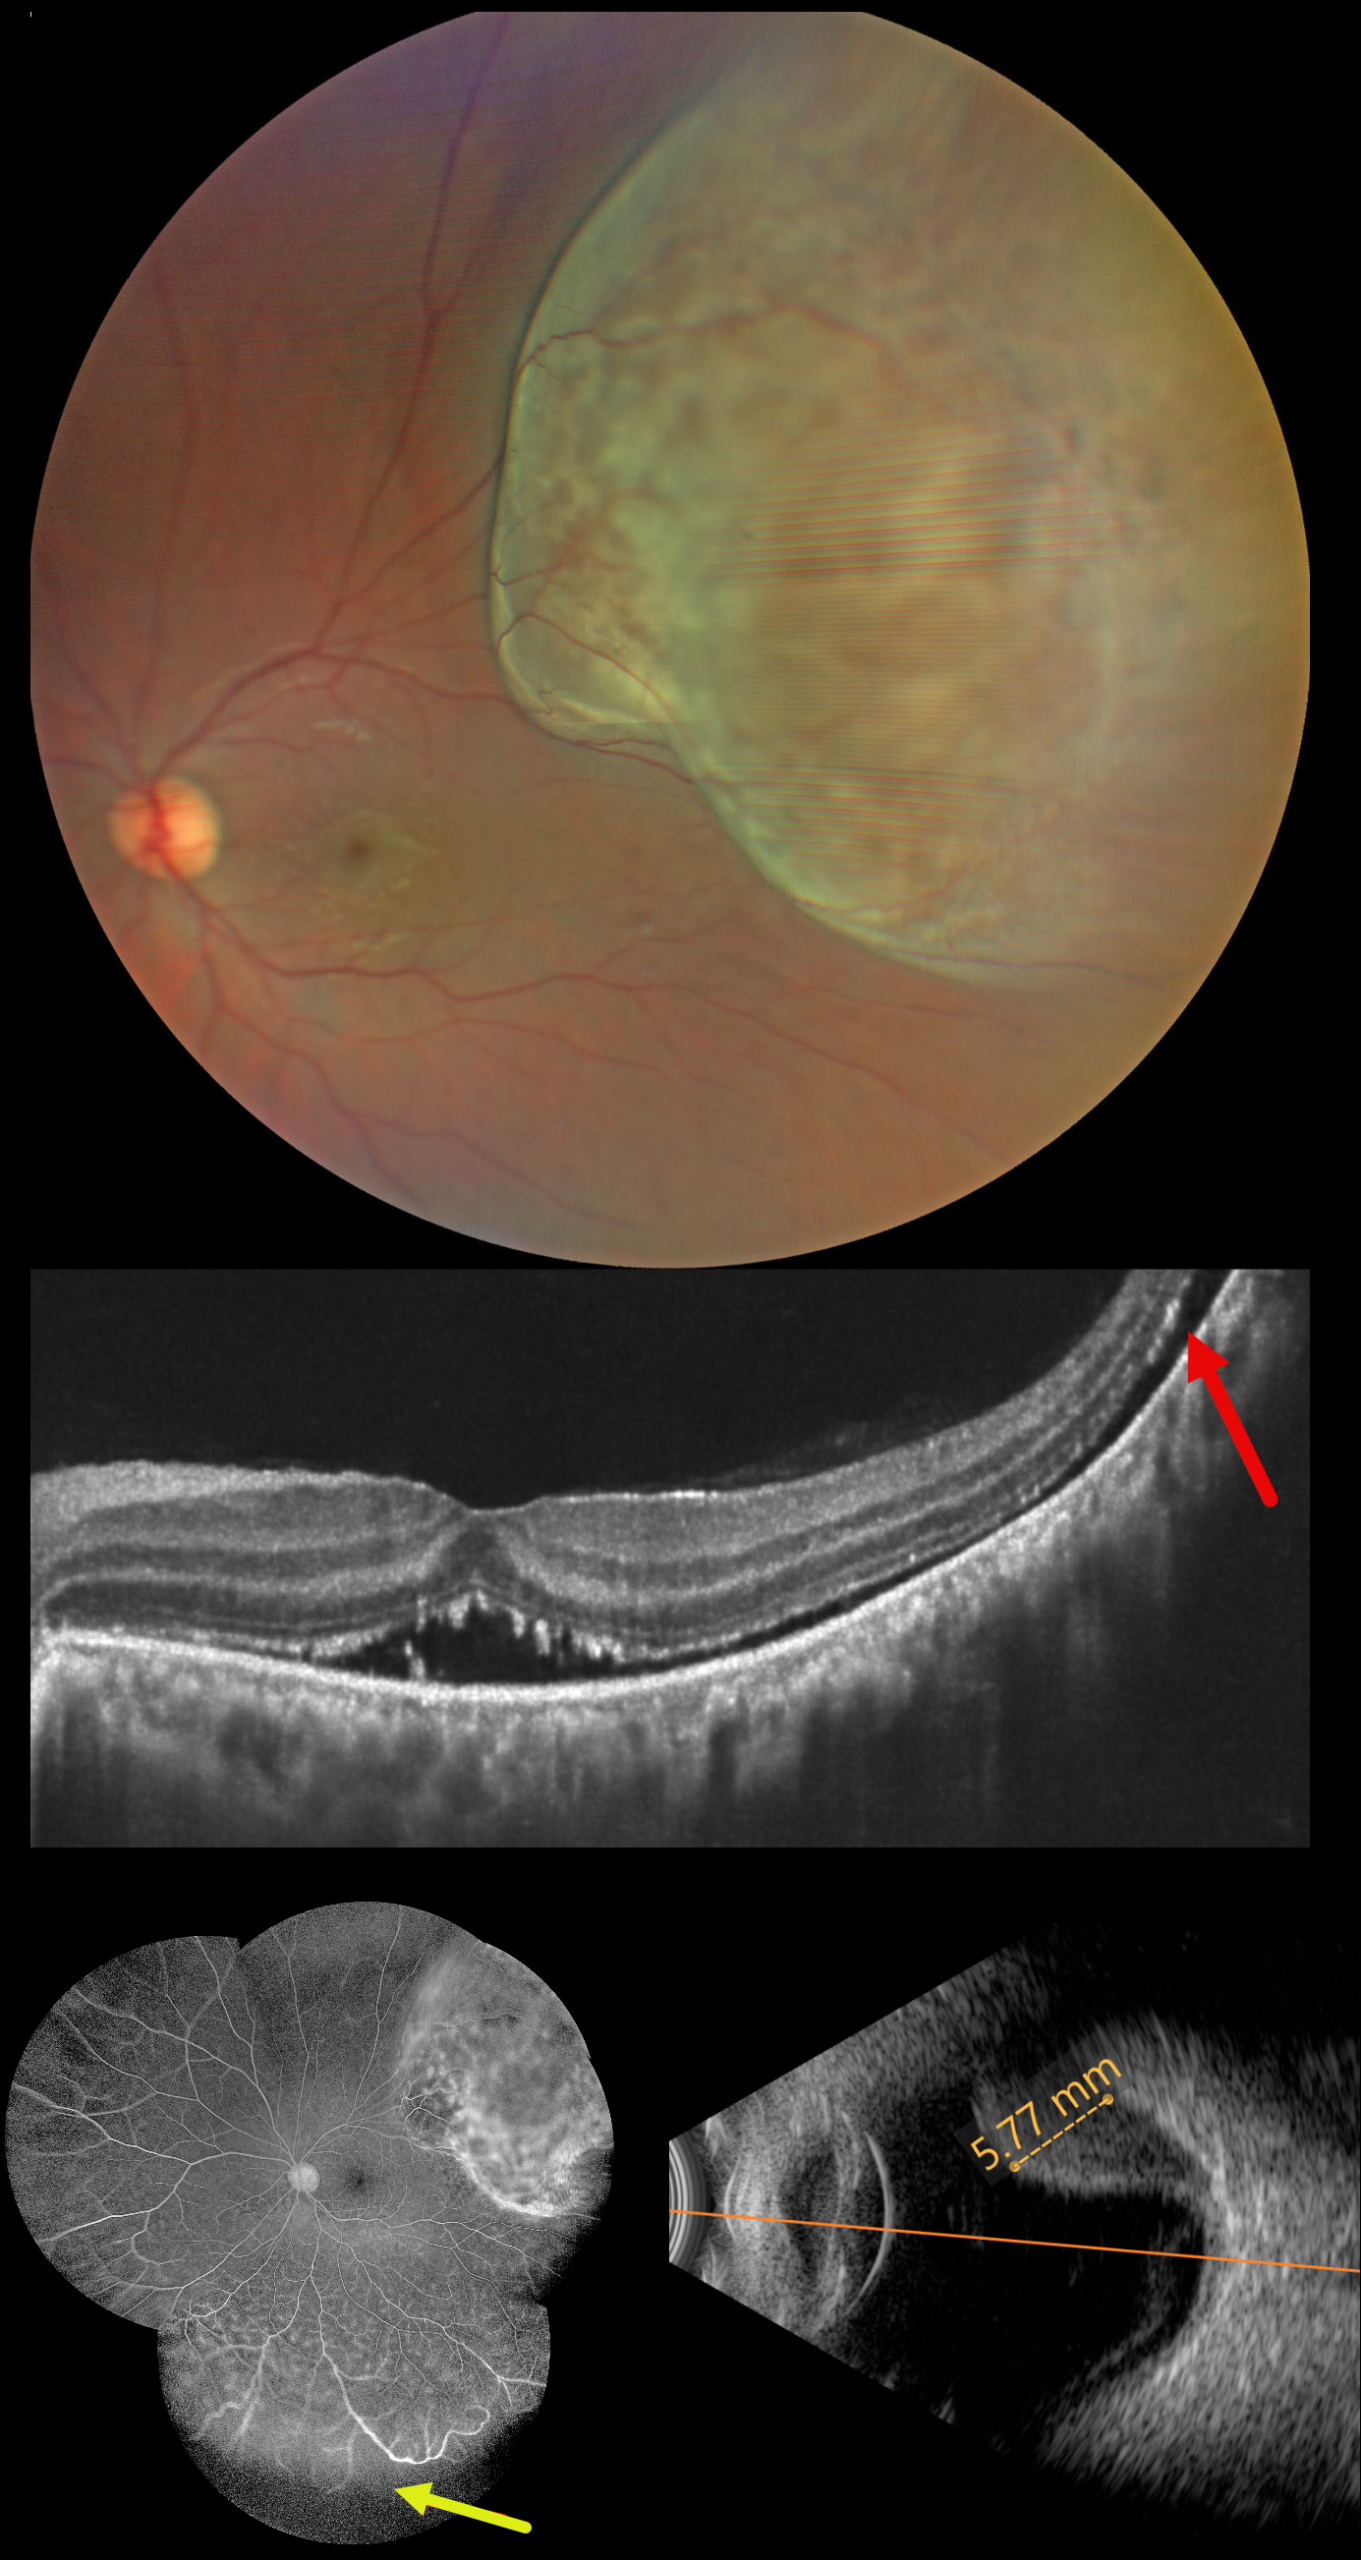
This healthy 36YO male presented with two weeks of vision loss in his left eye. Vision was 20/20 in his normal OD and 20/40 OS.
Fundus photography shows an elevated, pigmented, solid choroidal tumor, which spares the macula but occupies nearly the entire superotemporal quadrant. OCT scanning shows shallow subretinal fluid tracking from the tumor into the fovea with hyperreflective shaggy outer segments. Fluorescein angiography shows leaking intrinsic tumor vascularity with inferior peripheral retinal capillary loss. The tumor, which measures 5.77mm in axial thickness, shows moderate internal reflectivity on B-scan ultrasonography.
Learning Points:
Uveal melanoma is a malignant tumor arising from melanocytes in the uveal tract (iris, ciliary body, or choroid). The choroid is the most common site, accounting for 90% of uveal melanomas. Uveal melanoma is the most common primary intraocular cancer in adults, whereas metastatic disease is the most common intraocular malignancy. The liver is the most common metastatic site, although metastatic disease is rare on presentation. Metastases are more common in large tumors, with BAP1 mutations, and with certain tumor-related genetic markers (including positive PRAME and Class 2).
He was immediately referred to an ocular oncologist for further evaluation and treatment, including genetic testing, metastatic workup, and plaque brachytherapy. One month postoperatively, the tumor regressed to 4.6mm in thickness with decreased exudative fluid (not shown).
UVEAL MELANOMA
Malvika Singh and Manish Nagpal
Originally posted on @retina.rocks November 11, 2025
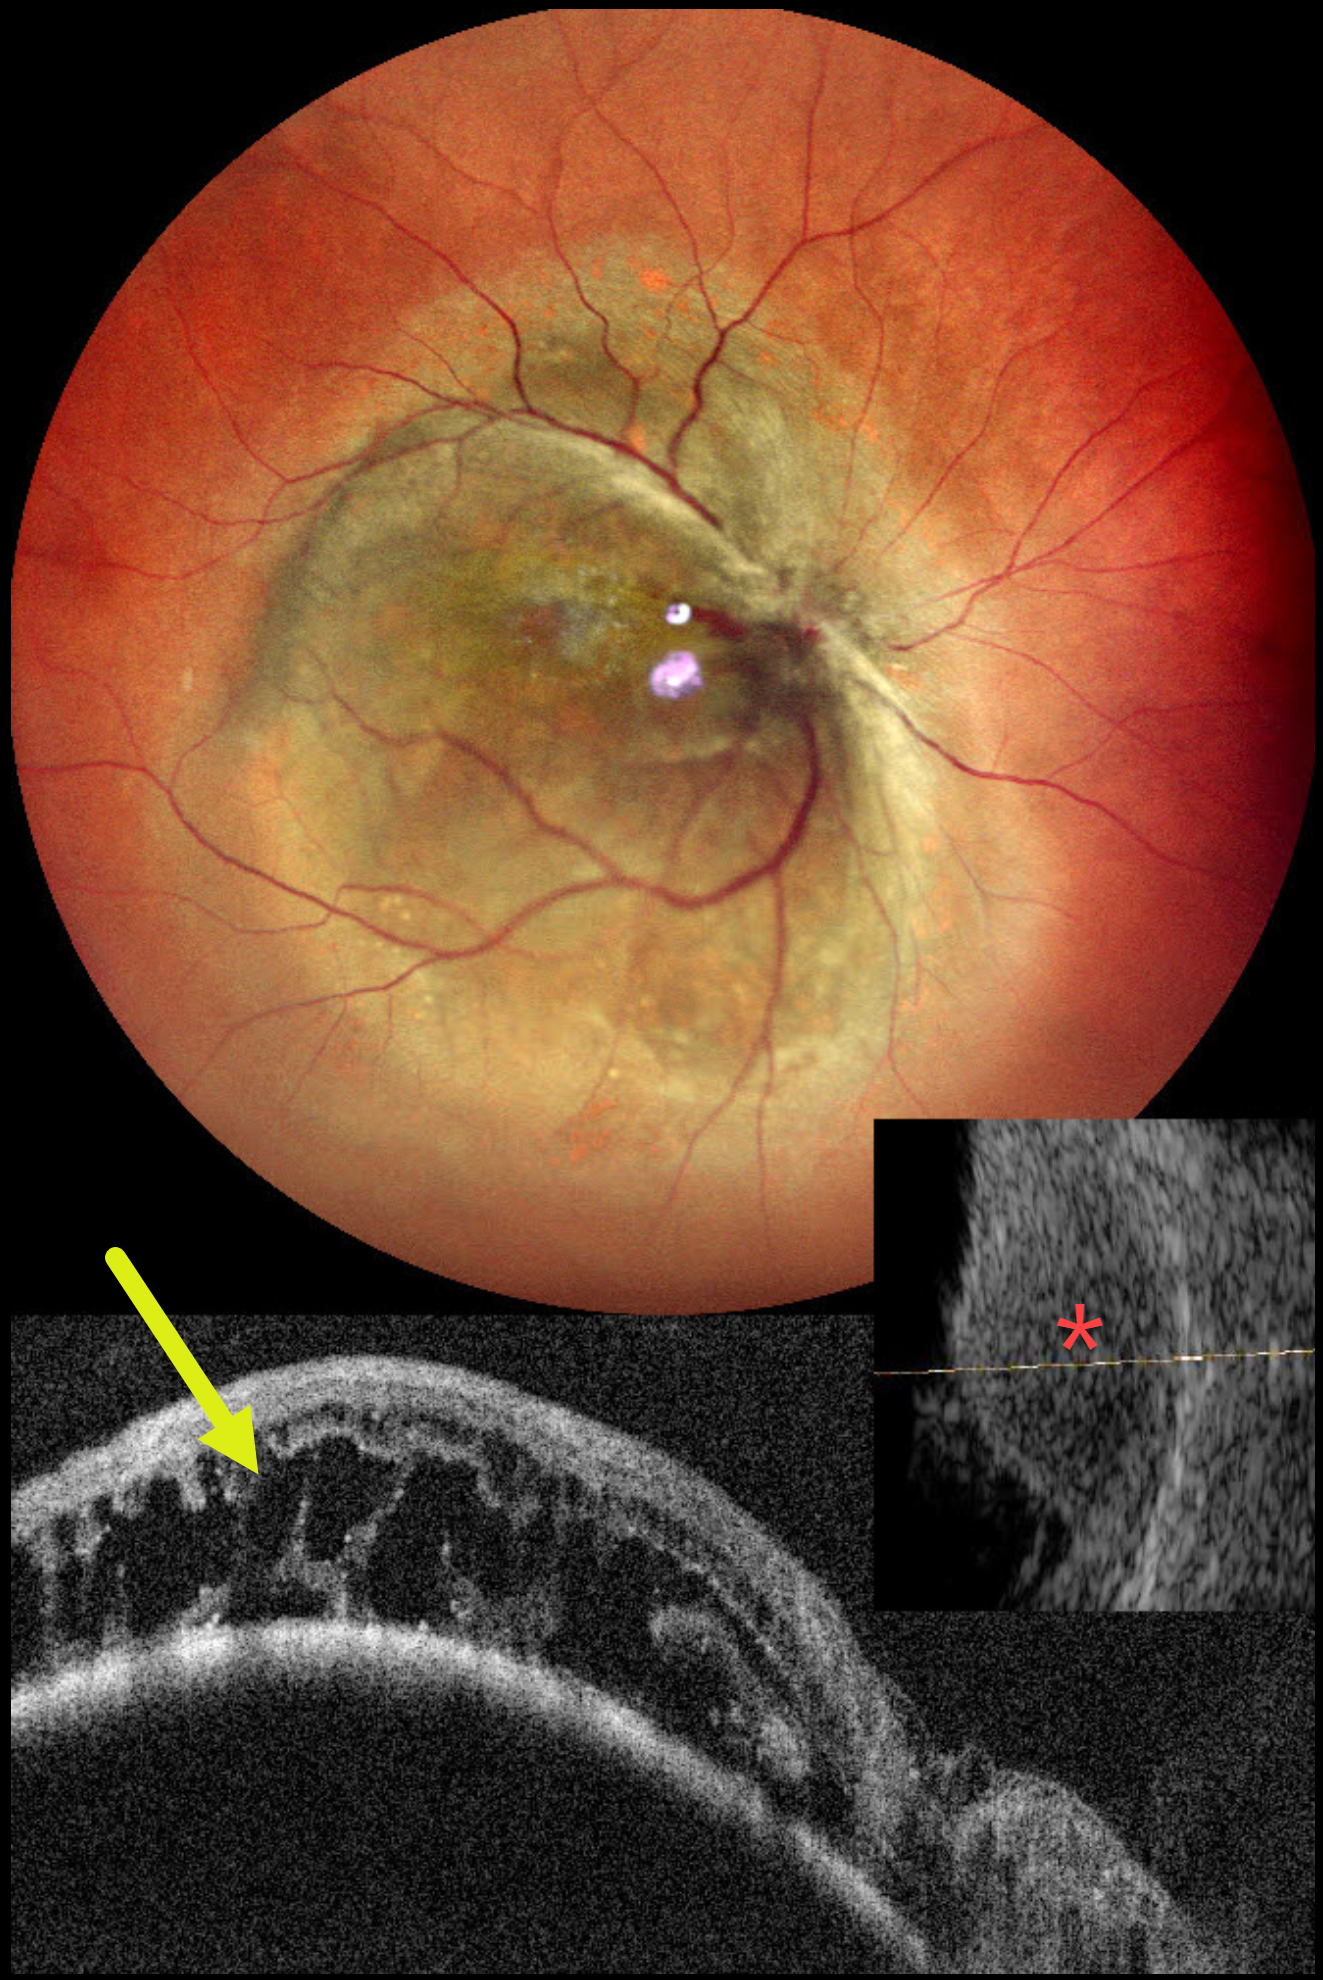
This healthy 42YO female presented with one and a half years of progressive vision in her right eye. Vision was counting fingers OD and 20/20 in her normal OS.
Pseudocolor SLO imaging shows a large, elevated pigmented choroidal lesion occupying the entire macula and extending into the midperiphery. OCT shows marked cystic outer retinal edema overlying the tumor. The lesion, which measures 6.9mm in thickness, has moderate homogenous internal reflectivity on B-scan ultrasonography. She was referred to ocular oncology for further evaluation and treatment.
Learning points:
Uveal malignant melanoma is a malignant tumor arising from melanocytes in the uveal tract (iris, ciliary body, or choroid). The choroid is the most common site, accounting for 90% of uveal melanomas. Uveal melanoma is the most common primary intraocular cancer in adults, whereas metastatic disease is the most common intraocular malignancy. The liver is the most common metastatic site, although metastatic disease is rare on presentation. Metastases are more common in large tumors, with BAP1 mutations, and with certain tumor-related genetic markers (including positive PRAME and Class 2).
UVEAL MELANOMA
Ankit Jain and Manish Nagpal
Originally posted on @retina.rocks September 3, 2025
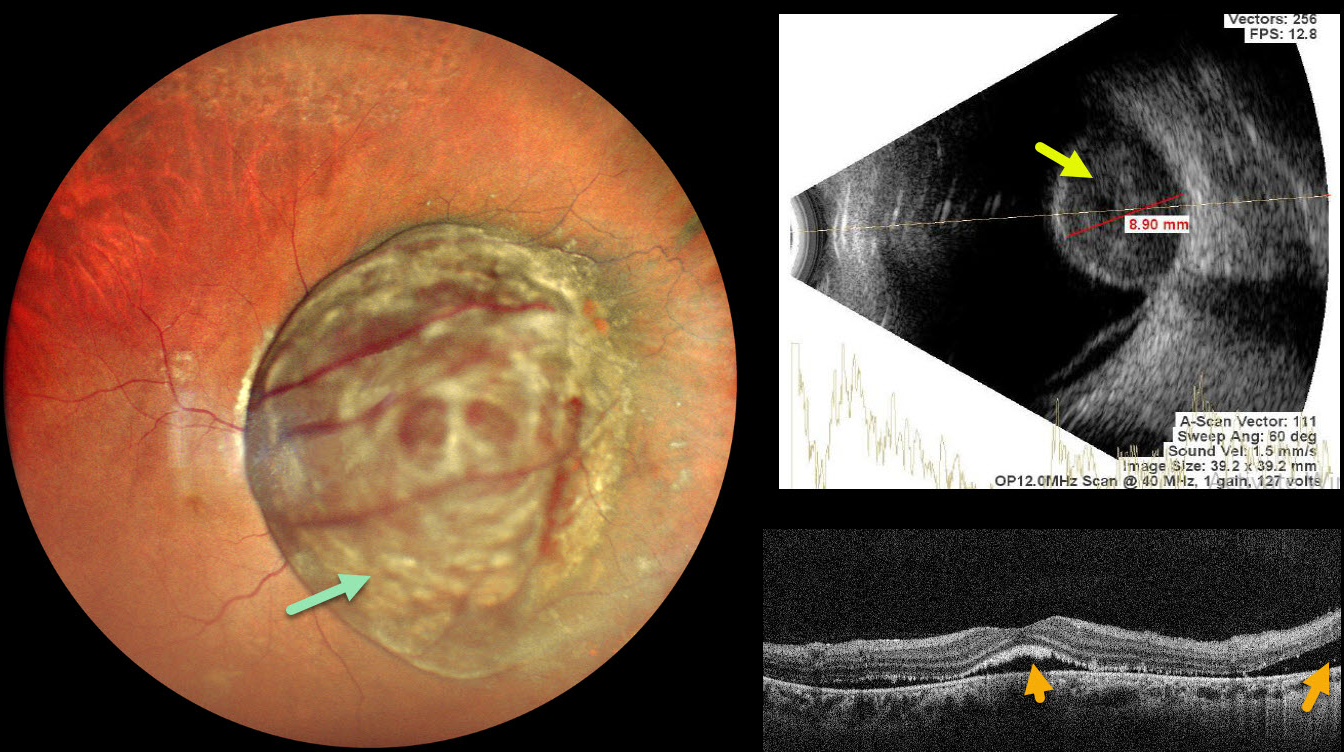
This 47YO female presented with 1 month of decreased vision in her right eye. Vision was 20/400 OD and 20/20 in her normal OS.
Pseudocolor SLO imaging shows a large, well-circumscribed pigmented choroidal lesion that obscures the entire posterior pole. The tumor vessels are markedly dilated and tortuous. OCT shows foveal and nasal subretinal fluid with ragged shed outer segments along the posterior retinal surface. The lesion, which measures 8.9mm in thickness, shows moderate homogenous internal reflectivity on B-scan ultrasonography. She was referred to ocular oncology for further evaluation and treatment.
Learning Points:
Uveal melanoma is a malignant tumor arising from melanocytes in the uveal tract (iris, ciliary body, or choroid). The choroid is the most common site, accounting for 90% of uveal melanomas. Uveal melanoma is the most common primary intraocular cancer in adults, whereas metastatic disease is the most common intraocular malignancy. The liver is the most common metastatic site, although metastatic disease is rare on presentation. Metastases are more common with large tumors, BAP1 mutations, and certain tumor-related genetic markers (including positive PRAME and Class 2).
UVEAL MELANOMA
Ayushi Gupta and Vishal Agrawal
Originally posted on @retina.rocks July 7, 2025
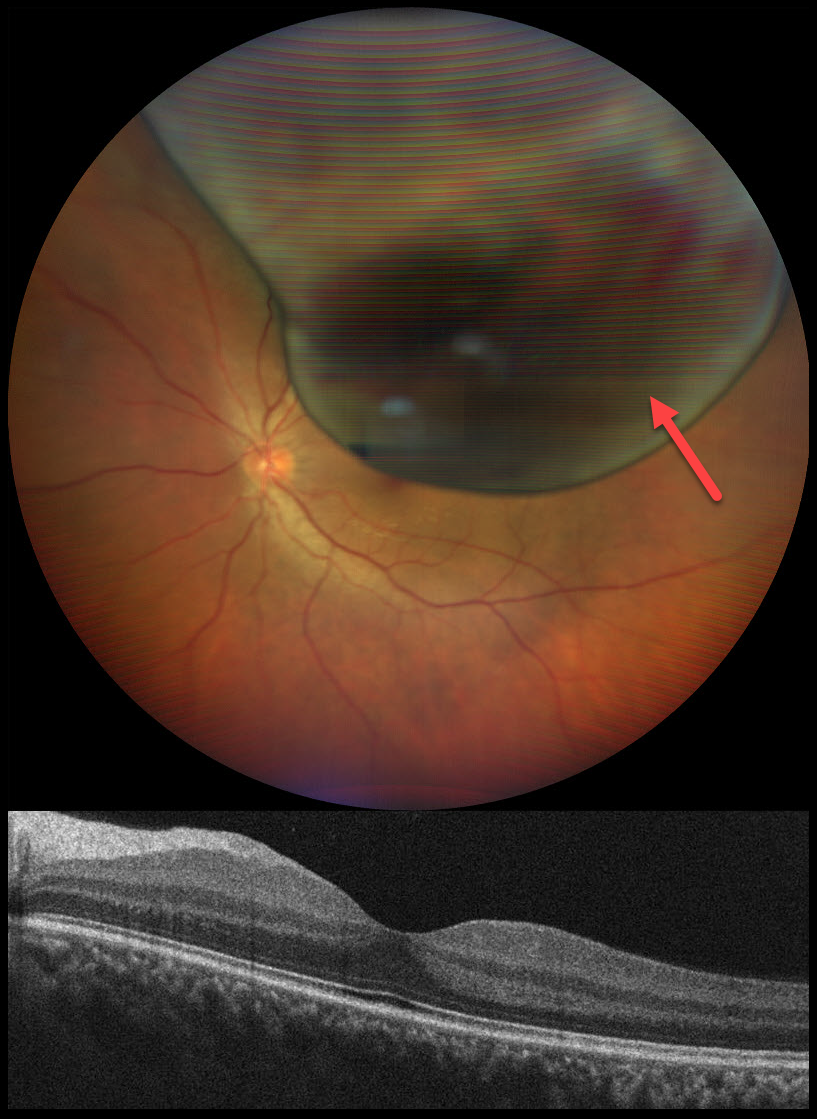
This 32YO male presented with a peripheral shadow of vision in his left eye for several weeks. Vision was 20/20 OU.
Color photography shows a large, elevated, well- defined, pigmented choroidal mass with a few overlying hemorrhages. Despite the lesion nearly draping over the central macula, foveal OCT scanning is remarkably normal. He was immediately referred to an ocular oncologist for a presumed uveal malignant melanoma. He was immediately lost to follow up.
Learning Points:
Uveal melanoma is a malignant tumor arising from melanocytes in the uveal tract (iris, ciliary body, or choroid). The choroid is the most common site, accounting for 90% of uveal melanomas. Uveal melanoma is the most common primary intraocular cancer in adults, whereas metastatic disease is the most common intraocular malignancy. The liver is the most common metastatic site, although metastatic disease is rare on presentation. Metastases are more common with large tumors, BAP1 mutations, and certain tumor-related genetic markers (including positive PRAME and Class 2).
Despite our patient having normal vision, their left eye harbored a blinding and potentially lethal uveal MM. This reminds us why we must always listen to our patient and explain their symptoms even with a normal acuity.
RECURRENT UVEAL MELANOMA
Originally posted on @retina.rocks May 19, 2025
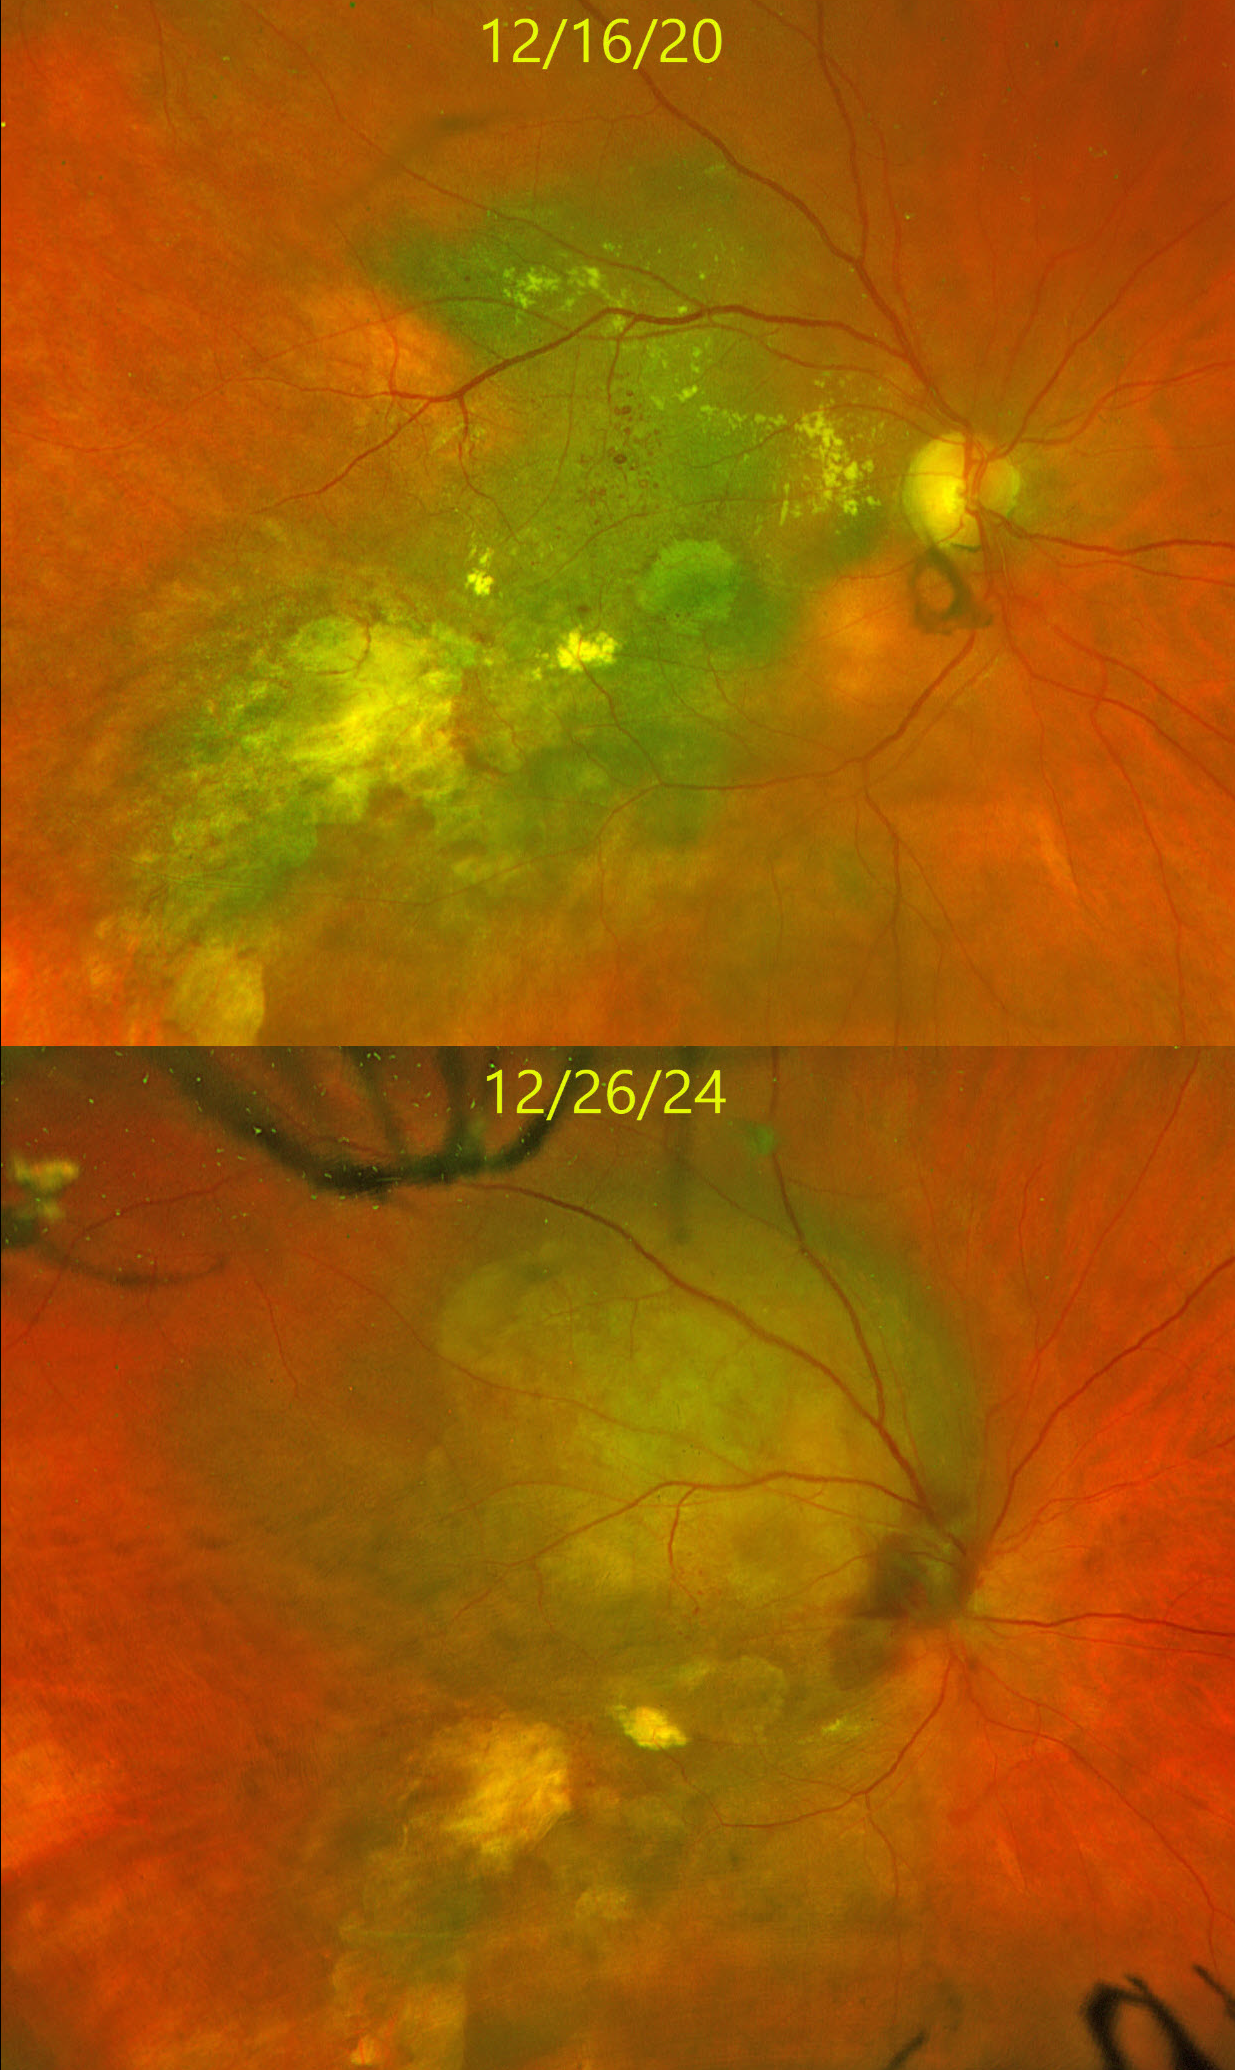
This 66YO female underwent plaque radiotherapy for a uveal malignant melanoma (MM) seventeen years earlier in 2007. The tumor responded well to this single treatment, and she has been followed twice yearly since. On 12/16/24, she had no new symptoms, and vision was stable at counting-fingers.
When examined about 8 months earlier, on 3/13/24, the tumor was stable compared with the prior Optos color RG image from 12/16/20. On the 12/26/24 visit, there is marked tumor growth with apparent optic nerve involvement/
Metastatic workup, including brain MRI and CT of the chest, abdomen, and pelvis, showed no metastases. She was referred to ocular oncology for further management.
Learning Points:
It is extremely rare for a previously dormant tumor to recur so many years following initially successful treatment. The Collaborative Ocular Melanoma Study (COMS) found that local treatment failure occurred in 10% of eyes, most commonly within 3 years of treatment (Jampol et al, Ophthalmology 2002;109:2197-2206). Our case highlights the need for continued long-term monitoring of these patients.
UVEAL MELANOMA
Ankit Jain and Manish Nagpal
Originally posted on @retina.rocks May 8, 2025
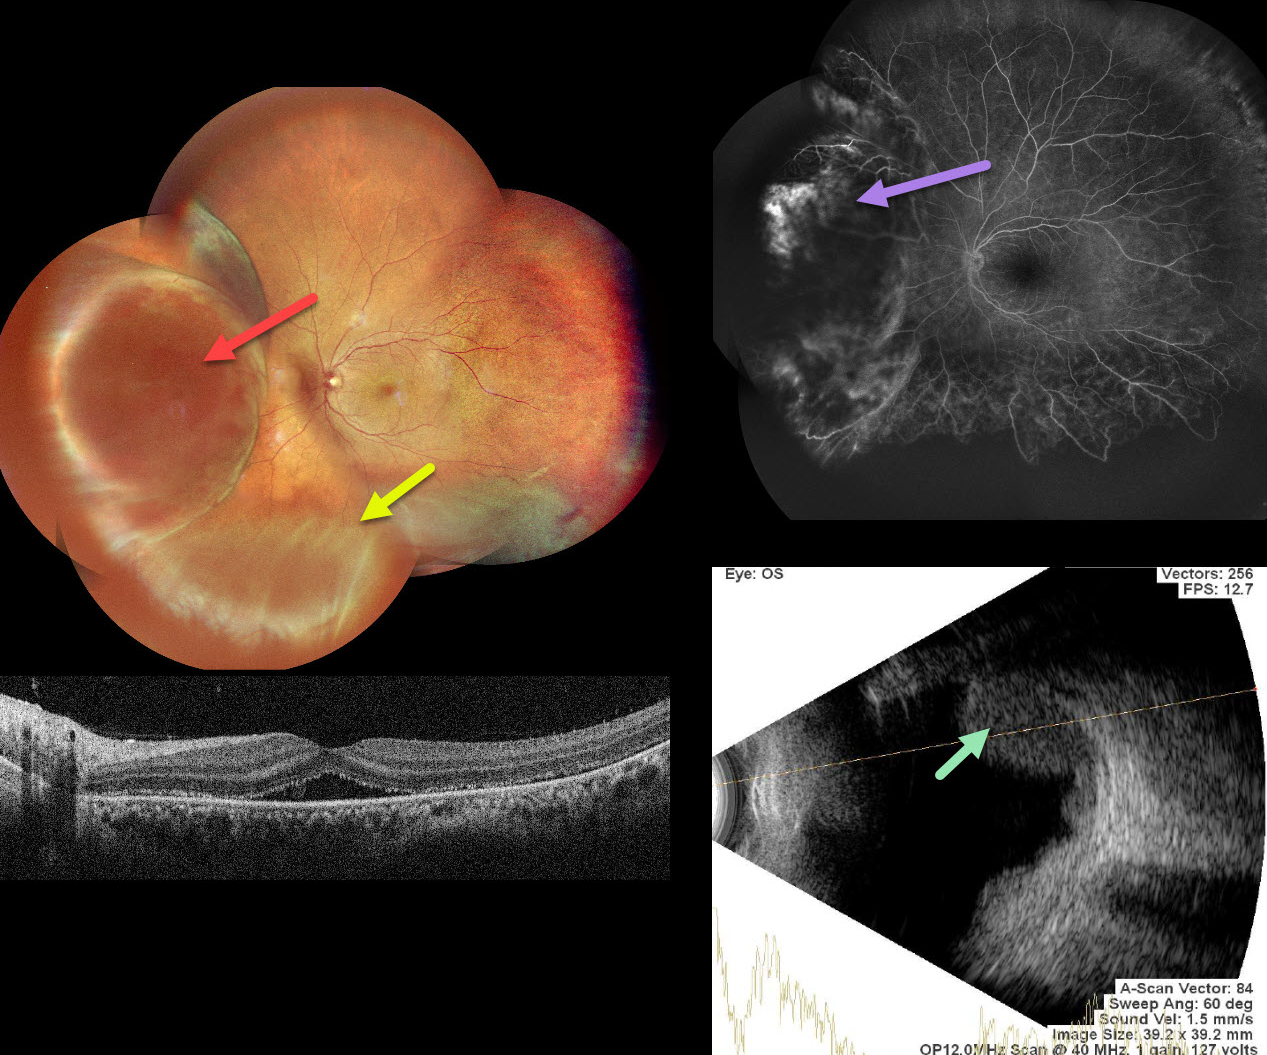
This 39 YO female presented with 1 month of decreased vision in her left eye. Vision was 20/20 in his normal OD and 20/60 OS.
Pseudocolor SLO imaging shows a large, nasal, well-circumscribed amelanotic choroidal lesion with an inferior exudative retinal detachment. OCT shows foveal subretinal fluid with likely shed outer segments along the posterior retinal surface.
Fluorescein angiography shows some leakage within the choroidal tumor. Severe peripheral retinal ischemia is noted temporally and inferiorly. The lesion shows moderate homogenous internal reflectivity on B-scan ultrasonography. MRI (not shown) was suggestive of a uveal malignant melanoma (MM), measuring 11×7 mm in size.
She was referred to ocular oncology for further treatment and evaluation.
CHOROIDAL HEMANGIOMA MISDIAGNOSED AS UVEAL MELANOMA
Originally posted on @retina.rocks November 19, 2024
This 44YO male was referred for recent vision loss from a possible uveal melanoma. Vision was 20/150 in his right eye and 20/20 in his healthy left eye.
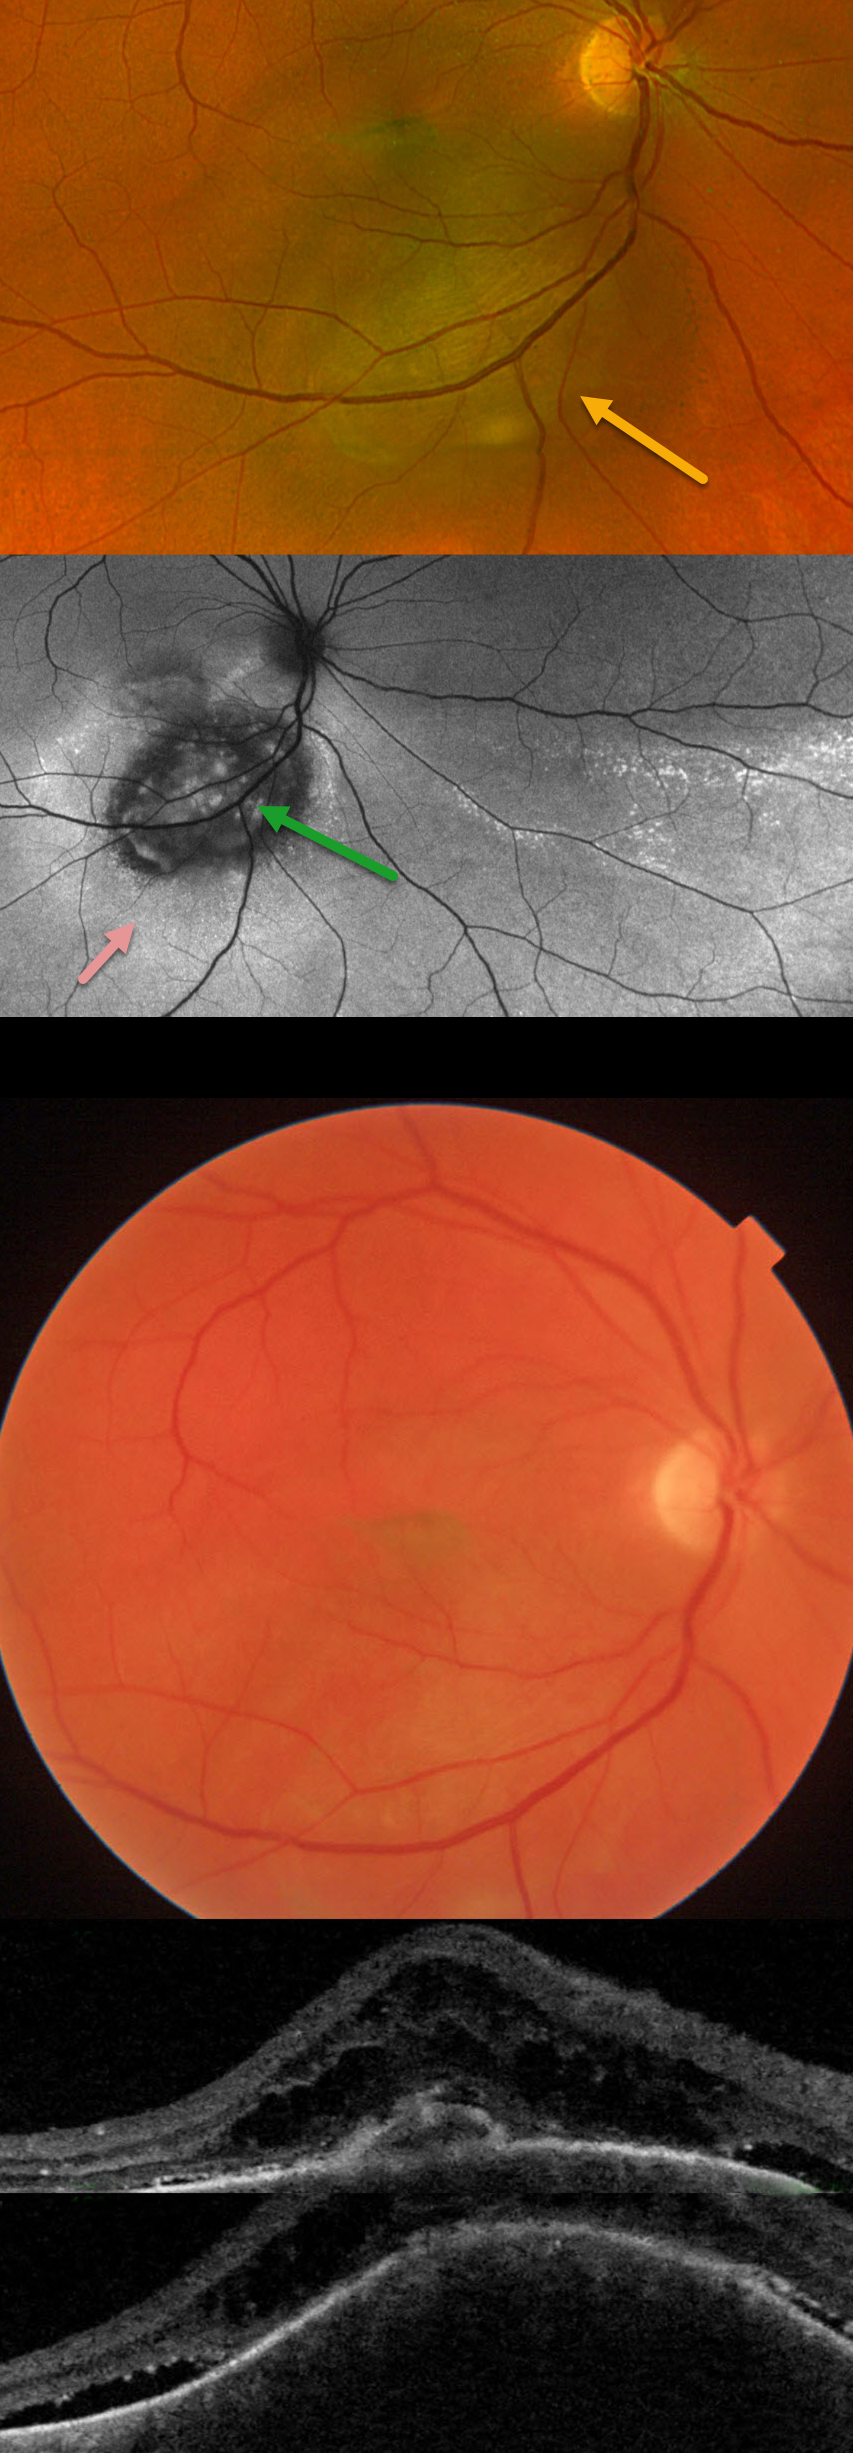
Optos color RG imaging shows an elevated, pigmented subretinal lesion extending from the inferior macula below the inferotemporal arcade. Fundus autofluorescence (FAF) shows this lesion to be hypo-FAF, with surrounding hyper-FAF and areas of hyper-FAF extending into the inferior and inferotemporal midperiphery, indicating prior extramacular subretinal fluid.
Triton color imaging, however, shows the choroidal lesion as orange. Swept-source OCT shows a thickened choroidal lesion with overlying subretinal fluid and cystic retinal edema. The lesion measured 9.6 x 9.0mm in basal diameter and 3.4mm thick with B-scan ultrasonography (not shown). There was moderate-to-high internal reflectivity, consistent with a choroidal hemangioma. Photodynamic therapy was recommended.
Learning Points:
Isolated choroidal hemangiomas are benign vascular lesions. Although they have no malignant potential, they can cause vision loss due to exudation of subretinal and intraretinal fluid, which can be treated with photodynamic therapy (see Tsipursky et al, Surv Ophthalmology 2011;56:68-85).
This lesion was initially misdiagnosed as a uveal malignant melanoma based on the hyperpigmented appearance on Optos RG imaging. This has also been reported in the literature (Becker et al, OSLIR 2023;54:292-296). These images are generated from a red (635nm) and green (532nm) laser. This creates a greenish tint, which distorts the true fundus color. In our patient, this was quite dramatic, with the hemangioma’s true orange color evident only in the Triton image. A newer Optos true-color RGB unit has recently been introduced, which maintains the ability to view the separate RG channels while also generating a true-to-life color image.
PSEUDO-UVEAL MELANOMA FROM NEOVASCULAR AMD SUBRETINAL FIBROSIS
Fraser McKay
Originally posted on @retina.rocks June 20, 2024
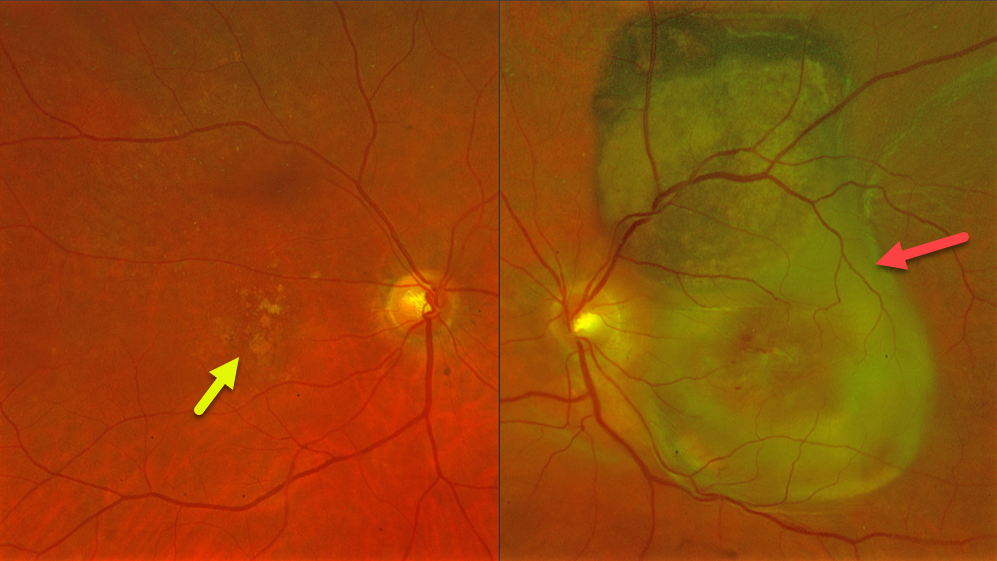
This 78YO female presented with at least several months of vision loss in her left eye. Vision was 20/40 OD and light perception OS. She was examined 2 years earlier with 20/400 vision OS from macular atrophy.
Optos color RG imaging OS shows a variably pigmented and slightly thickened subretinal lesion extending from the superior macula into the superior midperiphery. Subretinal fibrosis extends through the macula, along with retinal blood dots. Intermediate AMD with mixed drusen was noted OD.
Learning Points:
Suprachoroidal, subretinal, or sub-RPE blood can rarely simulate a uveal malignant melanoma. We suggested a trial of monthly anti-VEGF therapy for this treatment naïve neovascular AMD lesion, although the visual prognosis remains quite guarded given the extent of submacular fibrosis.
UVEAL MELANOMA
Janelle Adeniran
Originally posted on @retina.rocks June 4, 2024
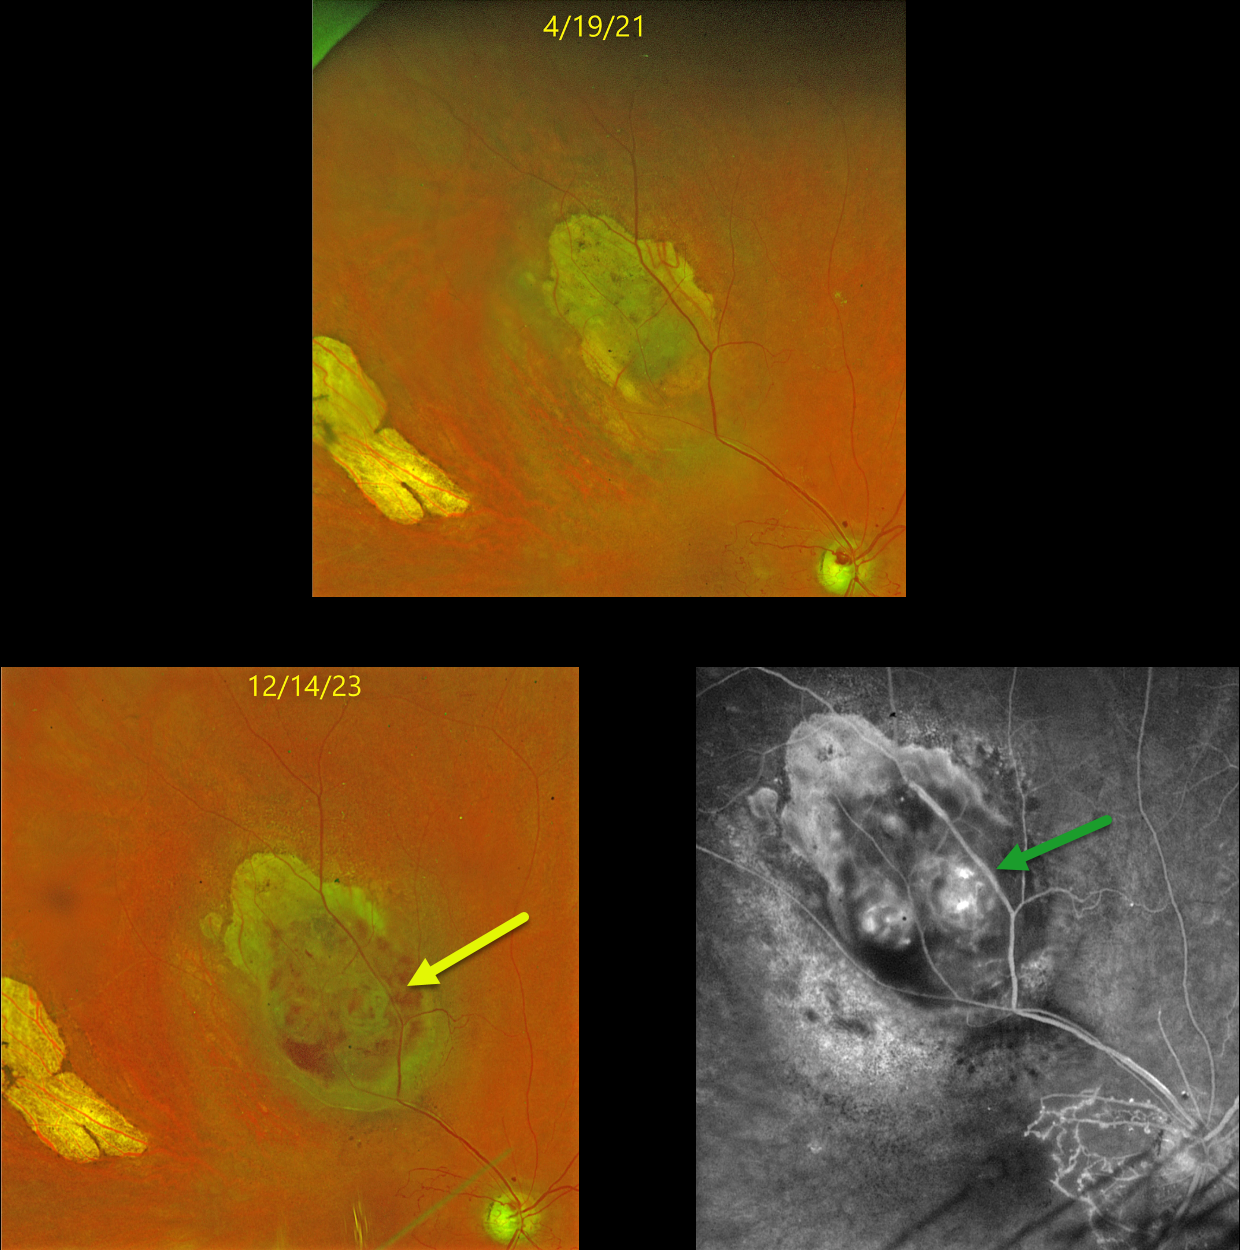
This 59YO female underwent iodine-125 plaque therapy in 2010 for a uveal malignant melanoma (MM) in her right eye. The tumor initially regressed and has remained stable with yearly examinations since. Vision has been stable at counting fingers due to a secondary branch retinal vein occlusion and radiation retinopathy.
In June 2023, she presented with new floaters and vision loss in this eye from a new moderate vitreous hemorrhage coming from the MM. Vision was light perception. Once the blood cleared following an intravitreal Avastin injection, the tumor showed some hemorrhages within or anterior to the lesion on Optos color RGB imaging.
Fluorescein angiography showed intrinsic vascularity and profound macular capillary loss. B-scan ultrasonography revealed a nodular appearance with heterogeneous echogenicity (not shown). There was definite growth compared with the tumor size several years earlier. Metastatic workup was negative. After extensive discussion, the patient elected for enucleation, which was scheduled in the near future.
Learning Points:
The Collaborative Ocular Melanoma Study (COMS) reported a 10% 5-year local treatment failure rate following plaque radiation (Jampol et al., Ophthalmology 2002;109:2197-2206). Our patient’s failure developed about 13 years following brachytherapy and reminds us of the need for long-term surveillance of these treated tumors.
UVEAL MELANOMA
Giovanni Cuffaro
Originally posted on @retina.rocks February 6, 2023
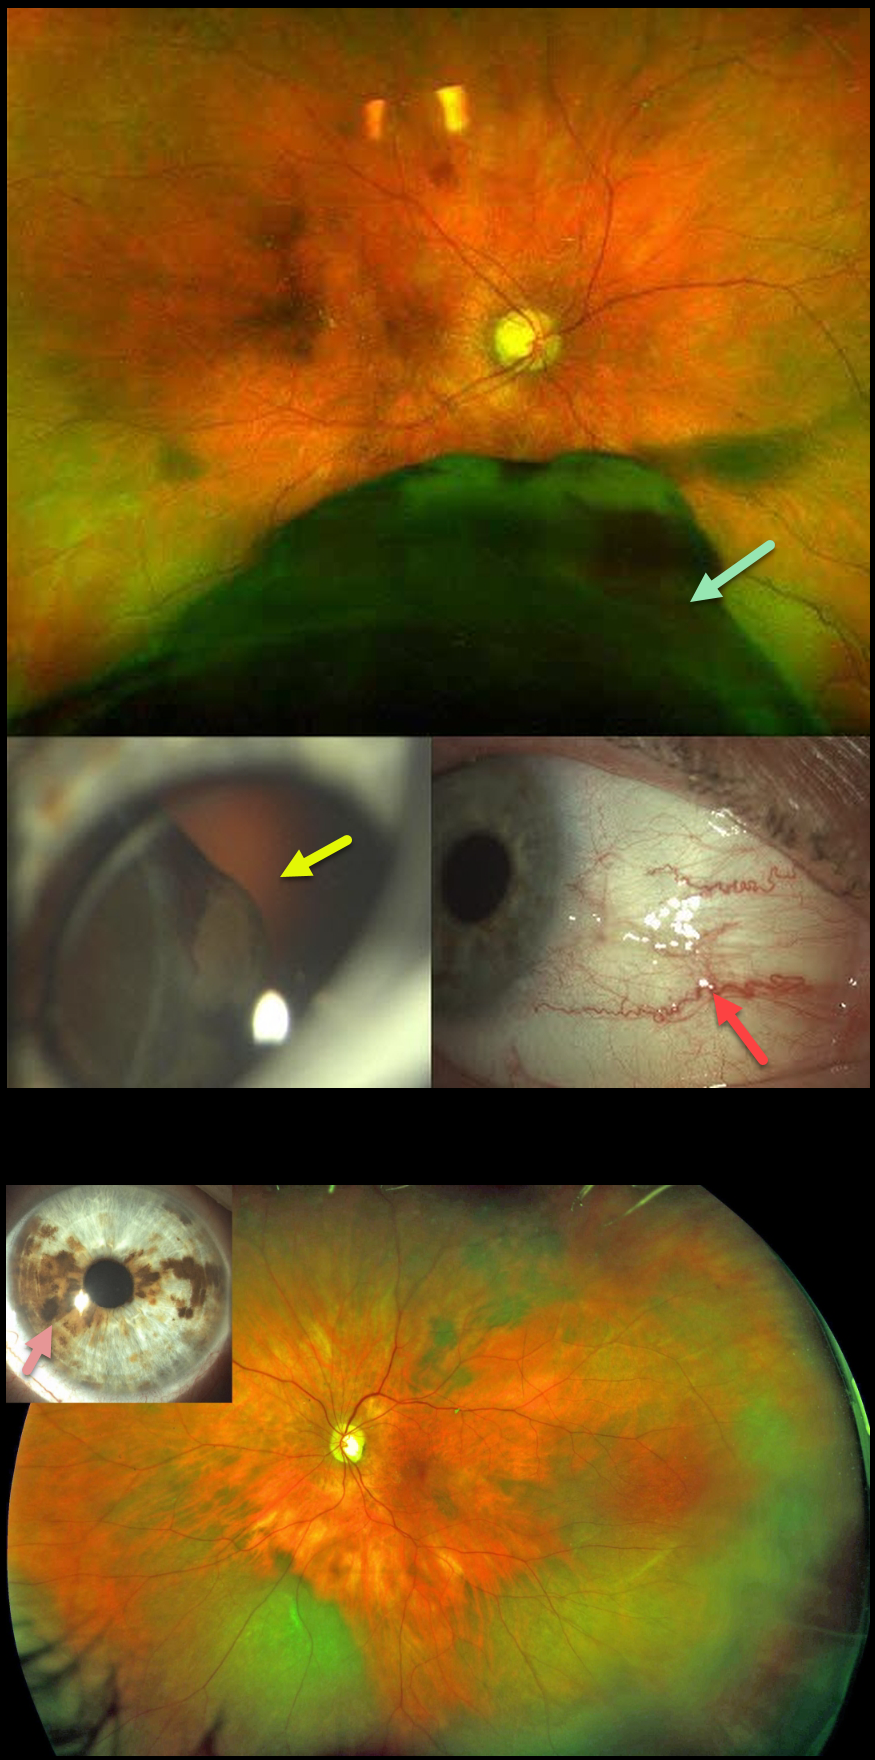
This 71YO female presented in January 2019 with one month of photopsias in her right eye. Optos imaging shows a large inferior malignant melanoma (MM) extending from the inferior retinal periphery into the posterior pole. The tumor was visible through the pupil at the slit lamp, and sentinel vessels were noted. Ocular melanocytosis was noted in the left eye.
She underwent primary enucleation of the right eye one month later. There was complete monosomy 3, and HLA-A*0201 testing was positive.
She subsequently developed a peripheral inferotemporal uveal malignant melanoma in her left eye (axial thickness 5mm, lateral dimensions 13.5 by 13 mm), which was treated with brachytherapy in March 2020. In October 2021, she developed liver metastases.
She was placed on systemic Nivolumab, in addition to external radiotherapy to the liver lesions. Vision is currently 20/20 OS with no signs of local recurrence.
Learning Points:
Our patient had a unique combination of unfortunate multiple risk factors for developing uveal malignant melanoma with metastatic disease (see Kaliki et al, Indian J Ophthalmol 2015;62:93-102).
Monosomy 3 is strongly associated with metastatic disease and melanoma-related mortality. The tumor suppressor gene BRCA1-associated protein 1 (BAP1) is mapped to chromosome 3p21.1, which is associated with autosomal dominant uveal MM and other primary cancers.
Choroidal melanocytosis is part of the oculodermal spectrum, which occasionally includes pigmentation of the globe or periocular skin (Nevus of Ota, melanosis oculi). There are increased dendritic melanocytes in the affected tissues following the distribution of the first and second branches of the trigeminal nerve. Patients need ongoing monitoring since about 1 in 400 will develop uveal melanoma. Those who develop melanoma are twice as likely to undergo metastasis when compared to patients with uveal melanoma and no pre-existing melanocytosis.
For a recent review of oculodermal melanocytosis, see Abdolrahimzadeh et al, Graefe’s 2023;261:291-301.
UVEAL MELANOMA
Originally posted on @retina.rocks January 18, 2023
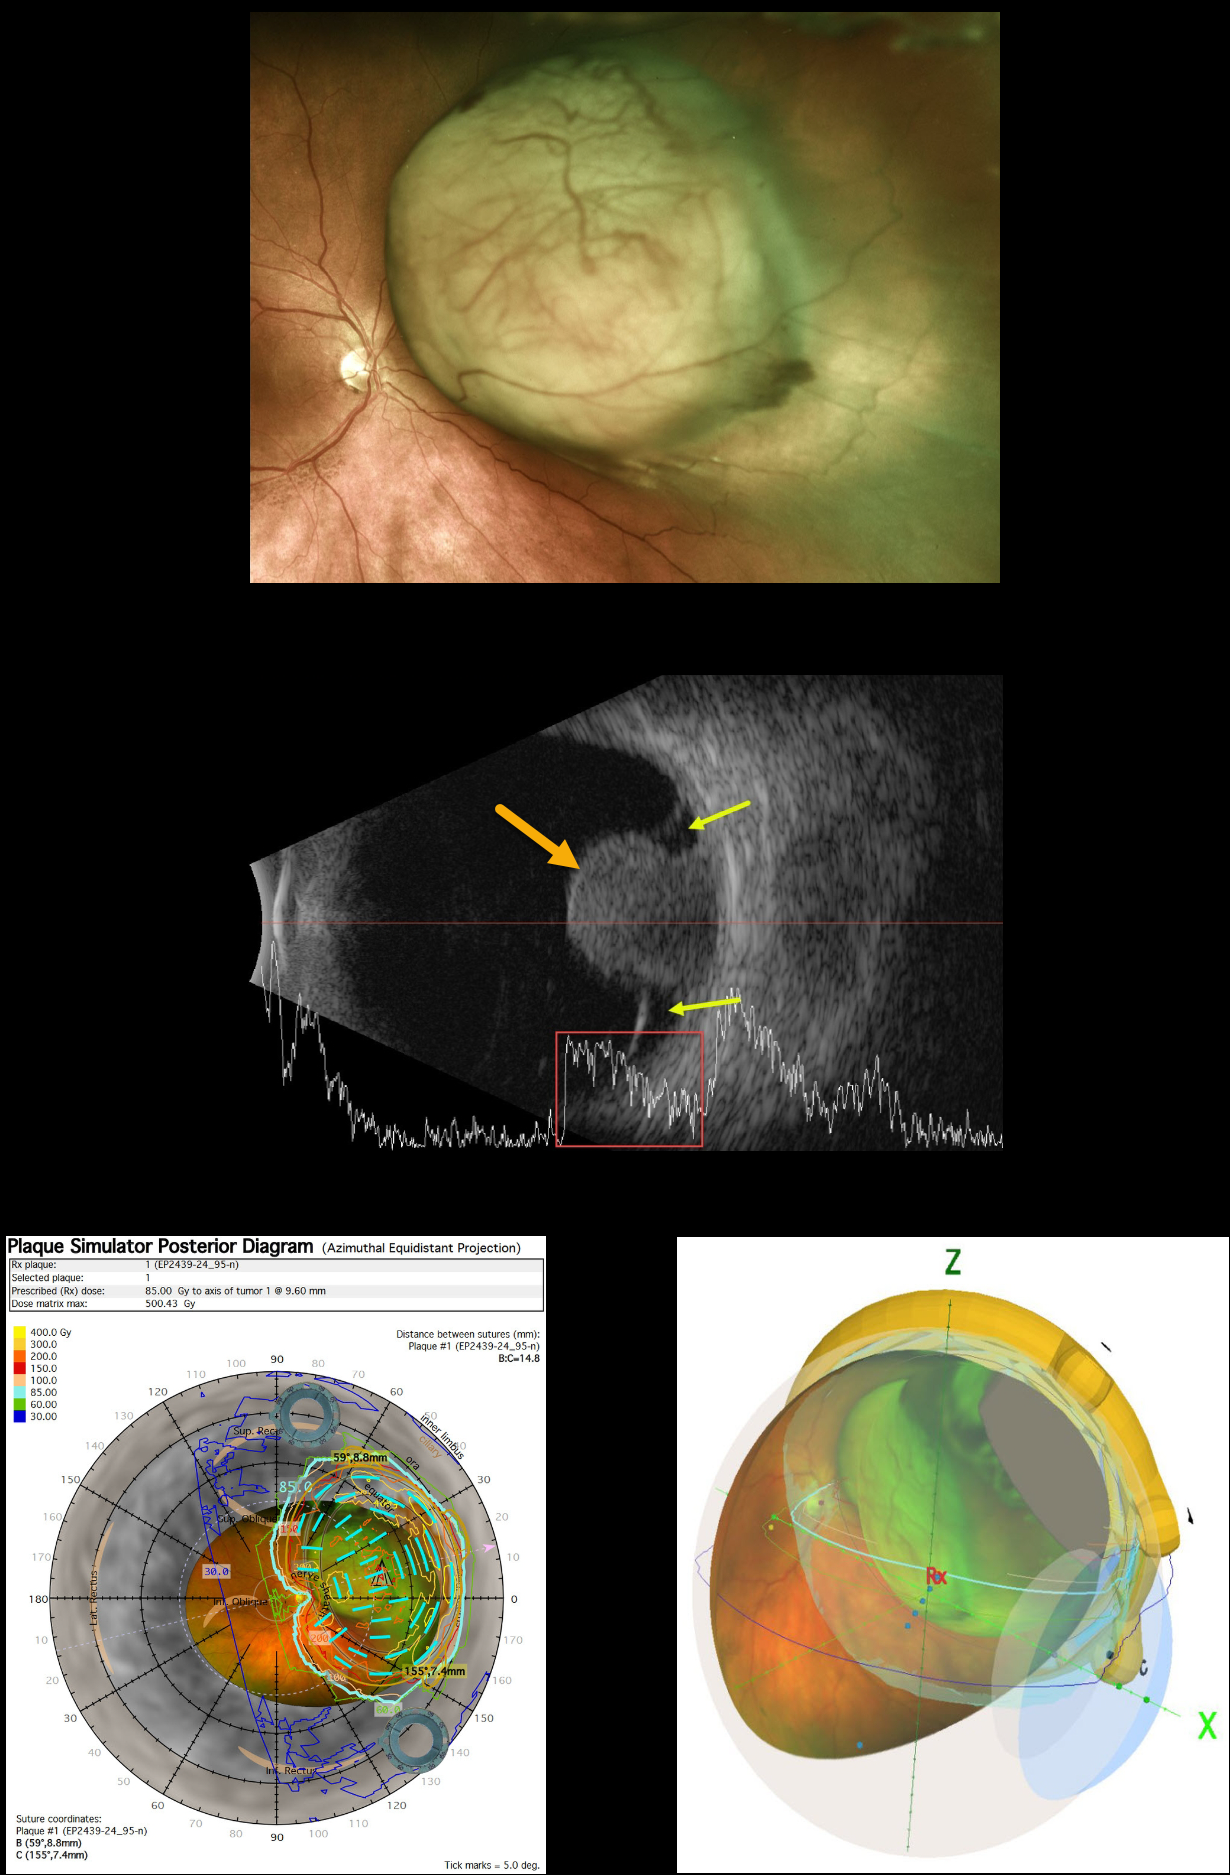
This 63YO female presented with several weeks of peripheral vision loss in her left eye. Vision was 20/40.
Optos color imaging shows a large, mostly amelanotic, mushroom-shaped choroidal lesion extending from just nasal to the nerve into the midperiphery. Intrinsic large vessels are noted. The lesion measured 11.5 × 14.5 mm in lateral dimensions.
Ultrasonography shows a mushroom-shaped choroidal tumor that measured 9.6mm in thickness. Localized subretinal fluid is seen on either edge. The lesion has moderate internal reflectivity.
Plaque radiotherapy of the uveal malignant melanoma (MM) was performed. The plaque simulator images created by the radiation oncologist during the design of the custom plaque with radioactive I-131 seeds are shown.
UVEAL MELANOMA
Originally posted on @retina.rocks May 30, 2022
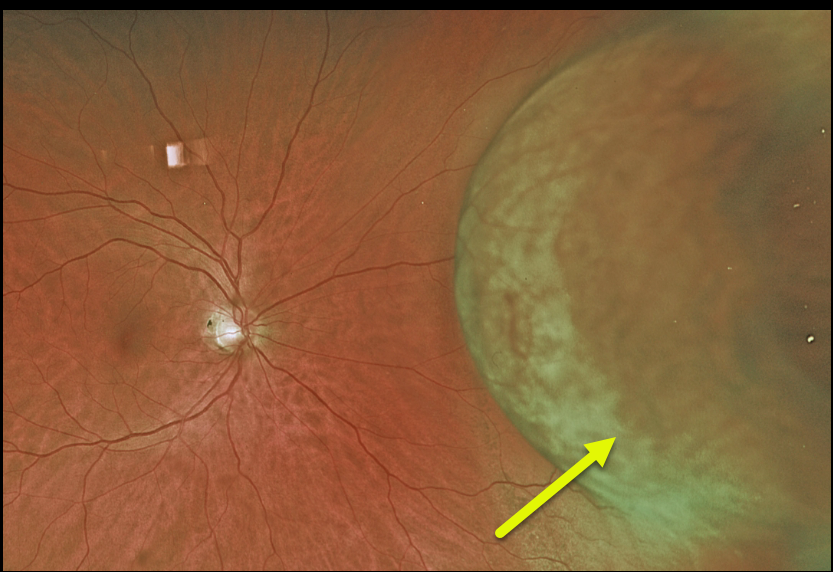
This healthy 51YO female presented with one year of increasing flashes in her right eye. Vision was 20/25. Funduscopic examination revealed a large, variably pigmented nasal choroidal mass measuring at least 9.7mm in the largest basal diameter.
She was referred for further evaluation and treatment for a presumed uveal malignant melanoma.
UVEAL MELANOMA
Originally posted on @retina.rocks April 20, 2022
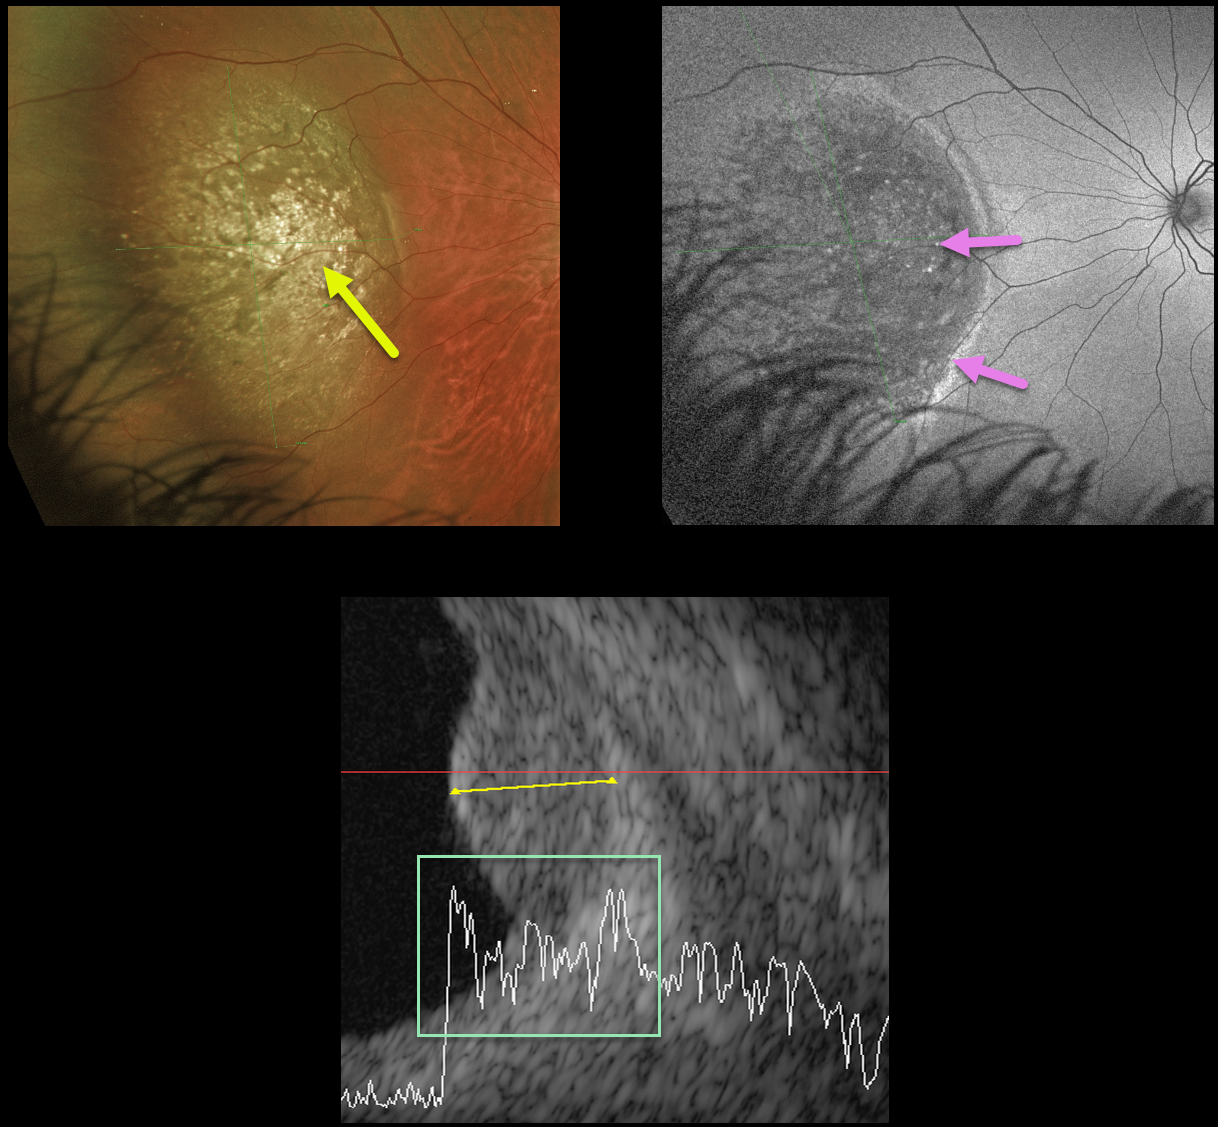
This 25YO male presented with this asymptomatic choroidal mass in his left eye. Vision was 20/20.
Optos color imaging shows a large, well-defined variably pigmented lesion with numerous overlying drusen in the nasal fundus. The lesion shows variable hypo- and hyper-autofluorescence.
B-scan ultrasonography shows moderate internal reflectivity. It measured 4 mm thick and 13.5 mm at its widest diameter.
We felt this lesion was a uveal malignant melanoma and referred him to an ocular oncologist for further evaluation and treatment.
UVEAL MELANOMA
Originally posted on @retina.rocks March 8, 2022
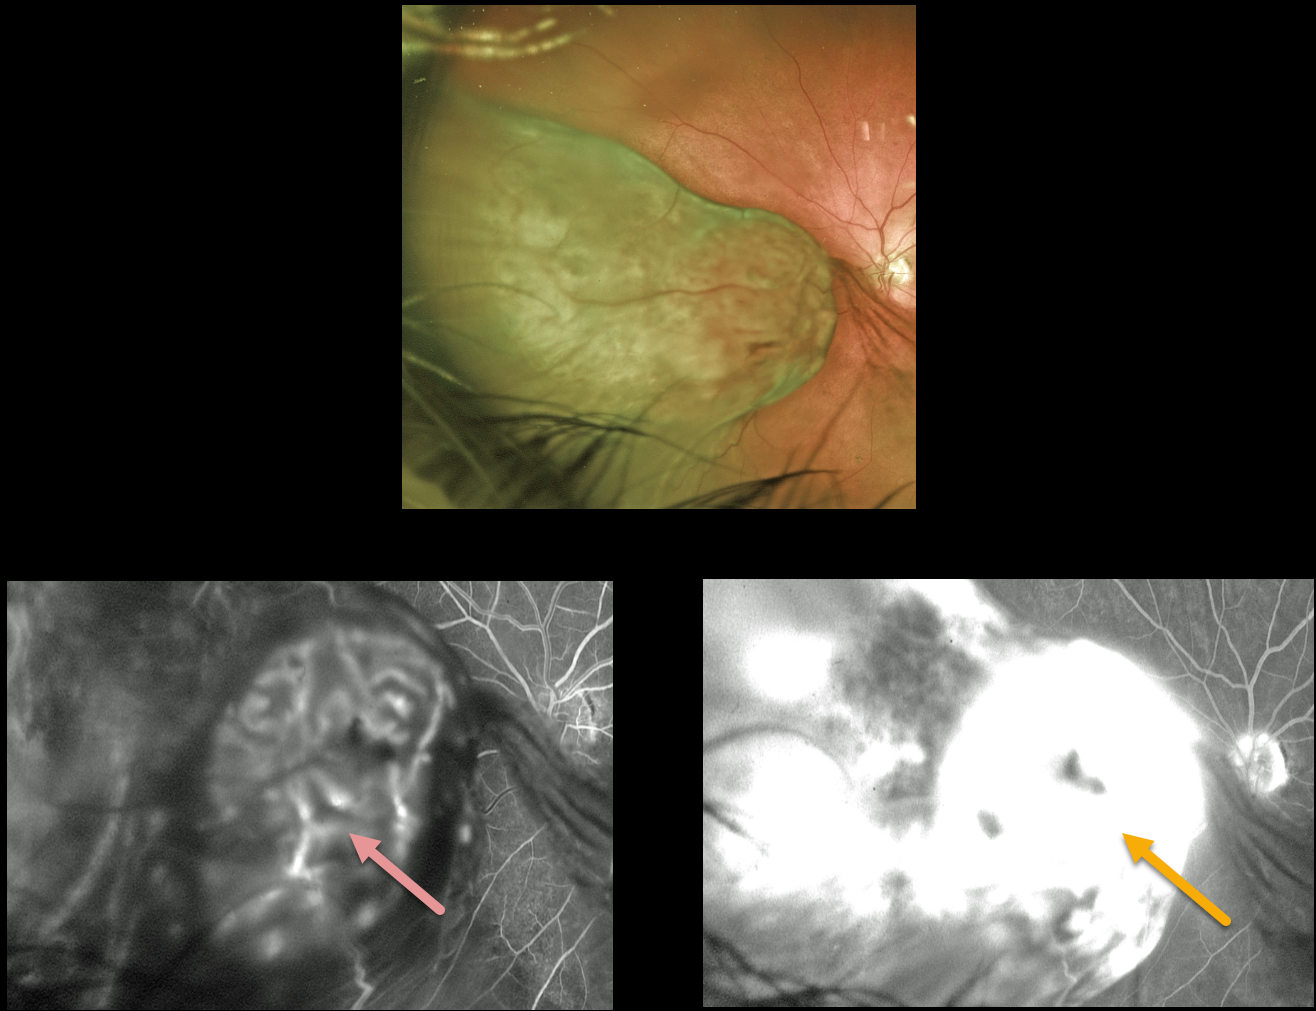
This 81YO male presented with a 9.5mm-thick uveal malignant melanoma with fan-like opacities emanating from the apex of the tumor in his left eye. We suspected early vitreous hemorrhage, pigment shedding, or vitreous seeding.
Early phase angiogram beautifully reveals its internal vascularity, with late leakage from the entire tumor. Vision was 20/70.
The patient underwent diagnostic vitrectomy with plaque radiotherapy. Cytology from the vitreous sample confirmed PRAME, SOX10, and Ki67-positive cells. Genetic expression profiling showed that the tumor was Class 1B, PRAME positive.
Learning Points:
About 20% of patients with a Class 1B lesion will experience clinical metastasis within 5 years. PReferentially expressed Antigen in MElanoma (PRAME) is a gene that can become aberrantly expressed in some malignancies. Its positivity can indicate an increased risk for metastatic disease in Class 1 tumors, but its negativity does not tend to alter prognosis.
Vitreous seeding from a choroidal melanoma before surgical intervention is exceedingly rare. Various approaches have been taken, including immediate enucleation (Cheng et al, Taiwan Journal of Ophthalmology 2017;7:168-171), close observation for recurrence or further seeding (Metz et al, Br J Ophthalmol 2016;100:660-664), or delivery of intravitreal melphalan (Masoomian et al, Retin Cases Brief Rep 2021;15:97-100).
UVEAL MELANOMA
Originally posted on @retina.rocks November 3, 2021
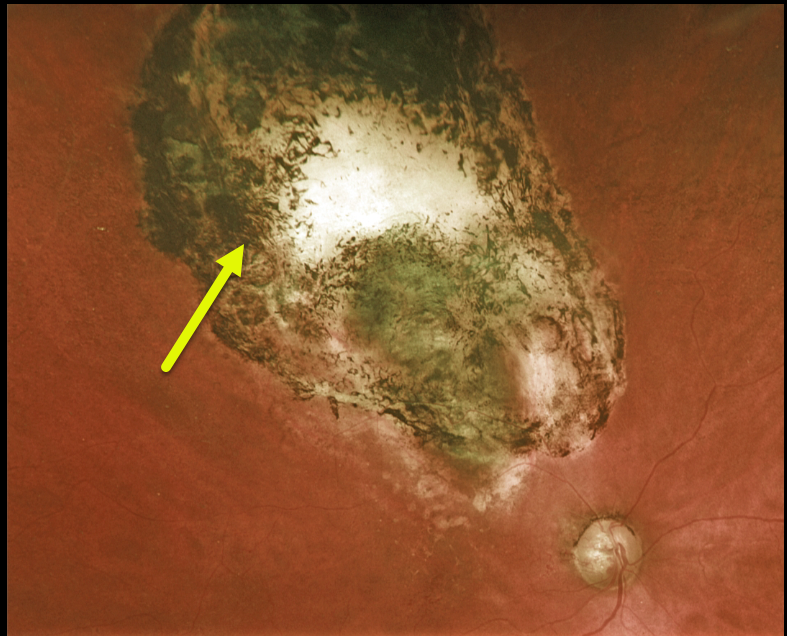
This 75YO female has a history of bilateral uveal malignant melanoma and is now monocular following enucleation of her left eye in 2001.
Plaque therapy in 2011 successfully saved her right eye, and the tumor has completely regressed.
Unfortunately, vision is 20/200 due to prior radiation retinopathy and possible glaucomatous optic neuropathy.
Learning Points:
In the United States, uveal malignant melanoma has an incidence of about 1 in 5 million people per year, and is virtually always unilateral. Primary bilateral uveal melanoma, as in this patient, is exceedingly rare (see Scott et al, Clin Exp Ophthalmology 2018;46:502-510). The BAP1 (BRCA-associated protein 1) germline mutation may be implicated in these cases.
UVEAL MELANOMA
Originally posted on @retina.rocks October 4, 2021
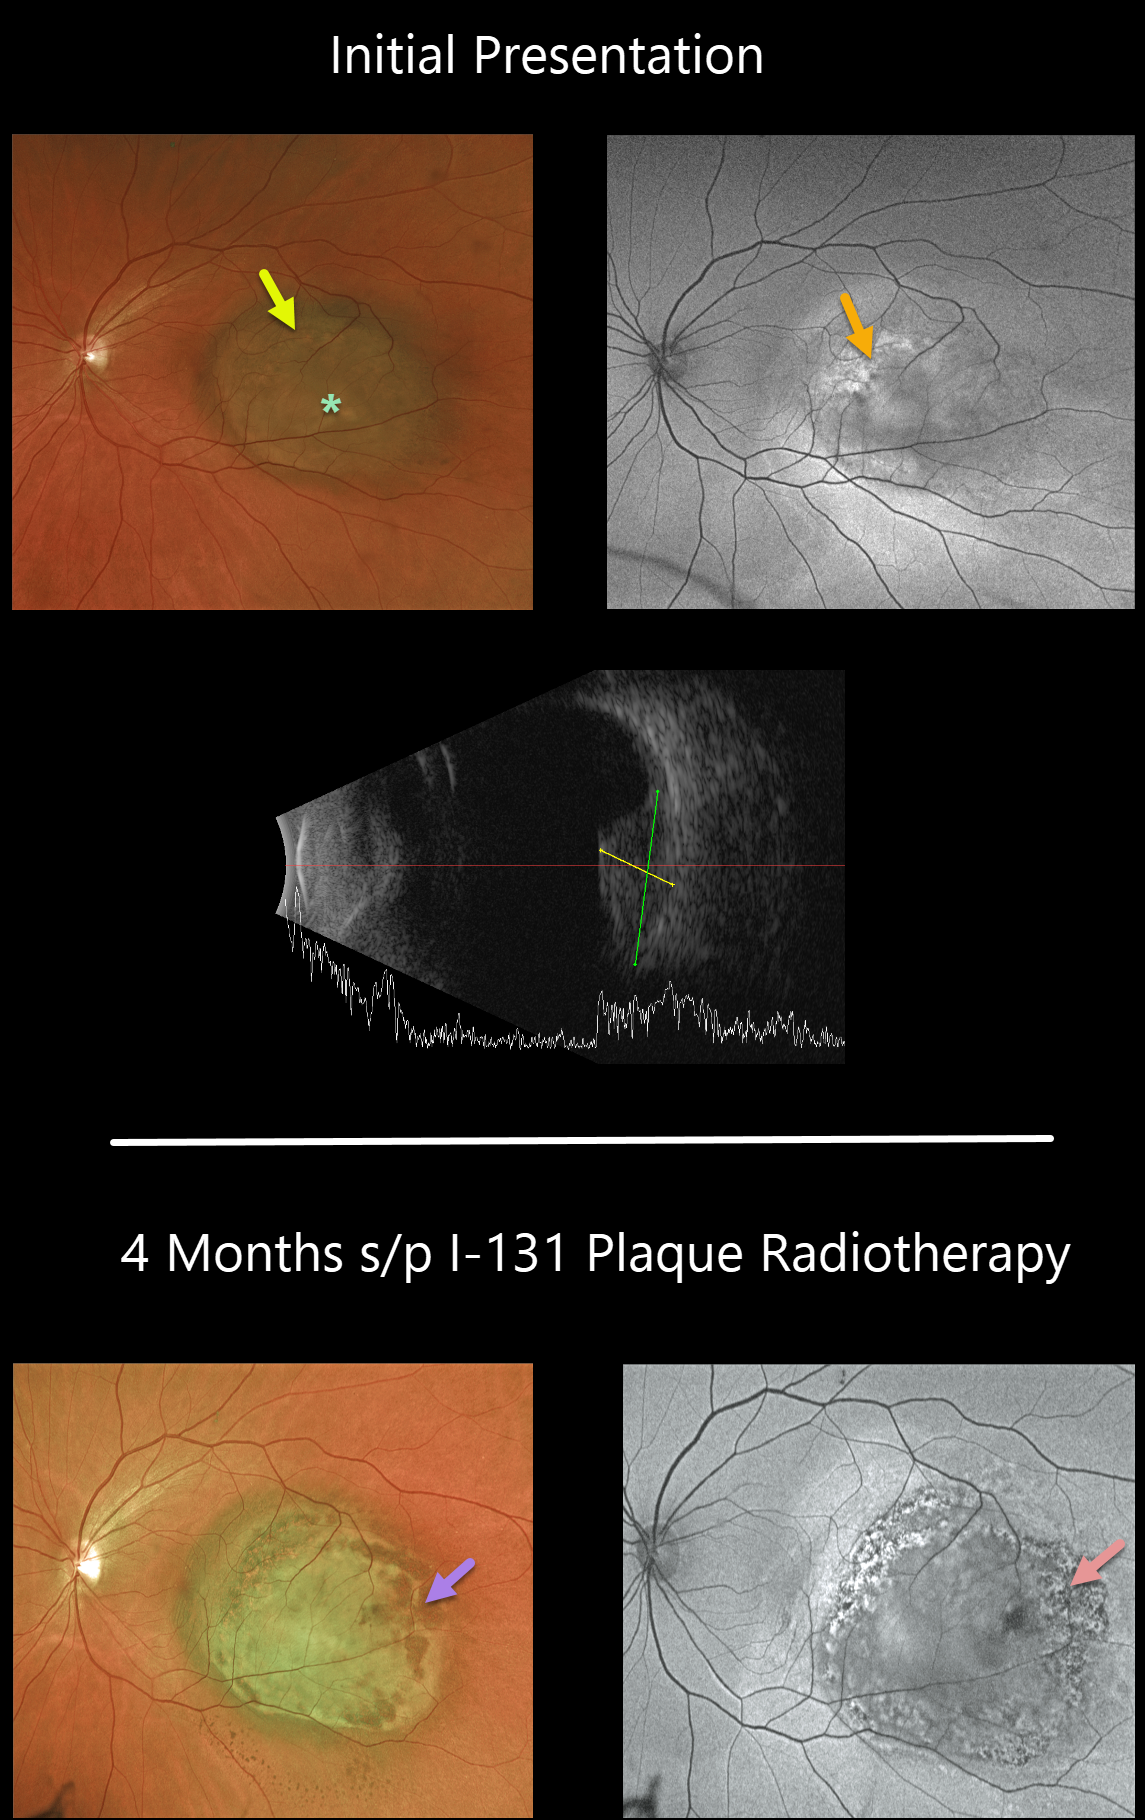
This 53YO male presented on 1/7/21 with a medium-sized posterior pole uveal malignant melanoma. Lipofuscin was noted along the surface of the tumor. Optos fundus autofluorescence (FAF) showed variable hyper- and hypo-FAF. The lesion measured 8 x 11 mm and was 5.5mm thick. Despite its macular location, vision was 20/30.
The patient underwent I-131 plaque radiotherapy. About four months postoperatively, the tumor began to flatten (4.2mm thick), with resolving lipofuscin, coarse pigment clumping, and a generalized decrease in FAF. Vision remained stable.
Genetic testing revealed a Class 2 PRAME-negative lesion.
Learning Points:
Close to 75% of patients with a Class 2 lesion will experience clinical metastasis within 5 years. PReferentially expressed Antigen in MElanoma (PRAME) is a gene that can be aberrantly expressed in some malignancies. Its positivity may indicate a shorter time to metastatic disease, but its negativity does not typically alter prognosis.
RADIATION PAPILLOPATHY
Originally posted on @retina.rocks July 2, 2021
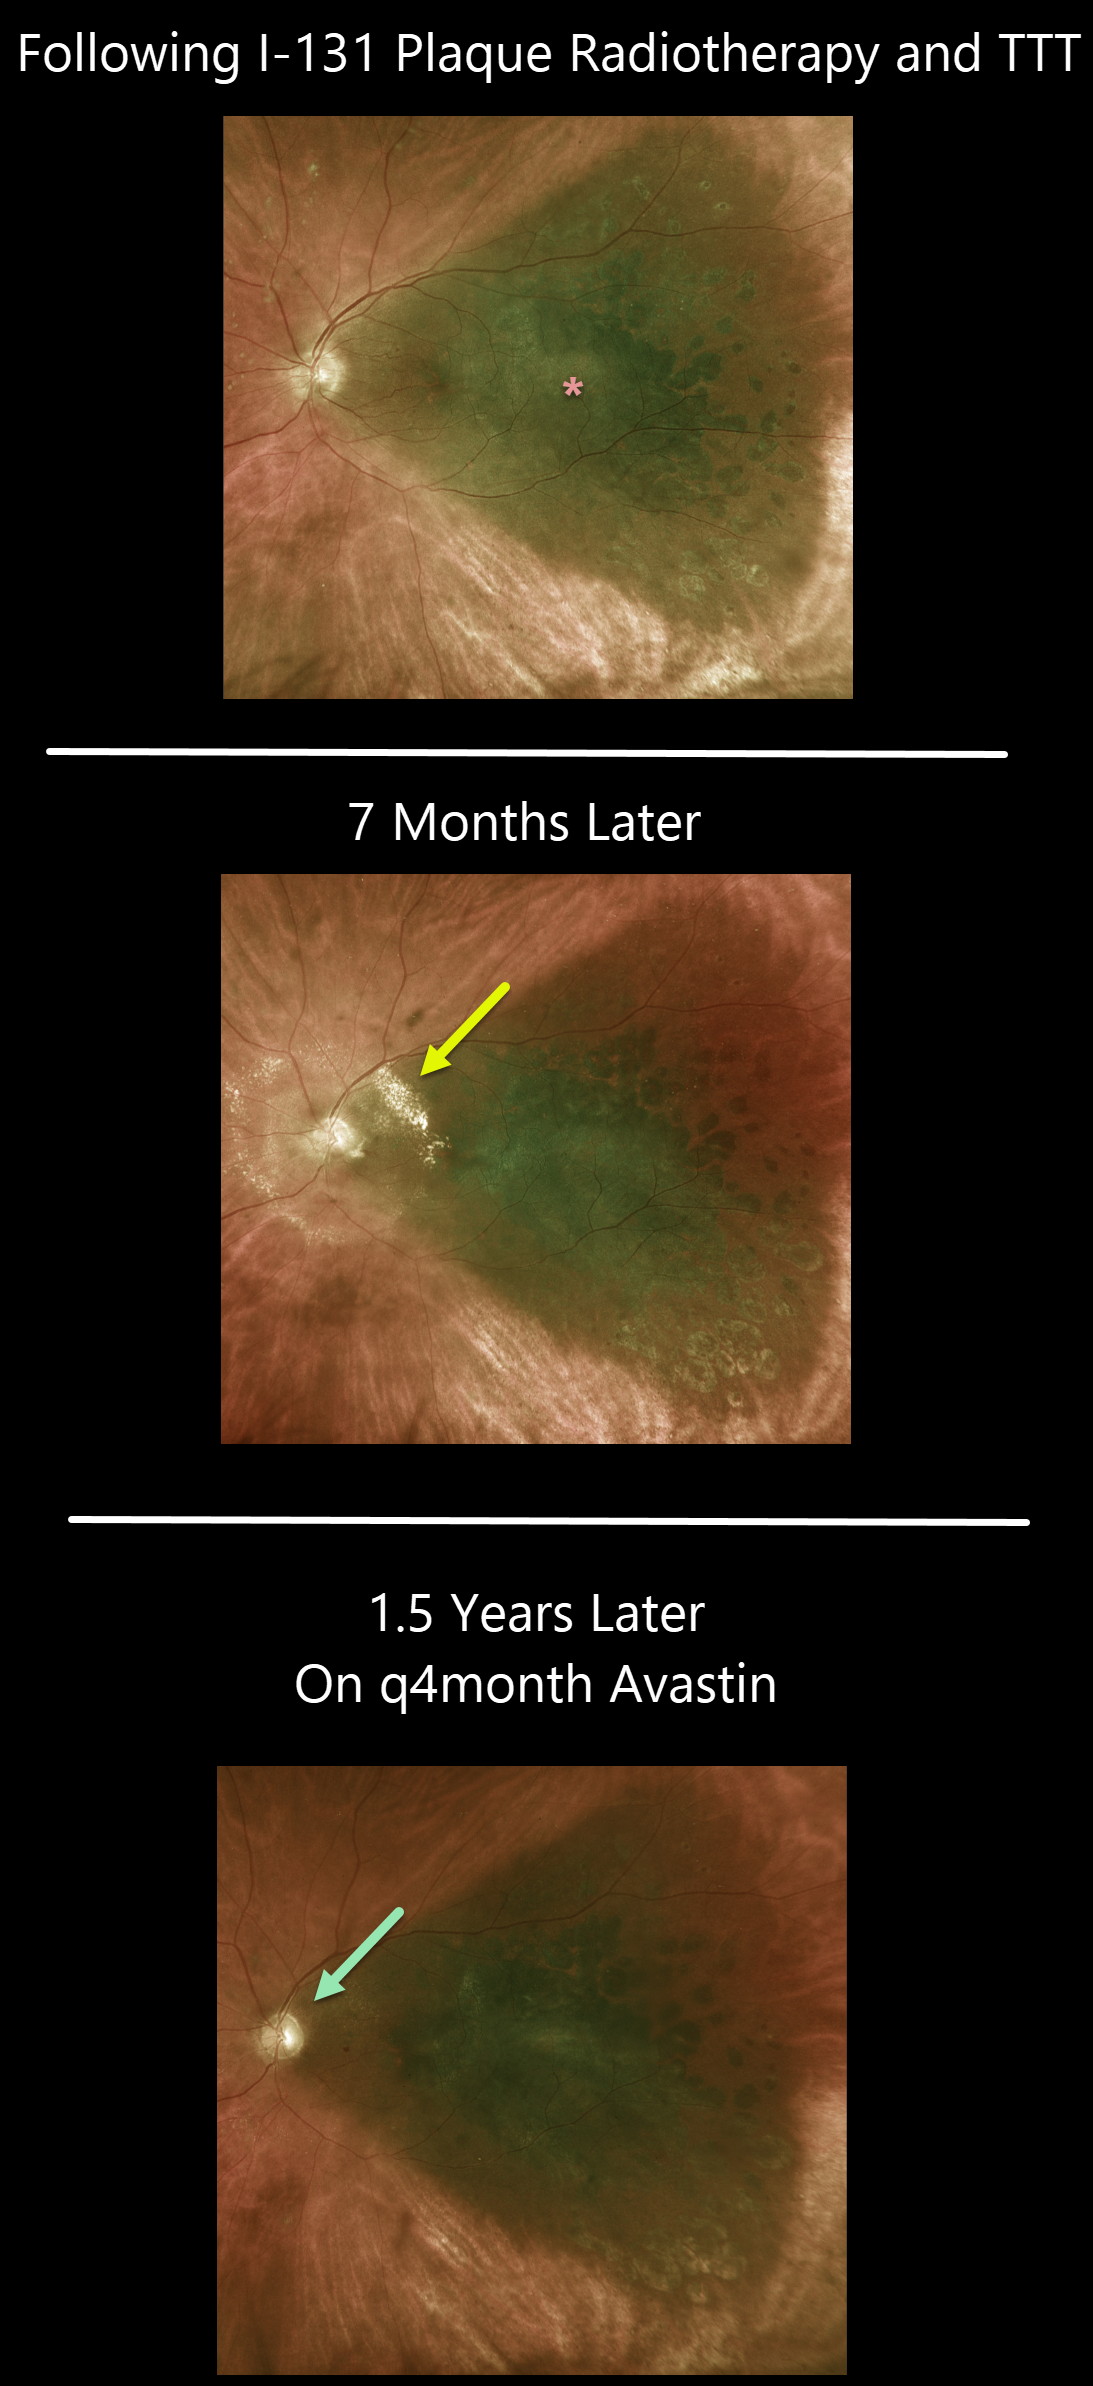
This 66YO male was examined following I-131 plaque radiotherapy and transpupillary thermotherapy for a type 1A, PRAME+ uveal malignant melanoma.
Vision was 20/80, and the tumor was regressing compared to its preoperative appearance (not shown). He was getting intravitreal injections every 4 months as prophylaxis against radiation retinopathy.
The patient returned 8 months later for an overdue examination with new peripapillary lipid from radiation papillopathy. The intravitreal Avastin injections were restarted, and the papillopathy gradually resolved.
Learning Points:
The incidence of radiation retinopathy is relatively high following plaque therapy for uveal malignant melanoma. Ongoing intravitreal injections greatly reduce this complication (see Fallico et al, Surv Ophthalmology 2021;66;441-460).
UVEAL MELANOMA + BRVO
Originally posted on @retina.rocks May 18, 2021
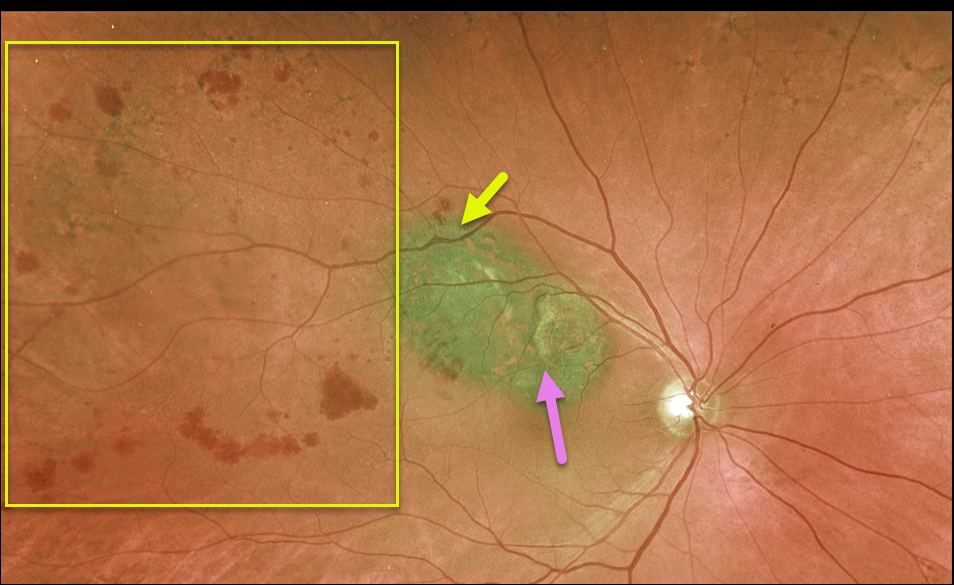
This 78YO male has a history of uveal malignant melanoma (MM), which was successfully treated with initial photodynamic therapy (PDT) (due to the presence of subretinal fluid) followed by transpupillary thermotherapy (TTT) once dry.
He developed a secondary branch retinal vein occlusion (BRVO), likely due to thermal damage from the TTT.
Vision is 20/30, and we continue to follow him closely. A scatter laser will be needed if he develops increasing ischemia with neovascularization from the BRVO.
Learning Points:
BRVOs are virtually always caused by an artery compressing a vein at a shared arteriovenous crossing.
However, rarely, they can occur due to other causes, including inflammation (most commonly sarcoidosis) or secondary to interventions such as TTT.
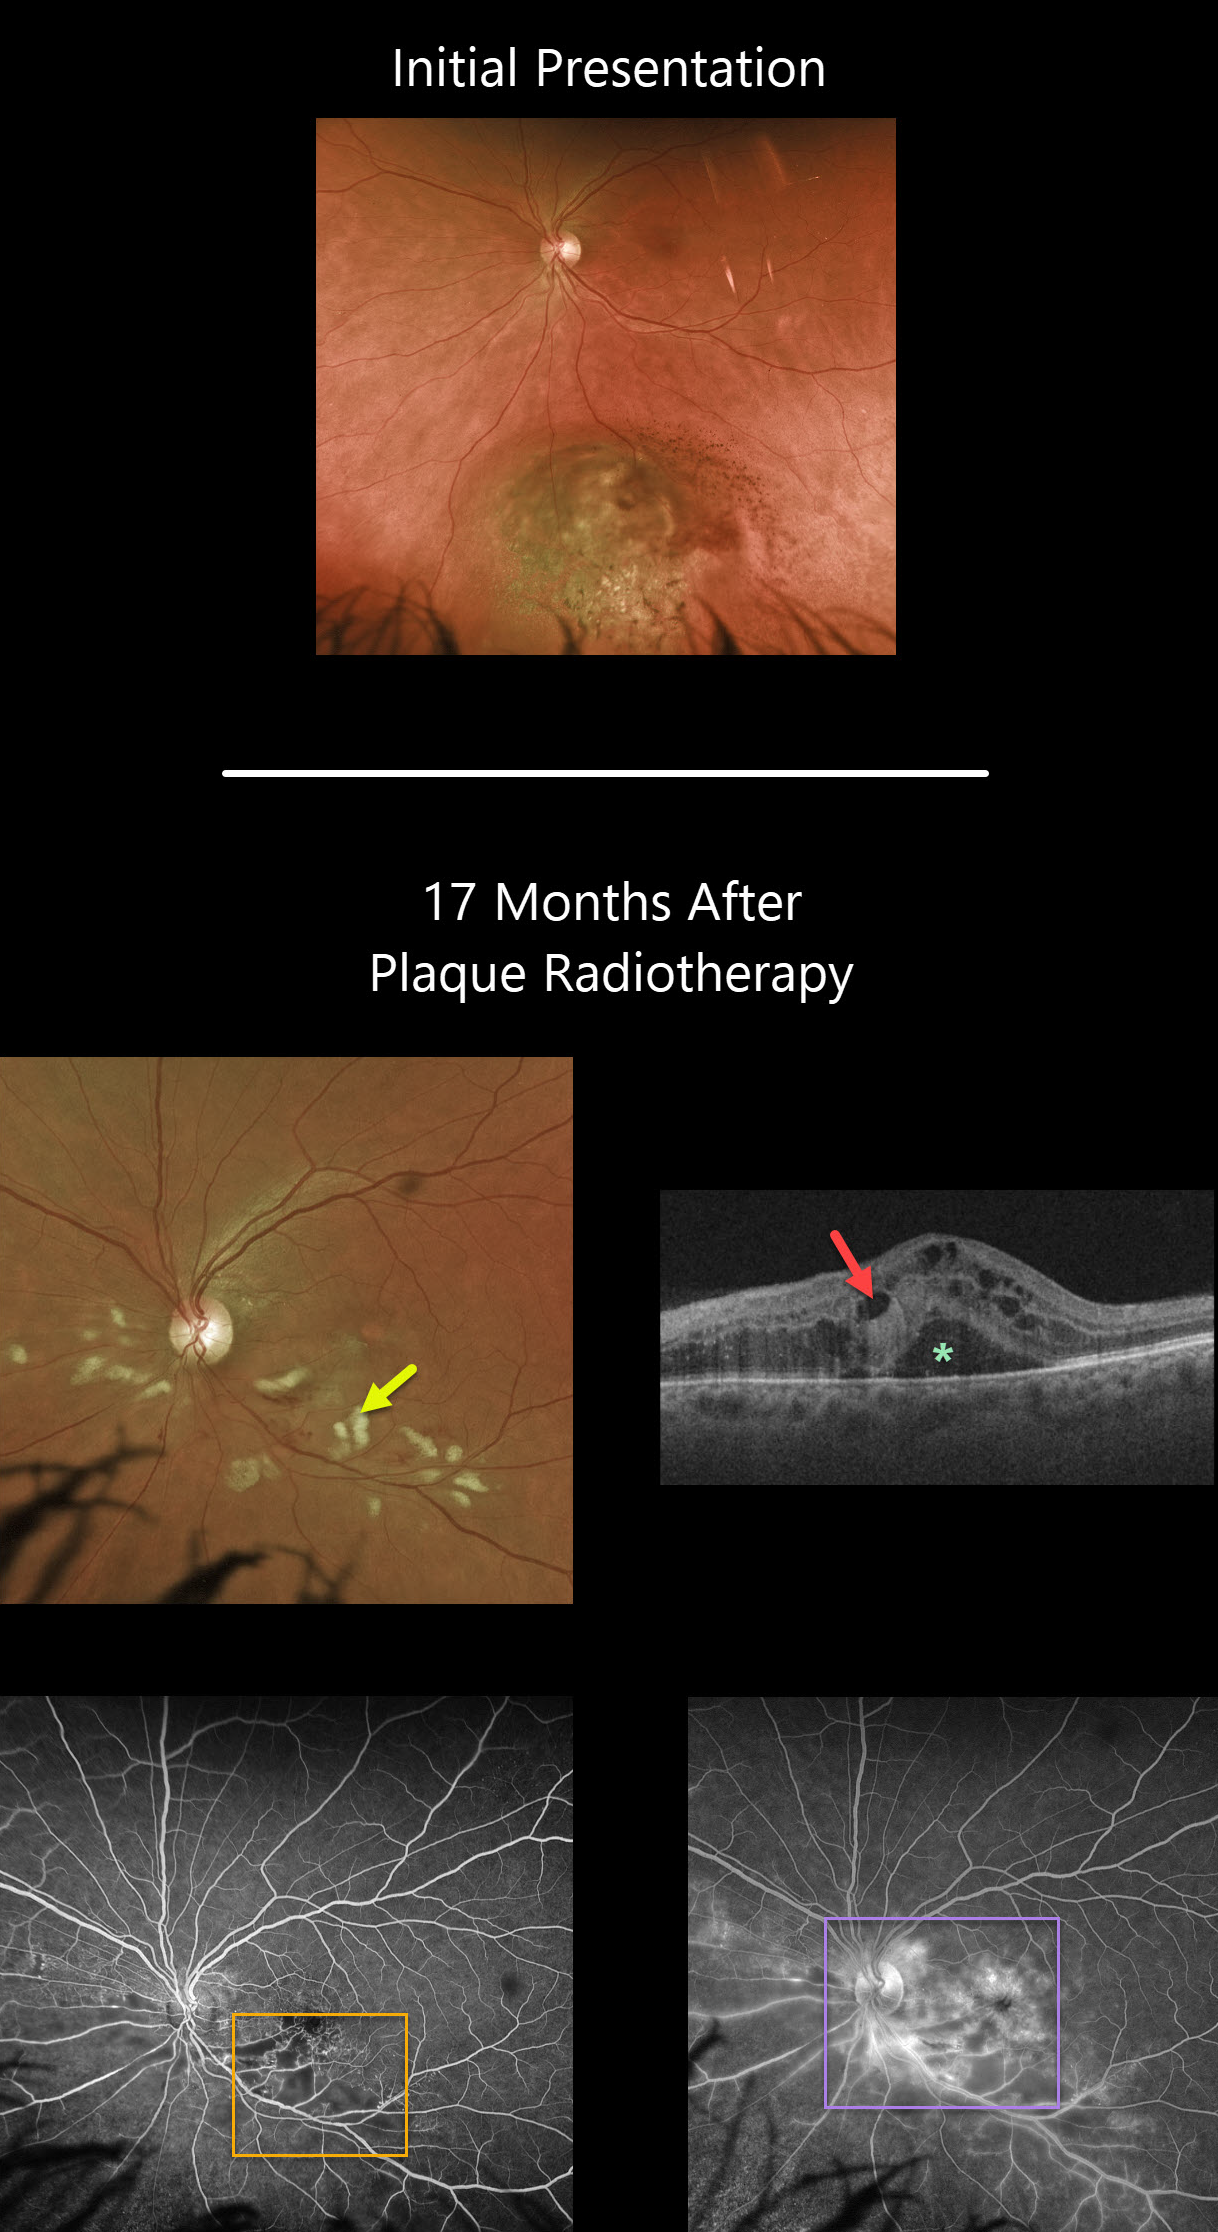
UVEAL MELANOMA
Originally posted on @retina.rocks March 29, 2021
Seventeen months following plaque radiotherapy for a uveal malignant melanoma, this patient developed radiation retinopathy with scattered inner retinal hemorrhages and nerve fiber layer infarcts (cotton wool spots). Vision was counting fingers, although it had been 20/40 ten days following plaque therapy a year and a half earlier.
Cystoid macular edema with subretinal fluid is noted on Triton swept-source OCT. Fluorescein angiography shows areas of capillary dropout, telangiectasias, and hyperfluorescent leakage secondary to cystoid macular edema.
Learning Points:
Radiation retinopathy usually occurs 3 months to 3 years after external beam radiation (e.g., for facial or orbital cancers) or plaque radiotherapy. The ocular findings closely resemble those seen with diabetic retinopathy, as in our patient, who is receiving Avastin injections for the macular edema.
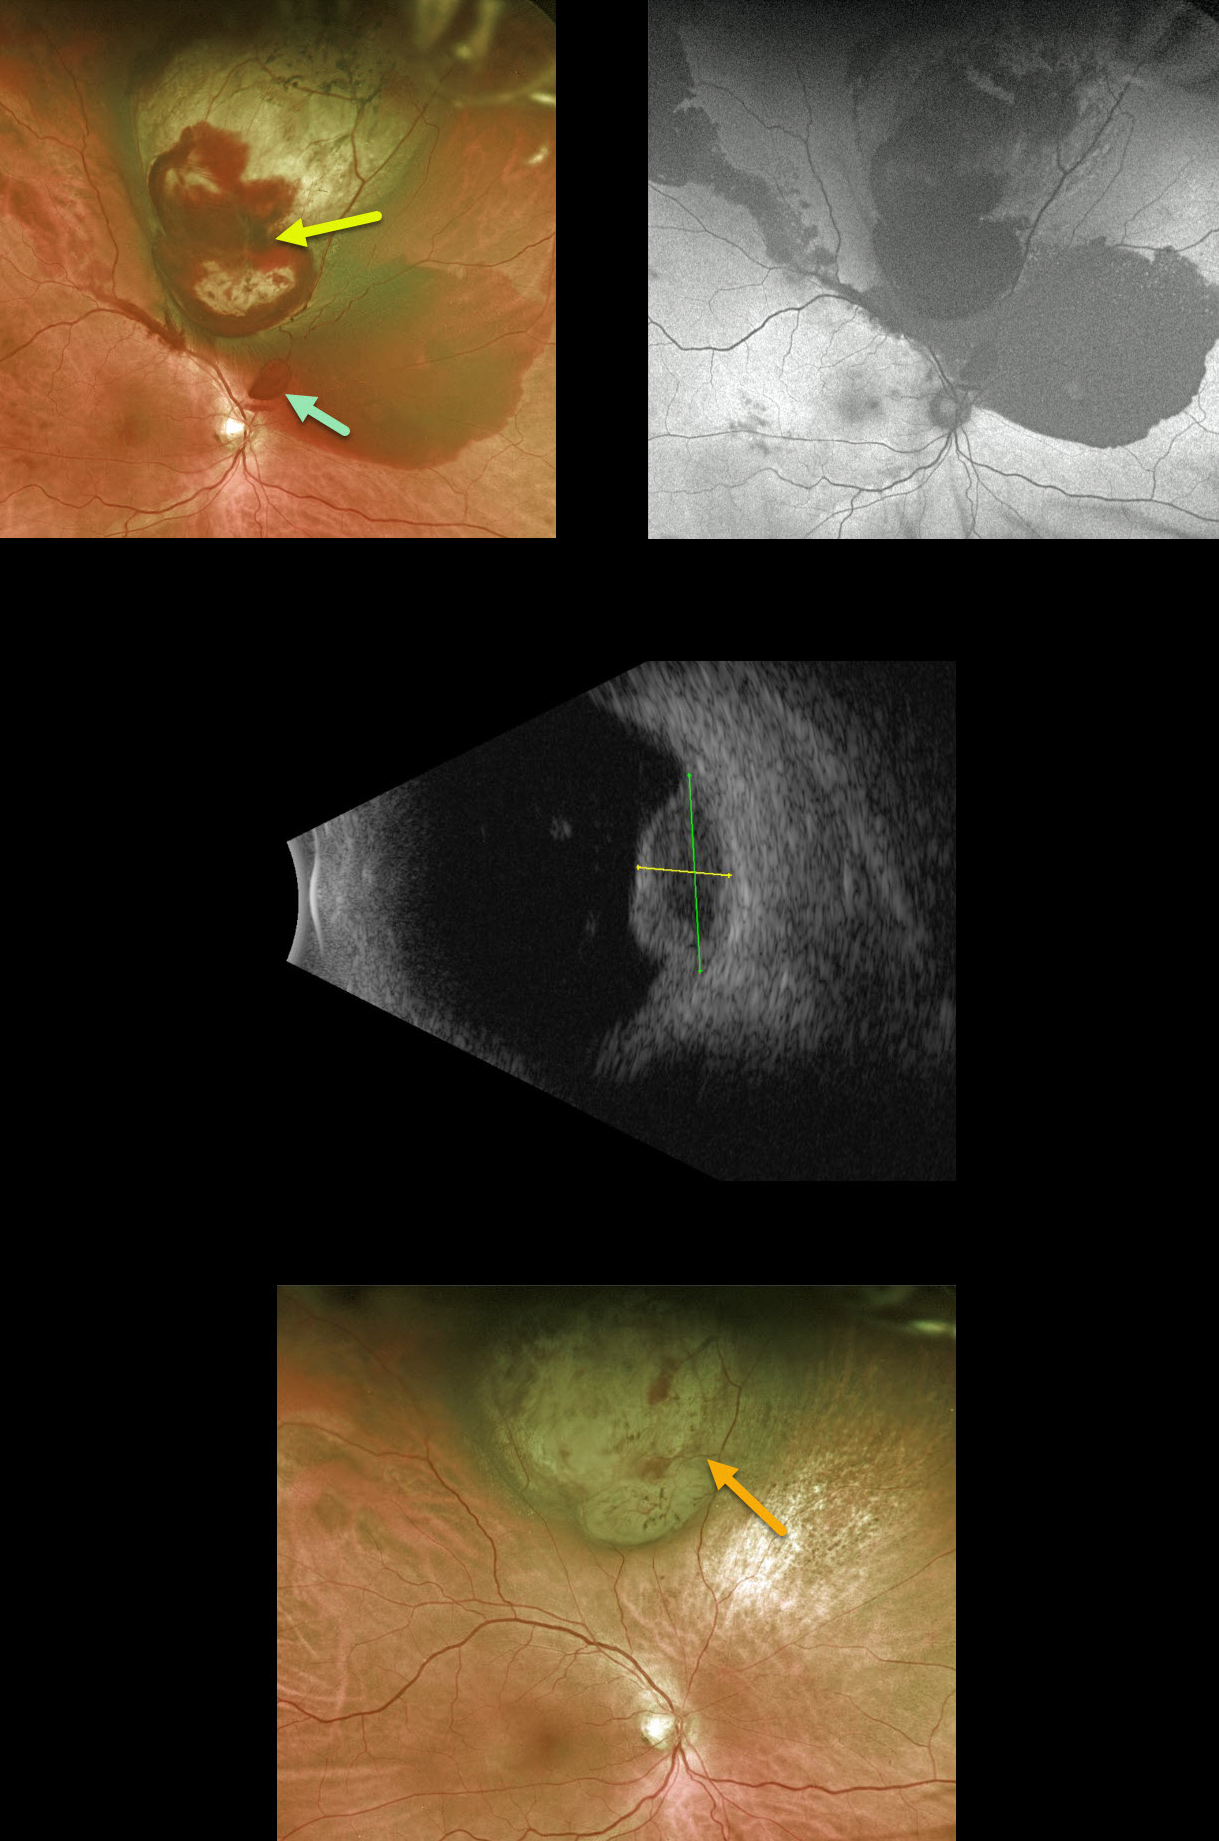
UVEAL MELANOMA
Originally posted on @retina.rocks March 4, 2021
This 60YO male presented with 20/25 vision in his right eye despite a superior uveal malignant melanoma. The tumor was associated with subretinal blood overlying and outside the lesion, as well as a small area of preretinal blood just superior to the optic nerve.
Fundus autofluorescence showed no lipofuscin. The tumor measured 5.55mm in thickness, with a basal diameter of 11.07mm, and appeared hollow on ultrasound, while the overlying subretinal blood was more echogenic.
A few days prior to radioactive plaque therapy, he noted a severe worsening of vision and was found to have a dense vitreous hemorrhage, obscuring the view of the tumor (not pictured).
Pars plana vitrectomy was performed at the time of plaque placement to clear the view and allow for transvitreal fine-needle aspiration.
About 3 months postoperatively, the tumor regressed to a thickness of 3.5mm. The subretinal blood resolved with secondary pigmentary changes, and his vision returned to baseline.
Learning Points:
Genetic expression profiling demonstrated a Class 1B, PRAME-negative tumor.
The patient continues to be followed closely for local recurrence and metastatic disease.
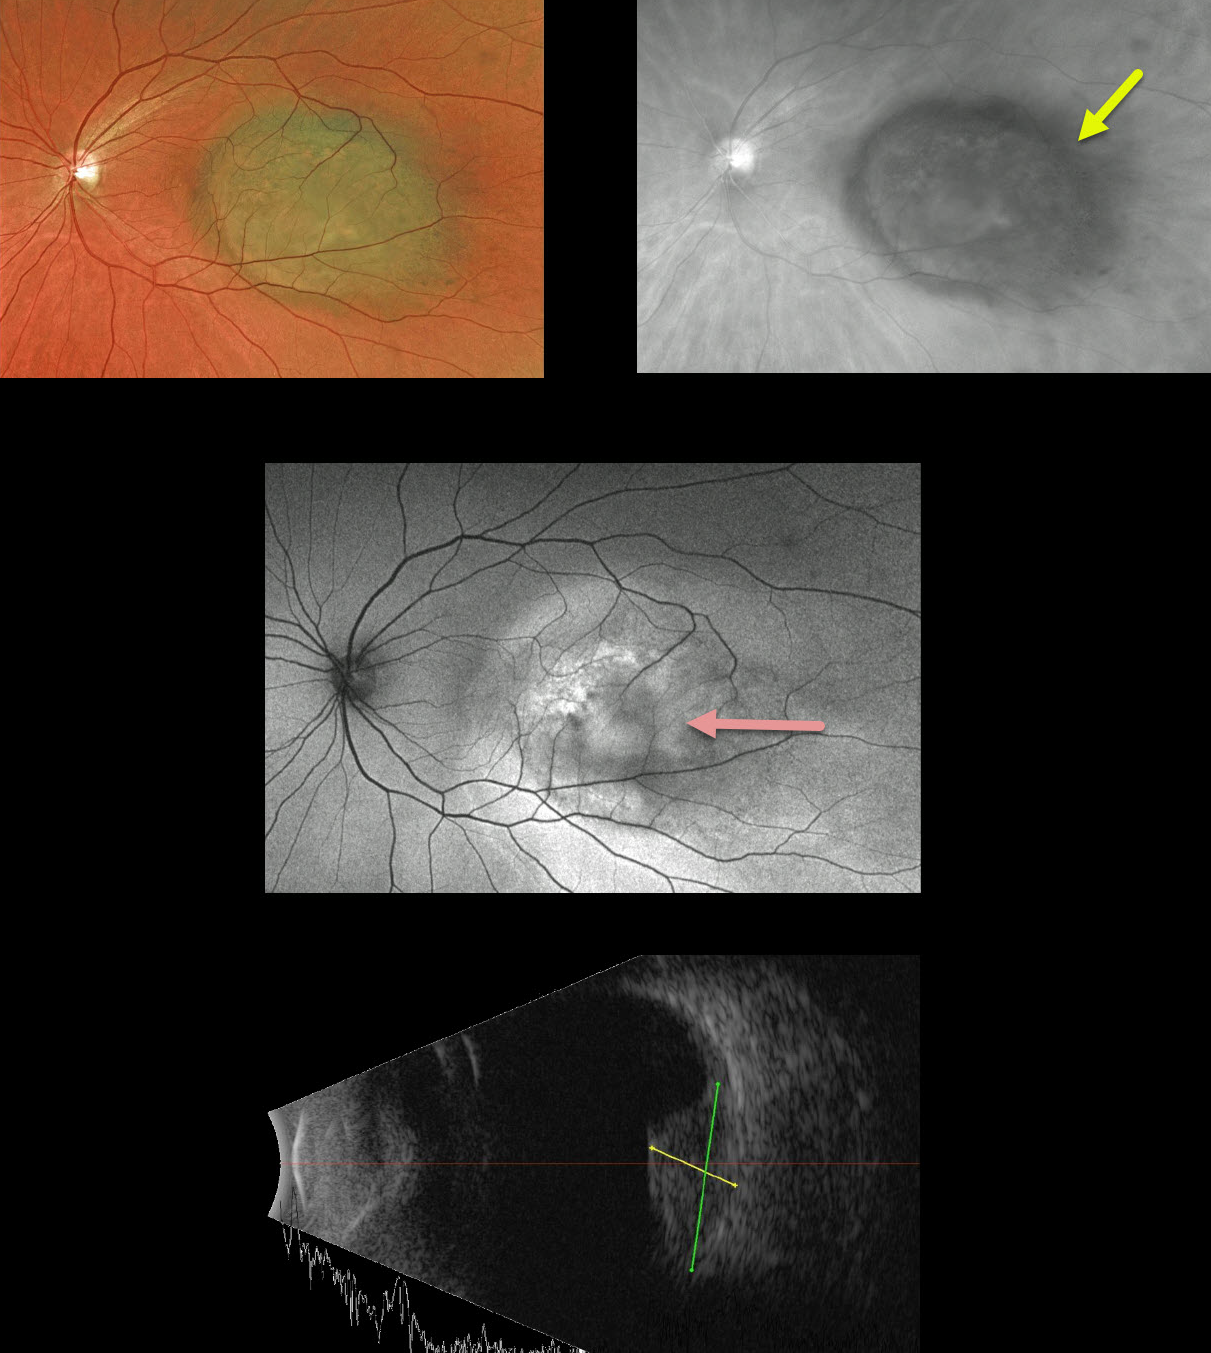
UVEAL MELANOMA
Originally posted on @retina.rocks January 18, 2021
This 52YO female presented with 20/200 vision in her left eye due to a uveal malignant melanoma. Amazingly, she was completely asymptomatic since she was right eye dominant.
The hyperpigmented lesion is well visualized on the Optos red channel and exhibits variable hyper- and hypoautofluorescence. The tumor measured about 5.5mm in thickness and 12mm in basal diameter on B-scan.
Radioactive plaque therapy was recommended.
Learning Points:
Clinical characteristics of choroidal nevi at risk for progressing to a uveal MM were described by Shields et al. (Ophthalmology 1995;102:1351-1361). The most recent version of this famous acronym, To Find Small Ocular Melanoma Doing Imaging (TFSOM-DIM, Retina 2019;39:1840-1851) is:
To (Thickness >2mm)
Find (Subretinal Fluid)
Small (Symptoms, vision <= 20/50)
Ocular (Orange pigment)
Melanoma (Melanoma hollow)
DIM (DIIaMeter >5mm)
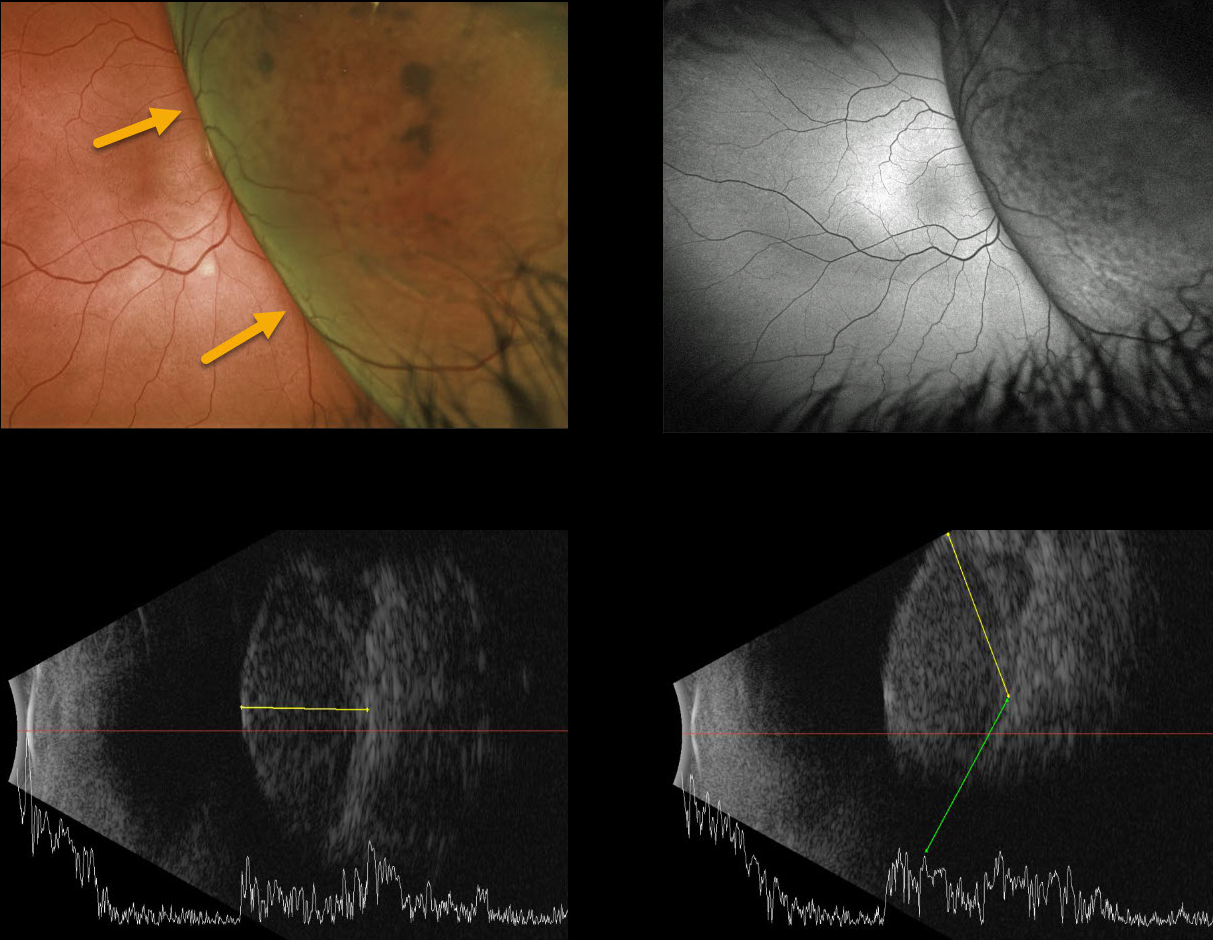
UVEAL MELANOMA
Originally posted on @retina.rocks October 20, 2020
This 81yo presented with peripheral vision loss. Vision was 20/100.
She had a large nasal uveal melanoma draping over the optic nerve. The tumor measured 10 mm in thickness and over 23 mm in basal diameter on B-scan ultrasonography.
Enucleation was recommended.
Learning Points:
Clinical characteristics of choroidal nevi at risk for progressing to a uveal MM were described by Shields et al. (Ophthalmology 1995;102:1351-1361). The most recent version of this famous acronym, To Find Small Ocular Melanoma Doing Imaging (TFSOM-DIM, Retina 2019;39:1840-1851) is:
To (Thickness >2mm)
Find (Subretinal Fluid)
Small (Symptoms, vision <= 20/50)
Ocular (Orange pigment)
Melanoma (Melanoma hollow)
DIM (DIaMeter >5mm)
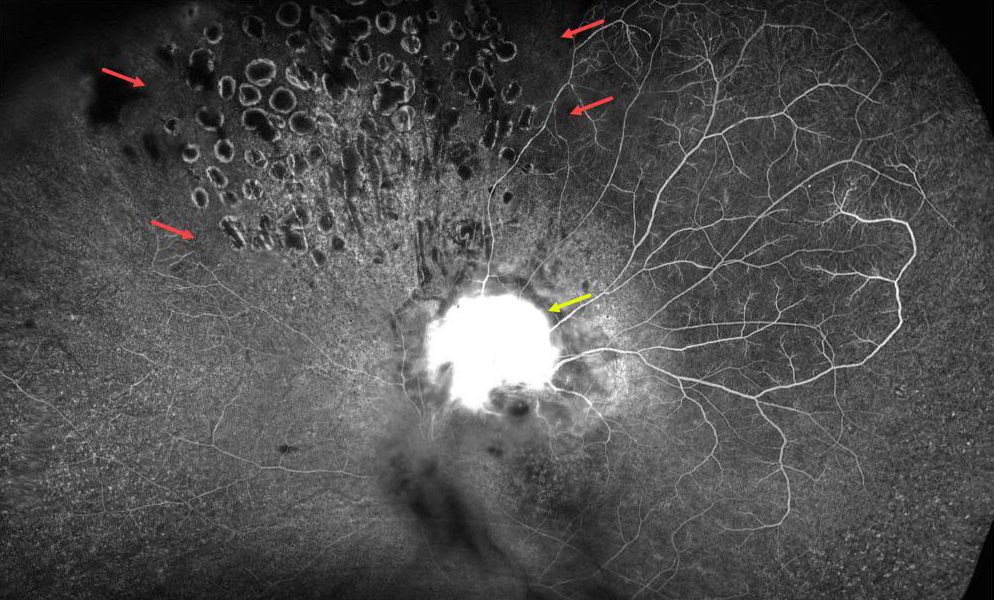
UVEAL MELANOMA
Originally posted on @retina.rocks June 19, 2020
This patient had a uveal melanoma previously treated with plaque radiotherapy.
Although the tumor was destroyed, retinal capillary damage created ischemic regions and secondary retinal neovascularization. The tumor diffusely stains on fluorescein angiography. Although scatter laser successfully caused the neovascularization to regress, residual areas of nonperfusion remain.
Learning Points:
Retinal neovascularization, which develops at the vitreoretinal interface, is caused by retinal ischemia. Remember that neovascularization below the retina is usually caused by subretinal disorders.
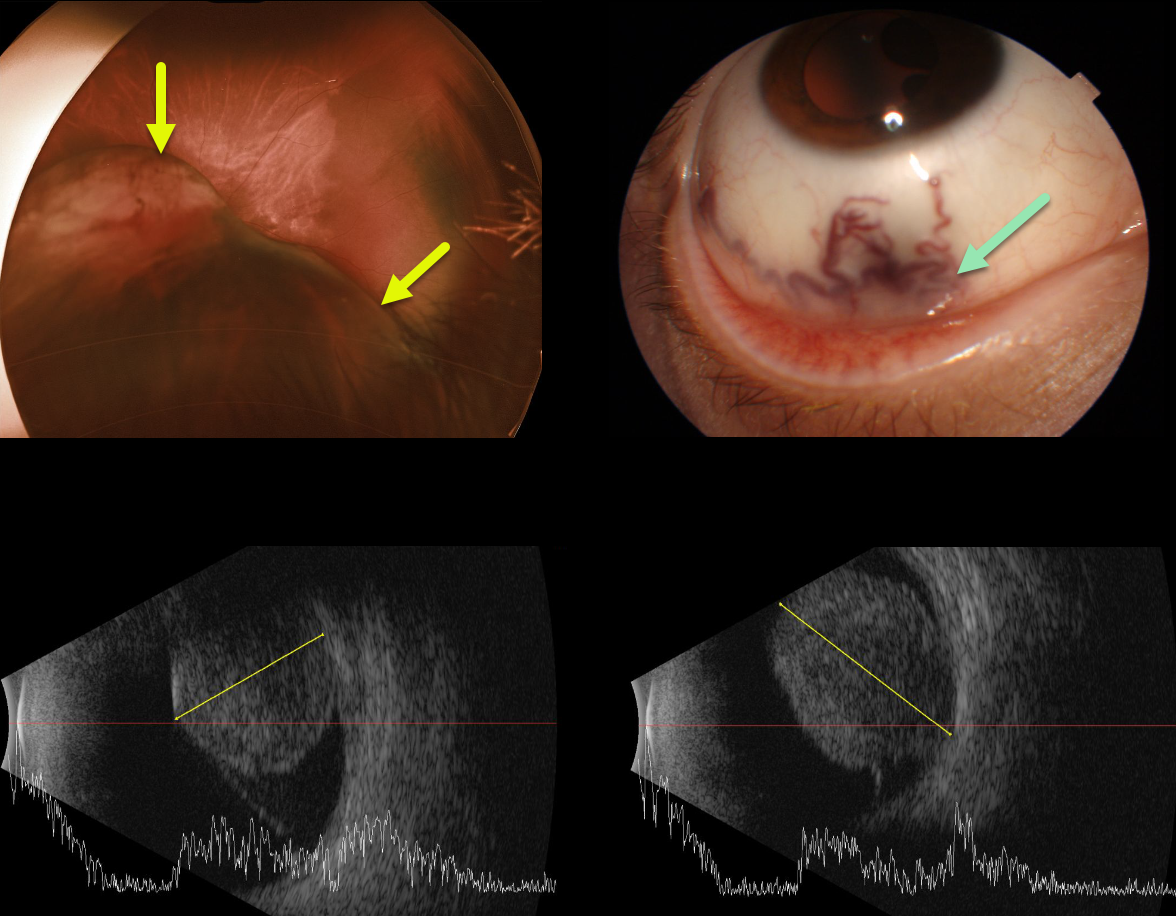
UVEAL MELANOMA
Originally posted on @retina.rocks May 14, 2020
This 22YO white male presented with a large ciliary body uveal malignant melanoma that was about 14mm thick x 18mm in length on B-scan ultrasonography.
Unfortunately, the tumor required enucleation since it was too large for radioactive plaque therapy.
Learning Points:
Large and dilated episcleral (sentinel) vessels are often a tell-tale sign of an underlying tumor.
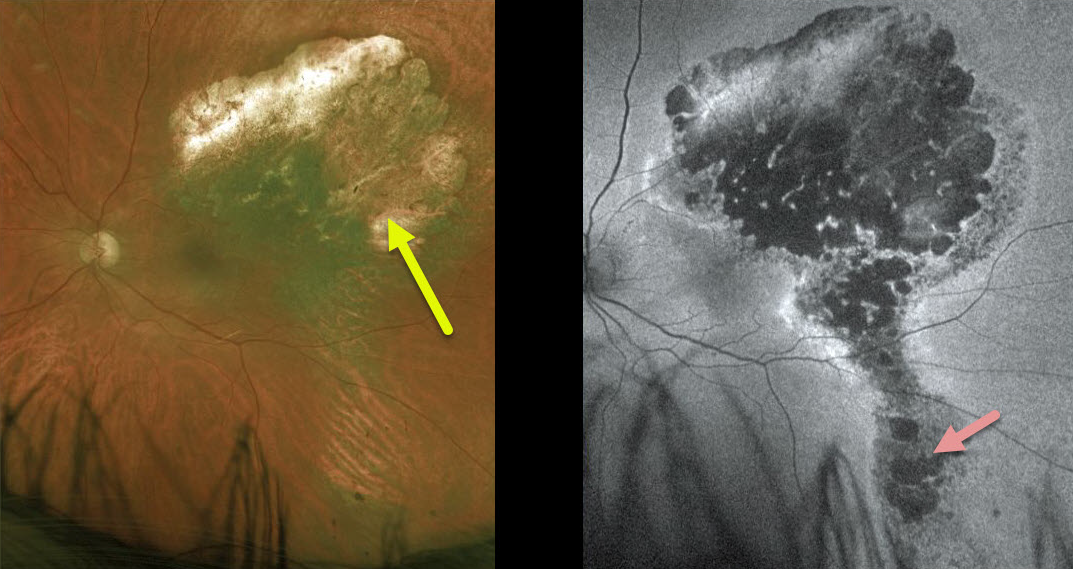
UVEAL MELANOMA
Originally posted on @retina.rocks February 7, 2020
This is a patient with uveal melanoma treated with a radiation plaque therapy 8 years ago.
Widefield fundus autofluorescence helps us image these clinically subtle RPE findings better than ever before.
Learning Points:
When active, these lesions can chronically leak causing disruption in the RPE with a “gutter”. Gutters are commonly seen in pathology with chronic leakage, including central serous retinopathy and overlying choroidal hemangiomas, choroidal nevi and uveal melanoma.


