

Vasoproliferative Tumor
<< Back to Cases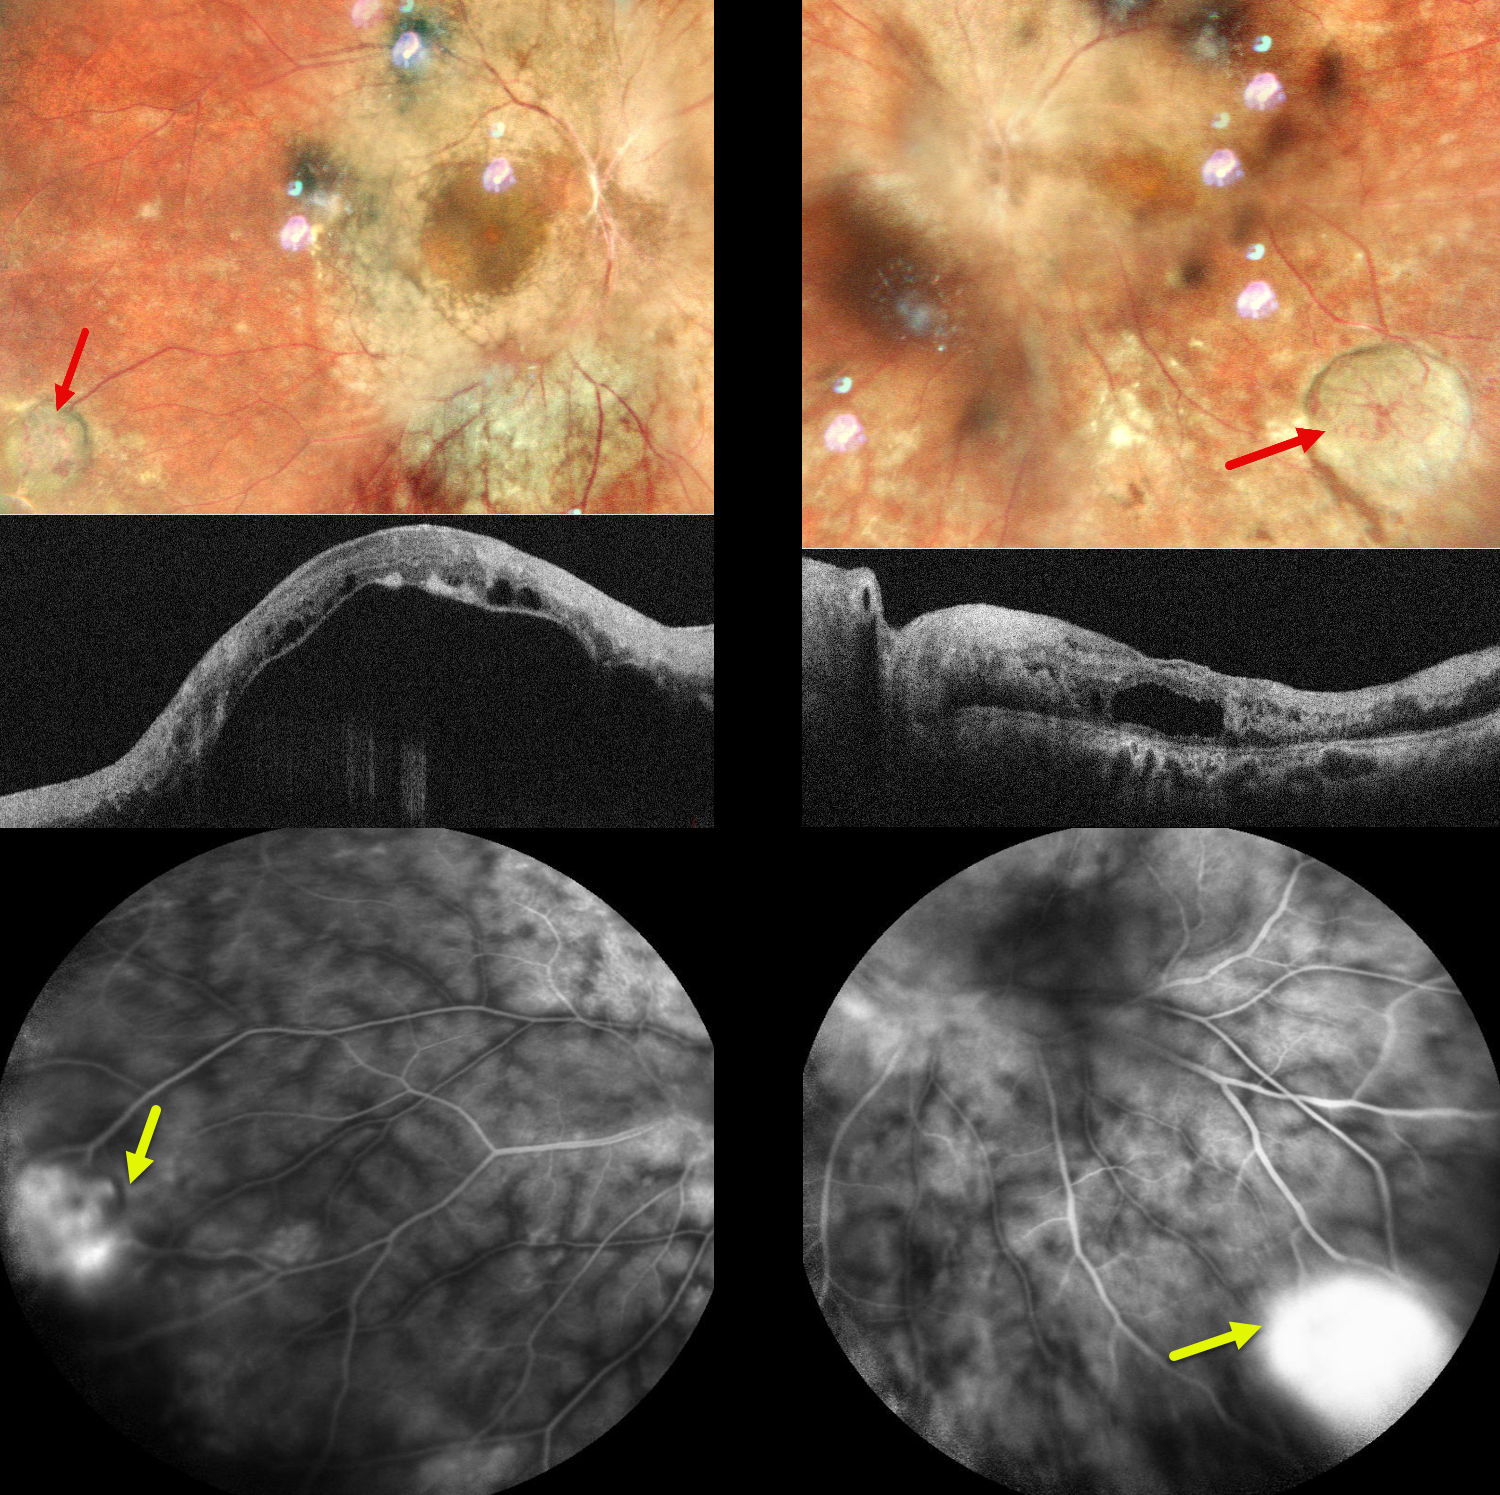
VASOPROLIFERATIVE TUMOR
Rohan Jain and Manish Nagpal
Originally posted on @retina.rocks July 20, 2026
This 37YO female presented with a 10-day history of pain in both eyes and 9 years of poor vision OU. She was diagnosed elsewhere 10 years earlier with chronic vitritis, which was treated with oral steroids. Vision was counting fingers OU. There were bilateral posterior subscapular cataracts that were not considered visually significant.
Pseudocolor SLO imaging shows a yellow-white vascularized lesion in each inferotemporal periphery associated with non-dilated feeding and draining vessels. The central retinal detail is blurred due to the cataracts. However, the major vessels overlying the discs appear sheathed with possible disc swelling OS. Deep retinal whitening/opacification is noted in each posterior pole, which seems to spare the macular centers.
OCT shows an opaque, hyperreflective retina bilaterally. There is marked subretinal fluid OD with a large hyporeflective pocket of fluid in the outer left macula. These lesions leak on fluorescein angiography.
Learning Points:
Vasoproliferative tumors (VPTs) are reactive lesions characterized by vascular and glial proliferation, often triggered by intraocular inflammation. They appear yellow or red and can cause subretinal exudation and detachment, anterior or posterior segment neovascularization, and vitreous hemorrhage. VPTs may arise as primary idiopathic lesions or as a vascular response to various conditions, including intermediate uveitis, retinitis pigmentosa, Coats disease, and prior retinal detachment (Shields et al, JAMA Ophthalmology 2013;131:328–334). In uveitic VPTs, breakdown of the blood-retinal barrier and cytokine-mediated angiogenesis contribute to their development.
Despite their benign nature, VPTs can cause significant visual loss through complications such as macular exudation, cystoid macular edema, vitreous hemorrhage, and epiretinal membrane formation. Treatment options include thermal laser, cryotherapy, and/or anti-VEGF injections. Bilateral intravitreal anti-VEGF injections followed by direct thermal laser photocoagulation were recommended, but the patient was immediately lost to follow-up.
VASOPROLIFERATIVE TUMOR
Originally posted on @retina.rocks November 15, 2021
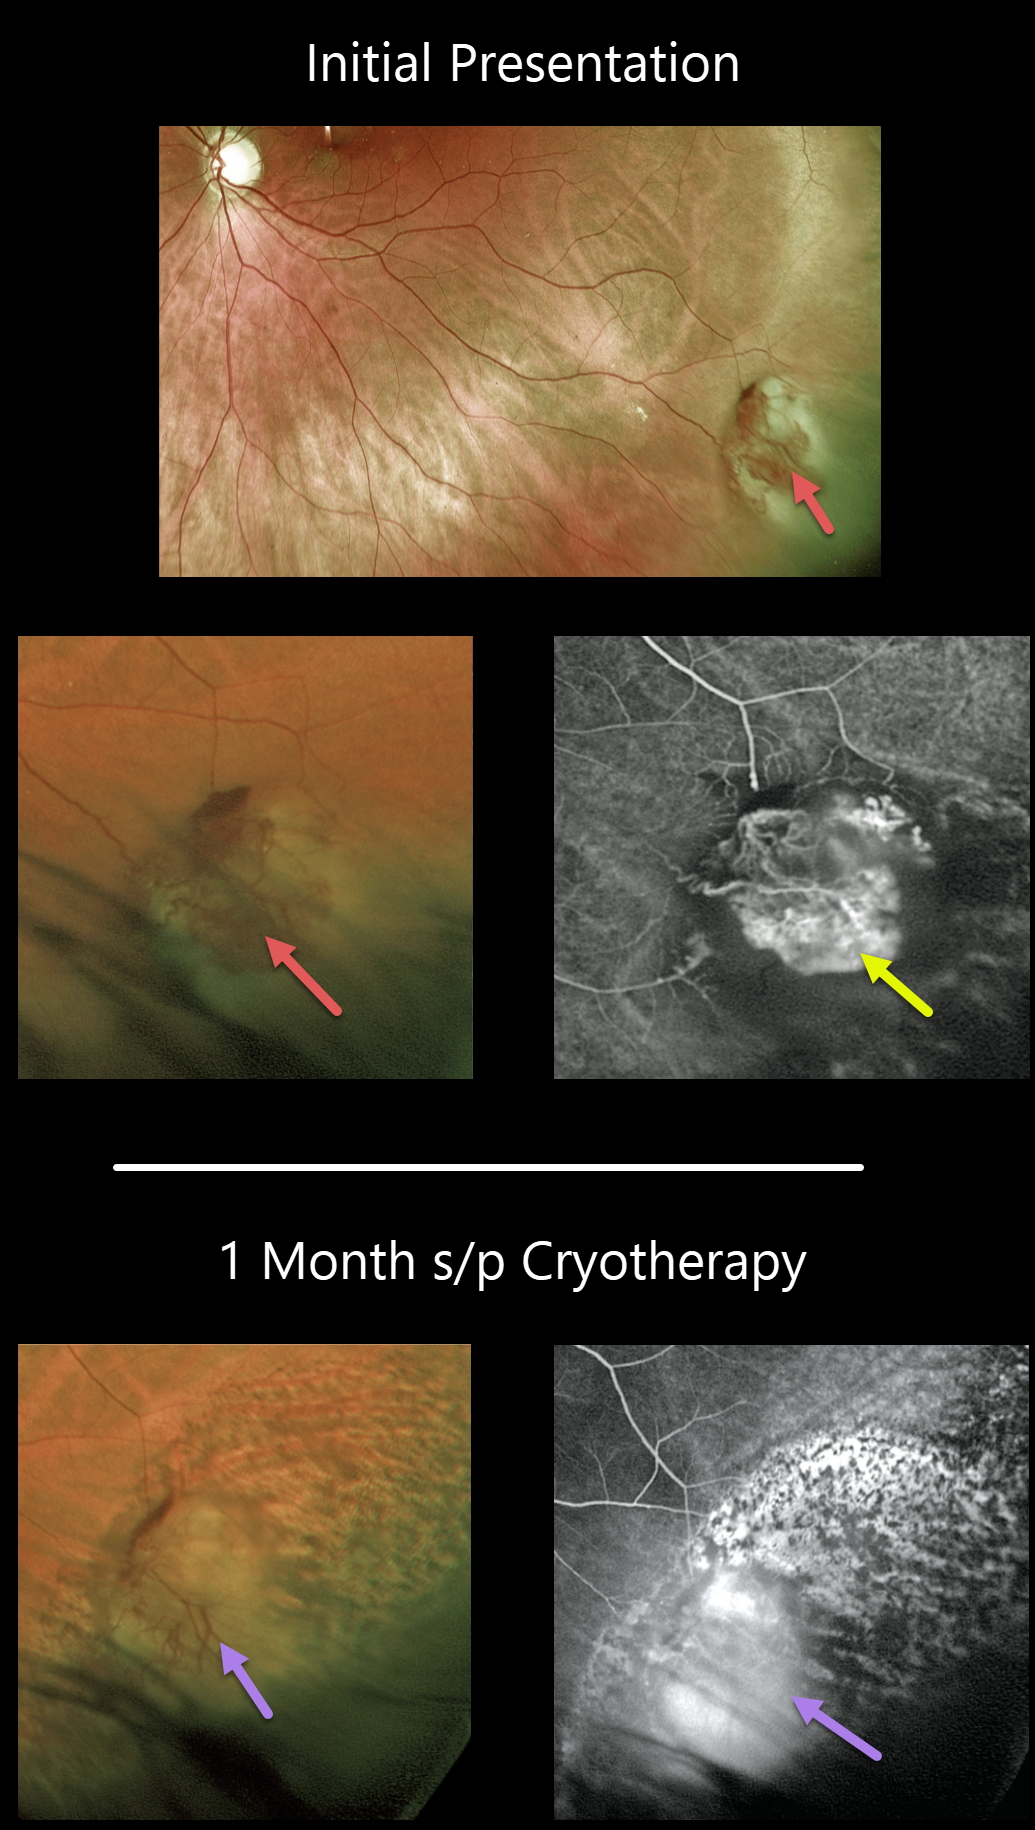
This 39YO female presented with an asymptomatic vasoproliferative tumor (VPT). The VPT initially appeared as a vascularized, reddish, elevated, peripheral mass.
Fluorescein angiography revealed the vascular nature of the lesion. The lesion was treated with cryotherapy and already showed signs of regression at the 1-month postoperative exam.
Learning Points:
Vasoproliferative tumors are benign globular, dome-shaped lesions arising in the peripheral retina. They can be yellow or red and cause subretinal exudation and detachment, anterior or posterior segment neovascularization, and vitreous hemorrhage.
They can be primary idiopathic lesions (as in our patient) or a vascular response to various entities, including intermediate uveitis, retinitis pigmentosa, Coats disease, and prior retinal detachment (see Shields et al, JAMA Ophthalmology 2013;131;328-334).
The lesions can be treated with thermal laser, cryotherapy, and/or anti-VEGF injections.
VASOPROLIFERATIVE TUMOR
Originally posted on @retina.rocks June 29, 2020
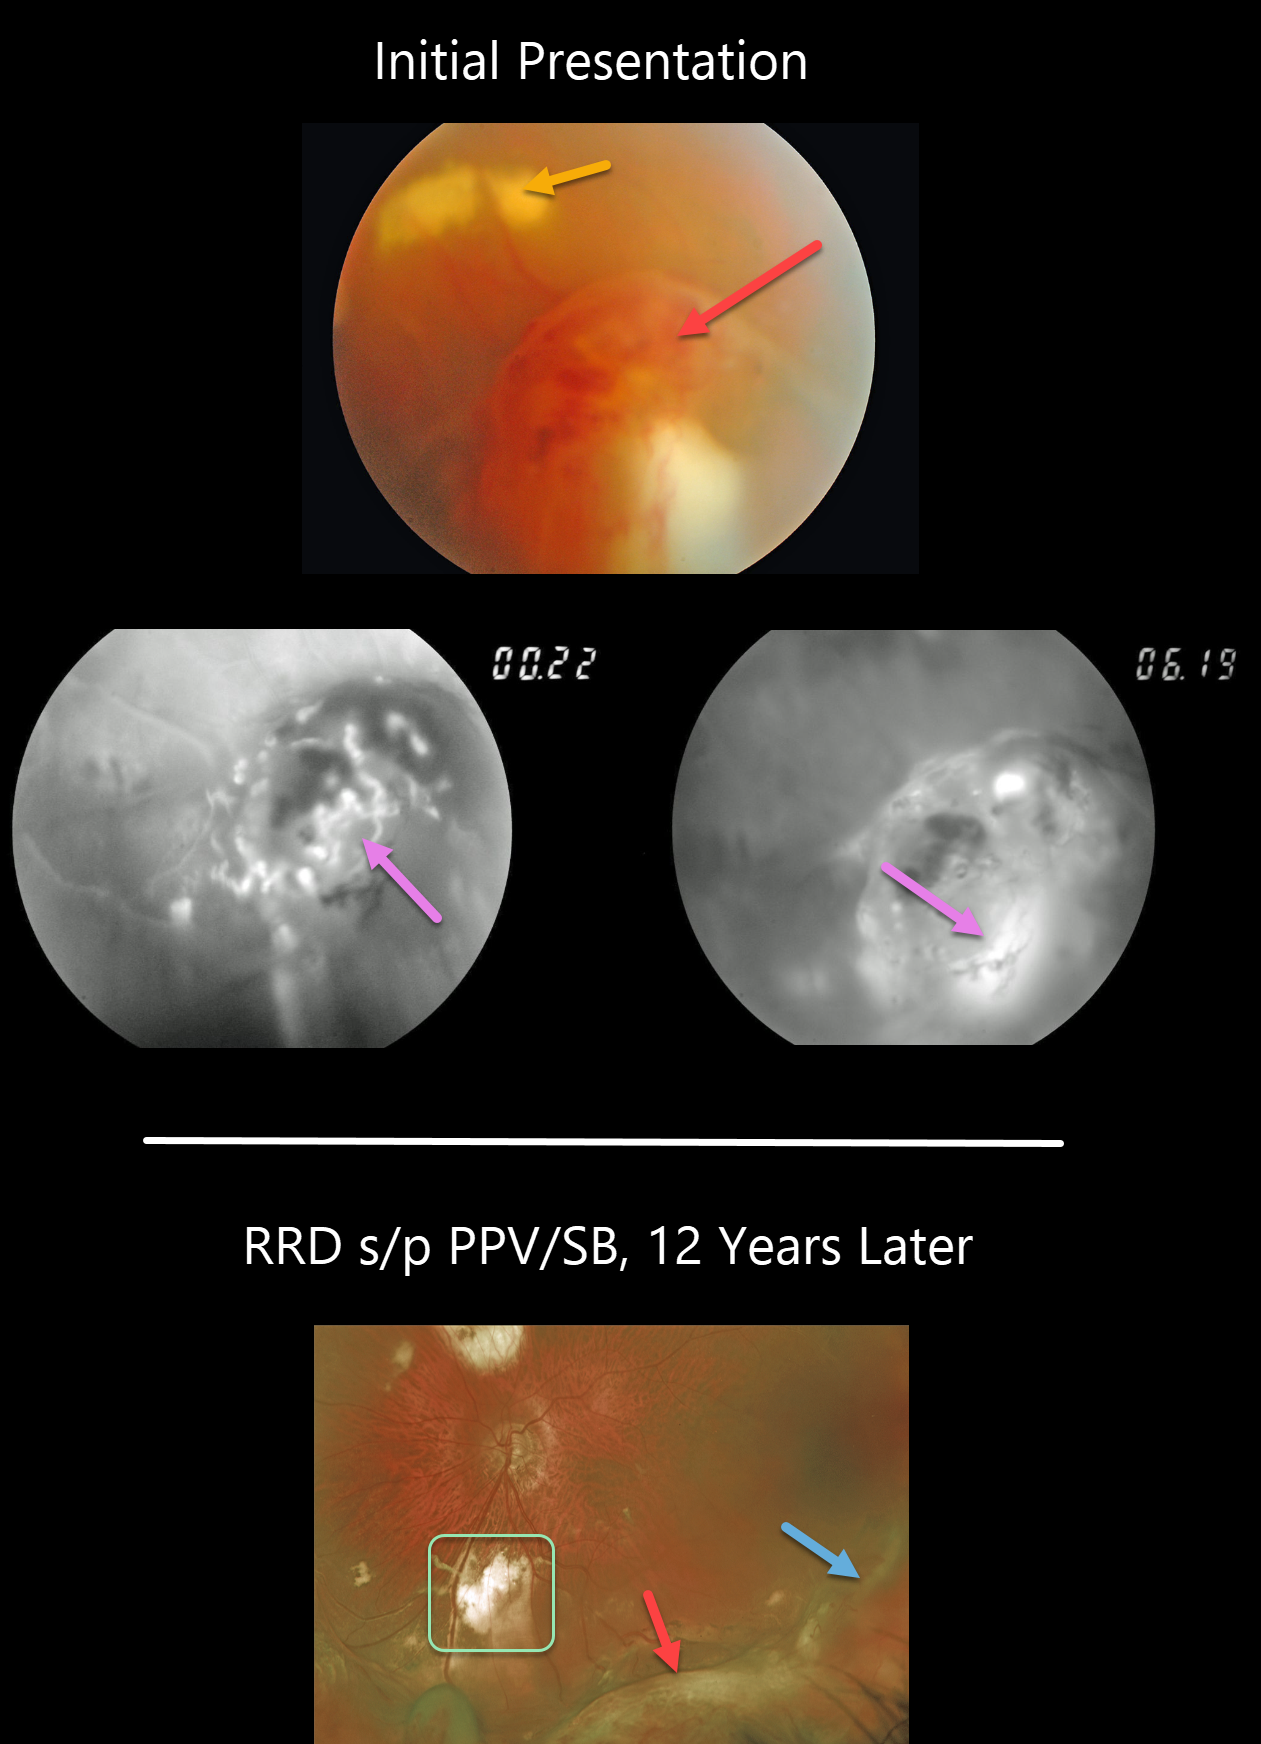
This 46YO presented with an asymptomatic vasoproliferative tumor (VPT). The VPT initially appeared as a tongue-like, reddish, elevated, peripheral mass with more posterior subretinal lipid. Fluorescein angiography (FA) revealed the vascular nature of the lesion.
He then developed a rhegmatogenous retinal detachment that was repaired with a combined vitrectomy and scleral buckle. The indentation from the buckle is visible more temporally and distinct from the complex enlarged VPT more inferiorly. The subretinal lipid resolved with more extensive subretinal scarring.
Learning Points:
Vasoproliferative tumors are benign globular, dome-shaped lesions arising in the peripheral retina. They can be yellow or red and cause subretinal exudation and detachment, anterior or posterior segment neovascularization, and vitreous hemorrhage.
They can be primary idiopathic lesions or a vascular response to various entities, including intermediate uveitis, retinitis pigmentosa, Coats disease, and prior retinal detachment.
For lesions causing symptomatic exudation or neovascularization, treatment with thermal laser, cryotherapy, and/or anti-VEGF injections is indicated.


